
Complete denture assessment
A new impression is only useful after the cause of the patient’s difficulty is understood. Assess the tissues, the prosthesis and the person’s ability to use it together.
Quick revision summary
Define the complaint
Translate loose, painful or difficult to chew into testable findings. Assess the old prosthesis and what the patient values, then separate base adaptation, borders, contacts and muscular displacement.
Examine the foundation
Map the ridges, mucosa, saliva, undercuts and functional limits. These determine support, impression strategy and expectations; an accurate base alone does not guarantee stability or comfort.
Choose a proportionate intervention
Compare adjustment, reline, rebase, replacement and feasible implant options. Preserve features that work and correct the demonstrated cause, with a maintenance and review plan the patient can use.
Common mistake
A denture that stays in place at rest can still tip during chewing or be displaced by borders and tongue movement.
Complete denture assessment
A new impression is only useful after the cause of the patient’s difficulty is understood. Assess the tissues, the prosthesis and the person’s ability to use it together.
Turn a complaint into a testable problem
Ask the patient to demonstrate the problem: does the upper denture drop during speech, does the lower denture lift on opening, or does a saddle tip when chewing on one side? Establish when the difficulty began, whether it followed an extraction or weight change, and what has already been tried. Comfort, appearance, speech and food choices may matter more to the patient than a clinician’s impression of retention.
Examine the denture outside the mouth for fractures, worn teeth, rough surfaces, plaque, calculus and previous repairs. Inspect the fitting surface and borders, then observe insertion, rest and function. A longstanding denture may have poor fit and altered occlusion but remain familiar to its wearer; a remake changes several variables at once. Record which features should be preserved and which need correction.
Separate support, retention and stability
| Property | What to examine | What a failure may look like |
|---|---|---|
| Support | Residual ridge, palate or mandibular bearing tissues; extent of the base; tissue tenderness | The denture sinks or causes local pressure during chewing. |
| Retention | Border seal, posterior palatal region, saliva, adaptation and displacement away from the tissues | The upper denture drops or dislodges when speaking. |
| Stability | Ridge form, tooth position, occlusal contacts and muscle interactions | The denture rocks, slides or tips under asymmetric loading. |
| Neuromuscular control | Tongue, lips, cheeks, learned control, dexterity and cognition | A technically acceptable denture is difficult to position or use. |
Map the denture-bearing tissues
Record ridge height and shape, firm versus mobile mucosa, undercuts, prominent bony areas and the depth of the sulcus in function. A flabby ridge can be displaced by an impression and rebound beneath the finished denture. A thin mucosal covering over a sharp ridge may tolerate little concentrated pressure. Salivary deficiency affects lubrication, comfort and adhesion; simply extending the border will not correct it.
In the maxilla, assess the palate, tuberosities and the posterior boundary. In the mandible, assess the buccal shelves, retromolar areas, mylohyoid region, lingual sulcus and floor-of-mouth movement. Border position must permit normal muscle activity. Identify ulcers, candidal inflammation and other lesions independently of the denture complaint; unexplained or persistent abnormalities need their own assessment.
Edentulous ridges: the denture foundation
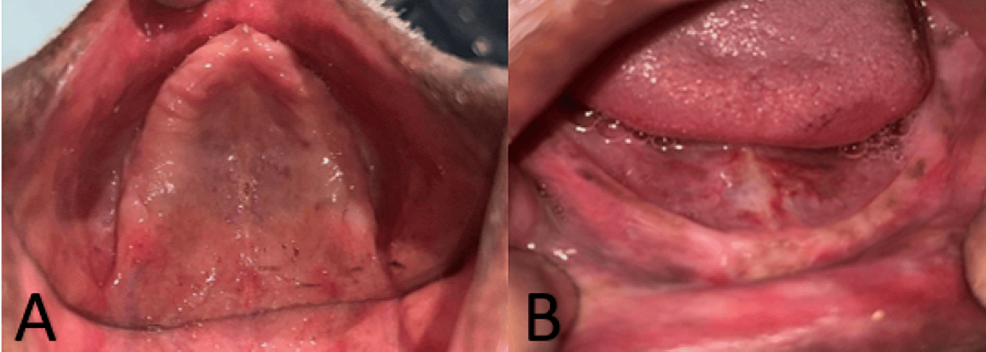
Upper (A) and lower (B) edentulous ridges in the source case. Relate the visible anatomy to the denture-bearing tissues described in the chapter.
Panel key
- A
- Maxillary edentulous ridge and palate.
- B
- Mandibular edentulous ridge.
Refining Complete Dentures — figure 2 · Rucha Chiddarwar, Anjali Bhoyar, Surekha A. Dubey, Mithilesh M. Dhamande and Sheetal R. Khubchandani · CC BY 4.0. Original published figure reproduced without alteration; panel letters and labels retained.
Assess jaw relationships and facial support
Observe the patient at rest and during speech, and examine the current occlusal vertical dimension, interarch space, tooth display and lip support. Check for a reproducible jaw relationship and whether the existing dentures slide into habitual closure. Do not infer a new vertical dimension from one facial measurement. Facial proportions, speaking space, comfort, existing records and clinical judgement contribute to the decision.
Opposing natural teeth or an implant restoration may deliver greater and less forgiving loads than another complete denture. Note parafunction and unilateral chewing. Tooth placement beyond the supporting ridge can create a tipping lever even when the fitting surface is accurate.
Choose an intervention that addresses the cause
| Option | Potential role | Limitation to discuss |
|---|---|---|
| Selective adjustment | Local border or occlusal error with an otherwise serviceable denture | Preserve a functioning seal; do not grind repeatedly without identifying the problem. |
| Reline or rebase | Changed adaptation when tooth position and jaw relationships remain acceptable | Will not correct major occlusal, aesthetic or design errors. |
| Remake | Several records or structural features need correction | Adaptation takes time; anatomical limitations remain. |
| Implant-retained overdenture assessment | Selected patients with persistent functional difficulty | Requires surgical suitability, funding, hygiene access and attachment maintenance. |
Worked assessment: a rocking lower denture
A patient describes soreness on one side and lifting on the other during chewing. Reproduce the movement, inspect the tissues and use a suitable pressure-indicating method to assess fit. Compare bilateral contacts and the position of the artificial teeth relative to the ridge. Distinguish a premature contact causing tipping from a base that lacks support or an overextended border displaced by muscles.
A small adjustment may be appropriate for an isolated error. Multiple problems may require new records and a remake. Explain the proposed change in terms of the patient’s demonstrated difficulty, then review function and tissue recovery rather than recording only that the denture was adjusted.
A distinction to remember
A denture that stays in place at rest can still tip during chewing or be displaced by borders and tongue movement.
A lower denture stays in place at rest but lifts when the patient speaks. What would you assess?
Reveal the reasoning
Check border extension, tongue space, polished surfaces and tooth position relative to muscular function. Also assess base fit and the jaw relationship. Retention at rest does not rule out muscle-driven displacement, so a reline alone may not solve the complaint.
Guidance to read alongside this chapter
Test your recall
How do support, retention and stability differ in complete dentures?
Show answer
Support resists movement towards the tissues, retention resists displacement away from them, and stability resists lateral or rotational movement. A denture can have acceptable retention yet rock under chewing forces. Assess each property separately before choosing adjustment, reline or replacement.