
Impressions and digital capture
The best recording method is the one that captures the required geometry and tissues reliably in the actual clinical field.
Quick revision summary
Define the capture task
A preparation margin, a mobile denture-bearing ridge and implant positions require different information. Choose the record method from anatomy, tissue behaviour, access and the intended prosthesis.
Control errors before capture
Manage tray rigidity or scan-body seating, tissue exposure, moisture and movement. Inspect critical margins and relationships directly; a complete-looking impression or mesh can still omit what matters.
Verify the whole transfer
Check occlusion, spatial relationships and laboratory communication as well as surface detail. Digital workflows change the error chain and storage options but do not remove clinical acceptance and verification.
Common mistake
A complete-looking scan or impression can omit a critical margin or distort a spatial relationship; surface detail alone is not accuracy.
Impressions and digital capture
The best recording method is the one that captures the required geometry and tissues reliably in the actual clinical field.
Define what needs to be captured
A fixed restoration needs a clearly defined preparation margin, adjacent and opposing teeth, sufficient occlusal information and an appropriate jaw relationship. An RPD record additionally needs surfaces important for surveying, rests, guiding planes and saddle support. A complete denture impression must address the functional foundation and borders. These are different recording problems; one successful scan of a tooth preparation does not establish suitability for a mobile edentulous ridge.
Control inflammation, saliva and bleeding before definitive capture. If a margin is inaccessible, consider whether tissue management, margin position or the restorative plan itself needs to change. The recording system cannot recover a feature that was never exposed or captured.
Conventional materials: relate properties to the task
| Material group | Useful role | Important limitation |
|---|---|---|
| Alginate | Diagnostic casts and selected preliminary records | Dimensional change with storage; follow the product’s handling and casting instructions. |
| Addition silicone / PVS | Many definitive fixed and selected removable records | Moisture control, tray support and compatibility with the clinical technique remain important. |
| Polyether | Accurate records in suitable conditions | Relative stiffness can complicate removal from significant undercuts; follow product-specific precautions. |
| Other functional or mucosal impression materials | Selected denture recording strategies | Choose for tissue condition and technique, rather than assuming one material suits every arch. |
Primary impressions for complete dentures
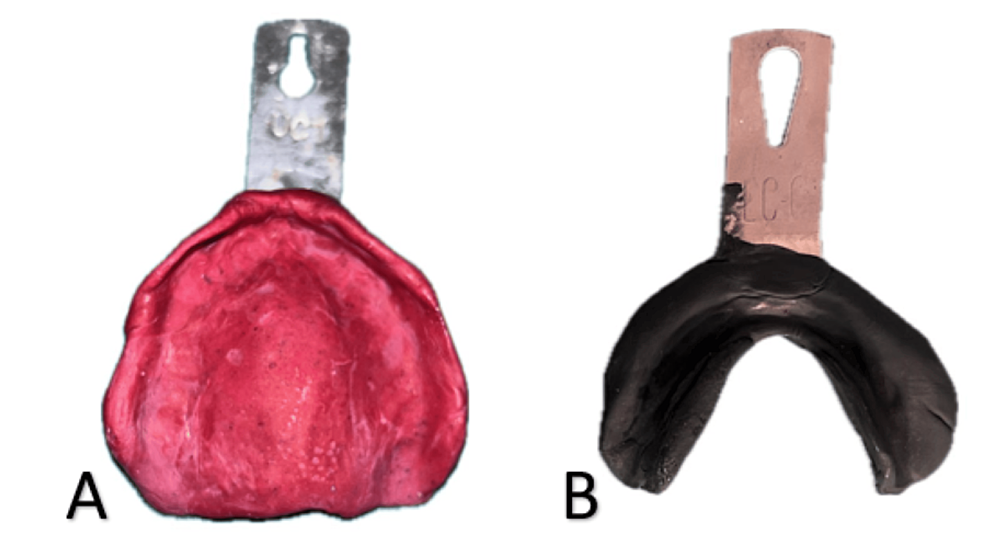
Upper and lower preliminary records from the same case. The materials illustrate this author’s technique rather than a required material choice for every patient.
Panel key
- A
- Maxillary impression in impression compound.
- B
- Mandibular impression using an admix material.
Refining Complete Dentures — figure 3 · Rucha Chiddarwar, Anjali Bhoyar, Surekha A. Dubey, Mithilesh M. Dhamande and Sheetal R. Khubchandani · CC BY 4.0. Original published figure reproduced without alteration; panel letters and labels retained.
Prevent and recognise conventional impression errors
Use a tray that supports the material with appropriate clearance and retention or adhesive. Verify adhesive compatibility and the manufacturer’s drying instructions. Coordinate working and setting times, seating and removal. Movement during setting, tray flex, insufficient support and improper removal can create distortion without an obvious large void.
Inspect the margin circumferentially, not just the most visible buccal surface. Look for tears, folds, drags, bubbles and areas where the tray has displaced the material. Verify that the opposing record and bite contain the necessary information. Disinfect and transport using a protocol compatible with the material, and tell the laboratory which areas are clinically important.
Definitive impressions: upper and lower arches
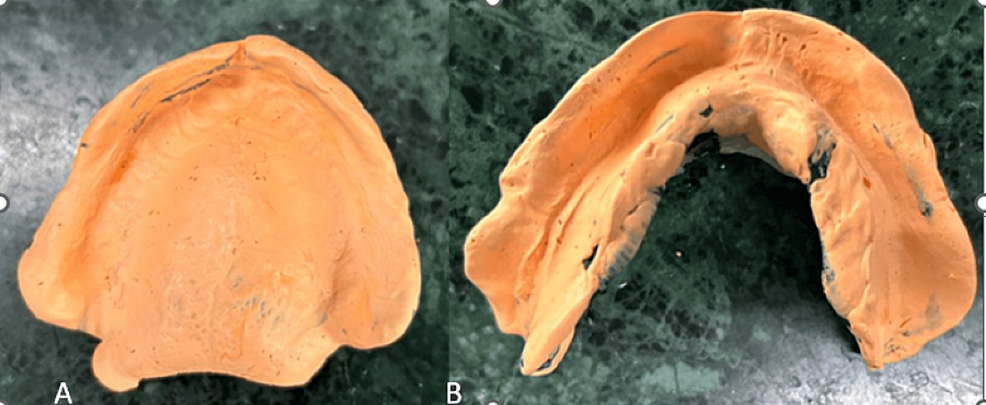
Final impressions from the source case. Compare their coverage and borders with the preliminary records, alongside the chapter’s impression checks.
Panel key
- A
- Maxillary definitive impression.
- B
- Mandibular definitive impression.
Refining Complete Dentures — figure 4 · Rucha Chiddarwar, Anjali Bhoyar, Surekha A. Dubey, Mithilesh M. Dhamande and Sheetal R. Khubchandani · CC BY 4.0. Original published figure reproduced without alteration; panel letters and labels retained.
Digital capture: accuracy includes the whole workflow
A scanner builds a model from successive captures. Long spans and limited anatomical landmarks may accumulate registration error. Reflective surfaces, saliva, movement and inaccessible areas can affect capture. Inspect the rendered model for holes, false connections and margin completeness. Repeatedly patching an unstable field can produce a convincing surface without reliable geometry.
Check the opposing scan and bite registration with the teeth correctly positioned. An attractive three-dimensional model is not proof of an accurate occlusal relationship. Scan bodies for implants must be the correct system, fully seated and captured as required by the workflow. Full-arch and soft-tissue applications may need additional verification or a different record strategy.
A practical acceptance checklist
Before sending a record, ask whether it permits the planned restoration to be designed without guessing. Confirm the necessary margins, rests, guidance surfaces, ridge extent and tissue boundaries. Review the bite, prescription, shade information and any photographs that communicate appearance. State limitations explicitly if a diagnostic rather than definitive record is being supplied.
If the record is inadequate, repeat the relevant stage after addressing the cause. A remake of the impression or scan is often a smaller intervention than compensating later with extensive restoration adjustment or an unsuccessful prosthesis.
Use a verification strategy for critical relationships
The acceptable error depends on the task. A short tooth-supported restoration and a long-span implant framework do not tolerate the same transfer uncertainty. A scan body must be fully seated and correctly identified, and a conventional coping or impression component needs equivalent verification.
Check the resulting relationship against the mouth using a method appropriate to the prosthesis. If repeated records disagree, investigate the error source before manufacture. Repeating the same capture without changing access, seating or technique may reproduce uncertainty rather than resolve it.
A distinction to remember
A complete-looking scan or impression can omit a critical margin or distort a spatial relationship; surface detail alone is not accuracy.
A scan looks complete but the distal preparation margin is missing. What should happen?
Reveal the reasoning
Improve access and tissue control and reacquire the affected area using an appropriate technique. If a reliable digital record remains impossible, reconsider the method or preparation conditions. A complete-looking model does not compensate for an unrecorded critical margin.
Test your recall
What should determine the choice of impression technique?
Show answer
Define the structures, margins and functional relationships that must be recorded, then consider tissues, access, moisture and the planned restoration. Material or scanner preference alone is insufficient. The record must answer the clinical task and be transferred reliably through the workflow.