
Complex comorbidity
Multiple conditions create interacting risks rather than a stack of independent precautions. Build one coherent plan that addresses infection, bleeding, healing, physiological reserve, medicine handling and the ability to recover.
Quick revision summary
Consider interacting risks
Renal disease, liver dysfunction, immunosuppression and polypharmacy can alter drug handling, haemostasis, infection and healing together. Assess their combined effect on the planned procedure rather than issuing separate contradictory precautions for each diagnosis.
Ask focused clinical questions
State the dental diagnosis, proposed intervention and urgency when seeking medical advice. Ask for the particular information that changes care, such as current blood results or treatment timing, rather than requesting undefined medical clearance.
Agree coordination and follow-up
Identify who will manage medicine changes, urgent deterioration and continuing dental care. Document advice, decisions and review arrangements so the patient receives a consistent plan instead of being passed between services without treatment.
Common mistake
Several individually reasonable precautions can conflict; the final plan must resolve the combined risks and specify responsibility.
Complex comorbidity
Multiple conditions create interacting risks rather than a stack of independent precautions. Build one coherent plan that addresses infection, bleeding, healing, physiological reserve, medicine handling and the ability to recover.
Prioritise the conflicts that change care
List the conditions and exposures relevant to the proposed procedure, then identify where their management conflicts. An NSAID may help inflammatory pain but be inappropriate with renal disease and anticoagulation; a long operation may avoid repeated travel but exceed respiratory reserve. Ask about current stability, functional change, treatment dates and what matters to the patient. Separate urgent dental disease from elective goals. A useful plan states which risk requires action now, which can be managed locally and which needs another team's input. Collecting several general clearances does not guarantee that the combined plan is safe or usable.
Osteoclast resorption and osteoblast formation during bone remodelling
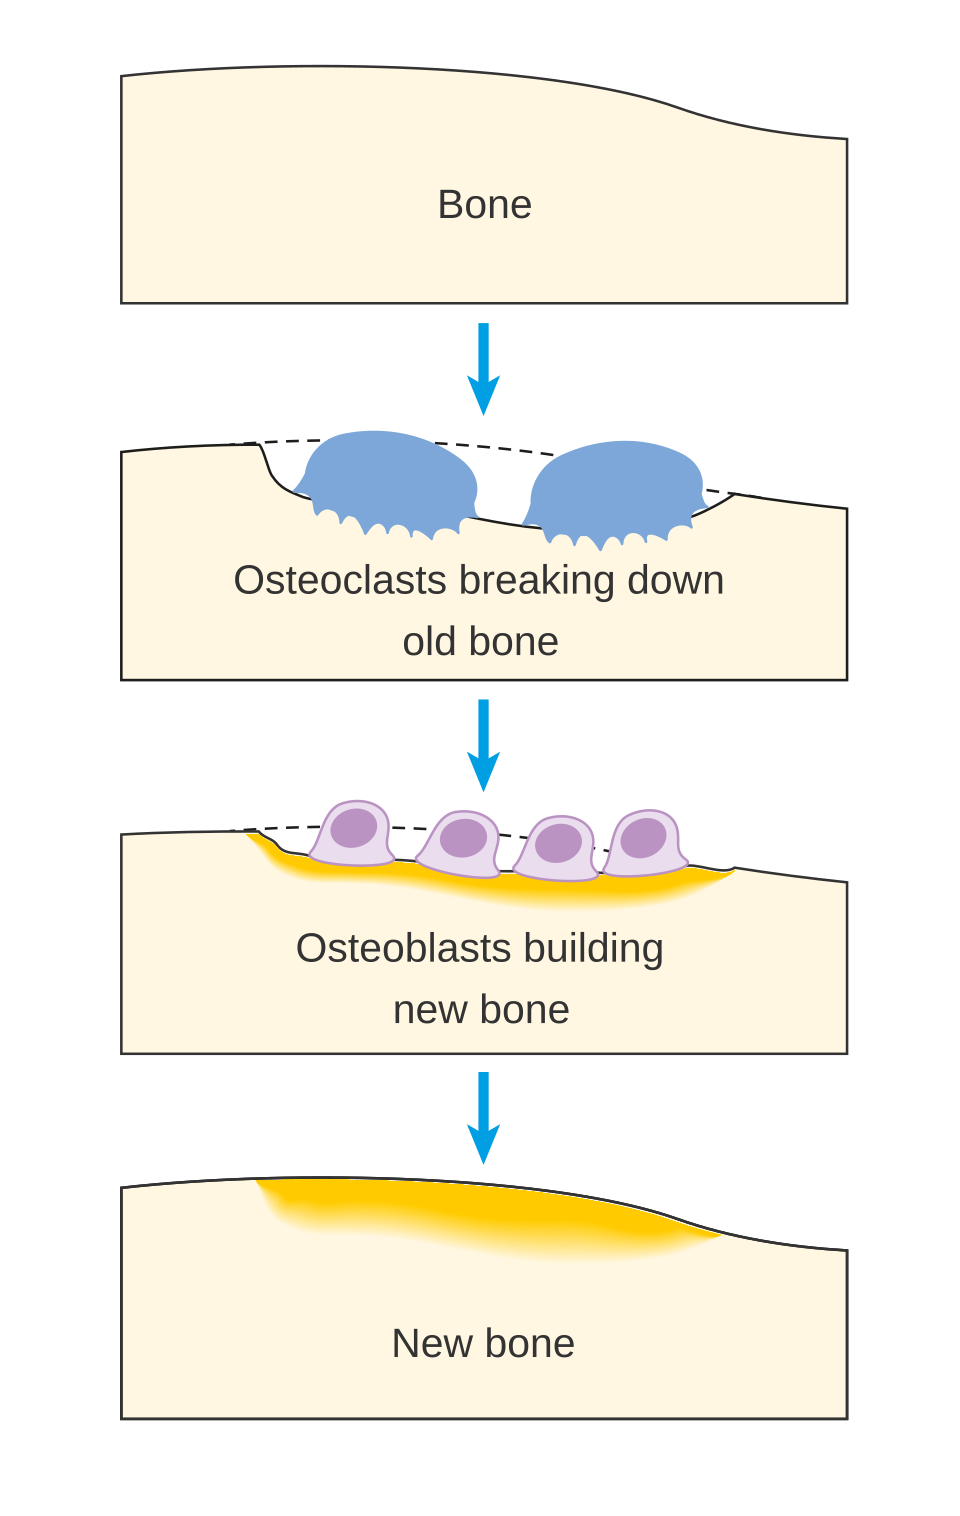
Follow osteoclast resorption and osteoblast replacement, then connect the cycle to antiresorptive therapy and MRONJ. Add osteocyte regulation and the RANK–RANKL–OPG system to this simplified sequence.
Osteoclast resorption and osteoblast formation during bone remodelling · Cancer Research UK (2014; source revision 2016) · CC BY-SA 4.0. Unchanged published raster preview; displayed responsively. Original available from the source.
Assess immune status and anticancer treatment
Ask about the exact treatment, cycle, recent illness and relevant blood results. An old normal count may not describe the anticipated nadir or recovery on the date of surgery. Neutrophils and platelets answer different questions about infection defence and bleeding. Coordinate invasive care with the treating service where necessary; do not invent one universal blood-count threshold for every regimen. Serious infection may produce little pus or fever in an immunocompromised person. A patient who becomes unwell after systemic anticancer treatment may need immediate assessment for neutropenic sepsis, rather than another empirical dental prescription while awaiting routine review.
Understand transplant and interaction risks
Establish the transplanted organ, current function, time since treatment, rejection episodes and immunosuppressants. The medical team may need to advise on timing, infection risk and medicine changes, especially early after transplantation or during intensified treatment. Check proposed antimicrobials and analgesics for interactions: altering immunosuppressant exposure can have major consequences. Do not stop immunosuppression independently or assume every transplant patient requires the same prophylactic antibiotic. Assess the actual dental source and urgency. Agree who will interpret investigations and communicate changes so the patient does not receive contradictory instructions from separate services.
Adapt care to renal, hepatic and respiratory reserve
Renal impairment can alter elimination and make nephrotoxic medicines particularly undesirable; dialysis also introduces treatment timing, anticoagulation and access considerations. Hepatic disease can affect metabolism, protein binding and haemostasis, but a liver-enzyme result alone does not describe synthetic function. Ask about decompensation and bleeding history. Respiratory disease, oxygen needs and obstructive sleep apnoea matter for positioning, sedation and recovery. Use current product information and appropriate clinical advice for prescribing rather than automatically applying standard adult doses. A stable chronic diagnosis is different from acute organ deterioration, which may require medical assessment before elective care.
Identify adrenal risk and steroid effects
Clarify known primary or secondary adrenal insufficiency and current or recent glucocorticoid exposure. Established adrenal insufficiency requires a procedure-specific stress and emergency plan; the relevant guidance for primary disease should not be applied indiscriminately to every person who once used a steroid inhaler. Ask about the steroid emergency card, usual replacement, additional-dose instructions and emergency kit. Do not stop maintenance replacement independently. Vomiting, profound weakness, hypotension or collapse in an at-risk person can indicate adrenal crisis and needs emergency treatment. Chronic steroid exposure can also affect infection, glycaemia and healing, which should be considered alongside adrenal function.
Plan around medication-related bone risk
Identify the exact antiresorptive or other associated medicine, its indication, route and exposure, using current MRONJ risk guidance. Cancer and osteoporosis regimens can carry different risks. Discuss the consequences of untreated disease and alternatives to surgery as well as the risk of impaired healing. Prevention before and during treatment matters, but necessary infection care still needs a route. Do not prescribe a drug holiday independently; interruption may offer uncertain dental benefit and can create medical harm. Agree the surgical setting, technique, information and follow-up according to the individual risk and the relevant guidance.
Distinguish radiotherapy injury and functional burden
Jaw radiotherapy creates a different bone-healing problem from MRONJ, so establish the radiation field and treatment information rather than treating the two labels as interchangeable. Dry mouth, limited opening, mucosal fragility and nutritional problems may further complicate care. Use restorative, oncology or surgical input for invasive treatment in irradiated tissues. Across all conditions, check whether the patient can attend, clean, eat, take medicines and recognise deterioration afterwards. A technically successful procedure can fail in recovery if the support plan ignores fatigue, mobility, cognition or an inability to maintain oral intake.
Coordinate review and escalation
Name the responsible service for outstanding results, medicine decisions and postoperative concerns. Give the patient one consistent set of instructions, including where to seek help for worsening swelling, bleeding, systemic illness or inability to take essential treatment. Stage care where this reduces burden and arrange review when the clinical state or regimen changes. Escalate acute deterioration through the relevant pathway rather than waiting for all elective investigations to return. Record remaining uncertainty honestly. A high-risk label should lead to appropriate expertise and a feasible plan, not indefinite exclusion from dentistry or untreated infection without ownership.
A distinction to remember
Several individually reasonable precautions can conflict; the final plan must resolve the combined risks and specify responsibility.
A patient on chemotherapy feels acutely unwell and has an oral ulcer but little visible swelling. Should a dentist wait for fever before escalating?
Reveal the reasoning
No. Immunosuppression can blunt familiar signs. Assess promptly and arrange immediate medical assessment for possible neutropenic sepsis according to the treatment context. The oncology pathway and current blood-count assessment take priority over routine ulcer treatment or a delayed dental review.
Test your recall
Why is complex comorbidity more than a list of diagnoses?
Show answer
Conditions and medicines interact, so a precaution suitable for one problem can worsen another. Identify the conflicts relevant to the dental procedure and recovery, then agree one coherent plan with clear responsibility for prescribing, timing, investigations and escalation.