
Anticoagulants and antiplatelets
Preventing thrombosis and controlling dental bleeding are both treatment goals. Identify the exact regimen, classify the procedure and prepare local haemostasis before deciding whether any dose timing needs to change.
Quick revision summary
Identify the antithrombotic
Warfarin, direct oral anticoagulants and antiplatelets affect different parts of haemostasis. Identify the indication, exact regimen, additional medicines and patient factors; INR does not measure the effects of DOACs or antiplatelets.
Match the procedure to guidance
Procedural bleeding risk guides the plan. Warfarin with a suitable INR below 4 usually continues; DOAC timing changes are reserved for the relevant higher-risk procedures and must follow the medicine-specific SDCEP schedule.
Secure haemostasis before discharge
Prepare pressure, packing, suturing and observation as appropriate. Confirm bleeding control and provide clear aftercare, contact details and any exact restart instruction; stopping antithrombotics for several days is not a routine dental precaution.
Common mistake
A normal INR does not measure DOAC activity or platelet inhibition, and a DOAC dose adjustment is not permission for an arbitrary multi-day interruption.
Anticoagulants and antiplatelets
Preventing thrombosis and controlling dental bleeding are both treatment goals. Identify the exact regimen, classify the procedure and prepare local haemostasis before deciding whether any dose timing needs to change.
Understand what each medicine changes
Warfarin reduces production of vitamin-K-dependent clotting factors; the INR is useful for its anticoagulant effect. Apixaban, rivaroxaban and edoxaban inhibit factor Xa, while dabigatran inhibits thrombin directly. INR does not quantify their effect. Aspirin and P2Y12 inhibitors such as clopidogrel affect platelet function, which is also not measured by INR. Ask about the indication, actual dosing schedule, recent thromboembolism or coronary intervention, renal function, liver disease and bleeding history. A person taking combined agents or a short initial high-dose DOAC regimen needs more consideration than someone on a stable single medicine.
Vascular spasm, platelet plug and blood-clotting cascade
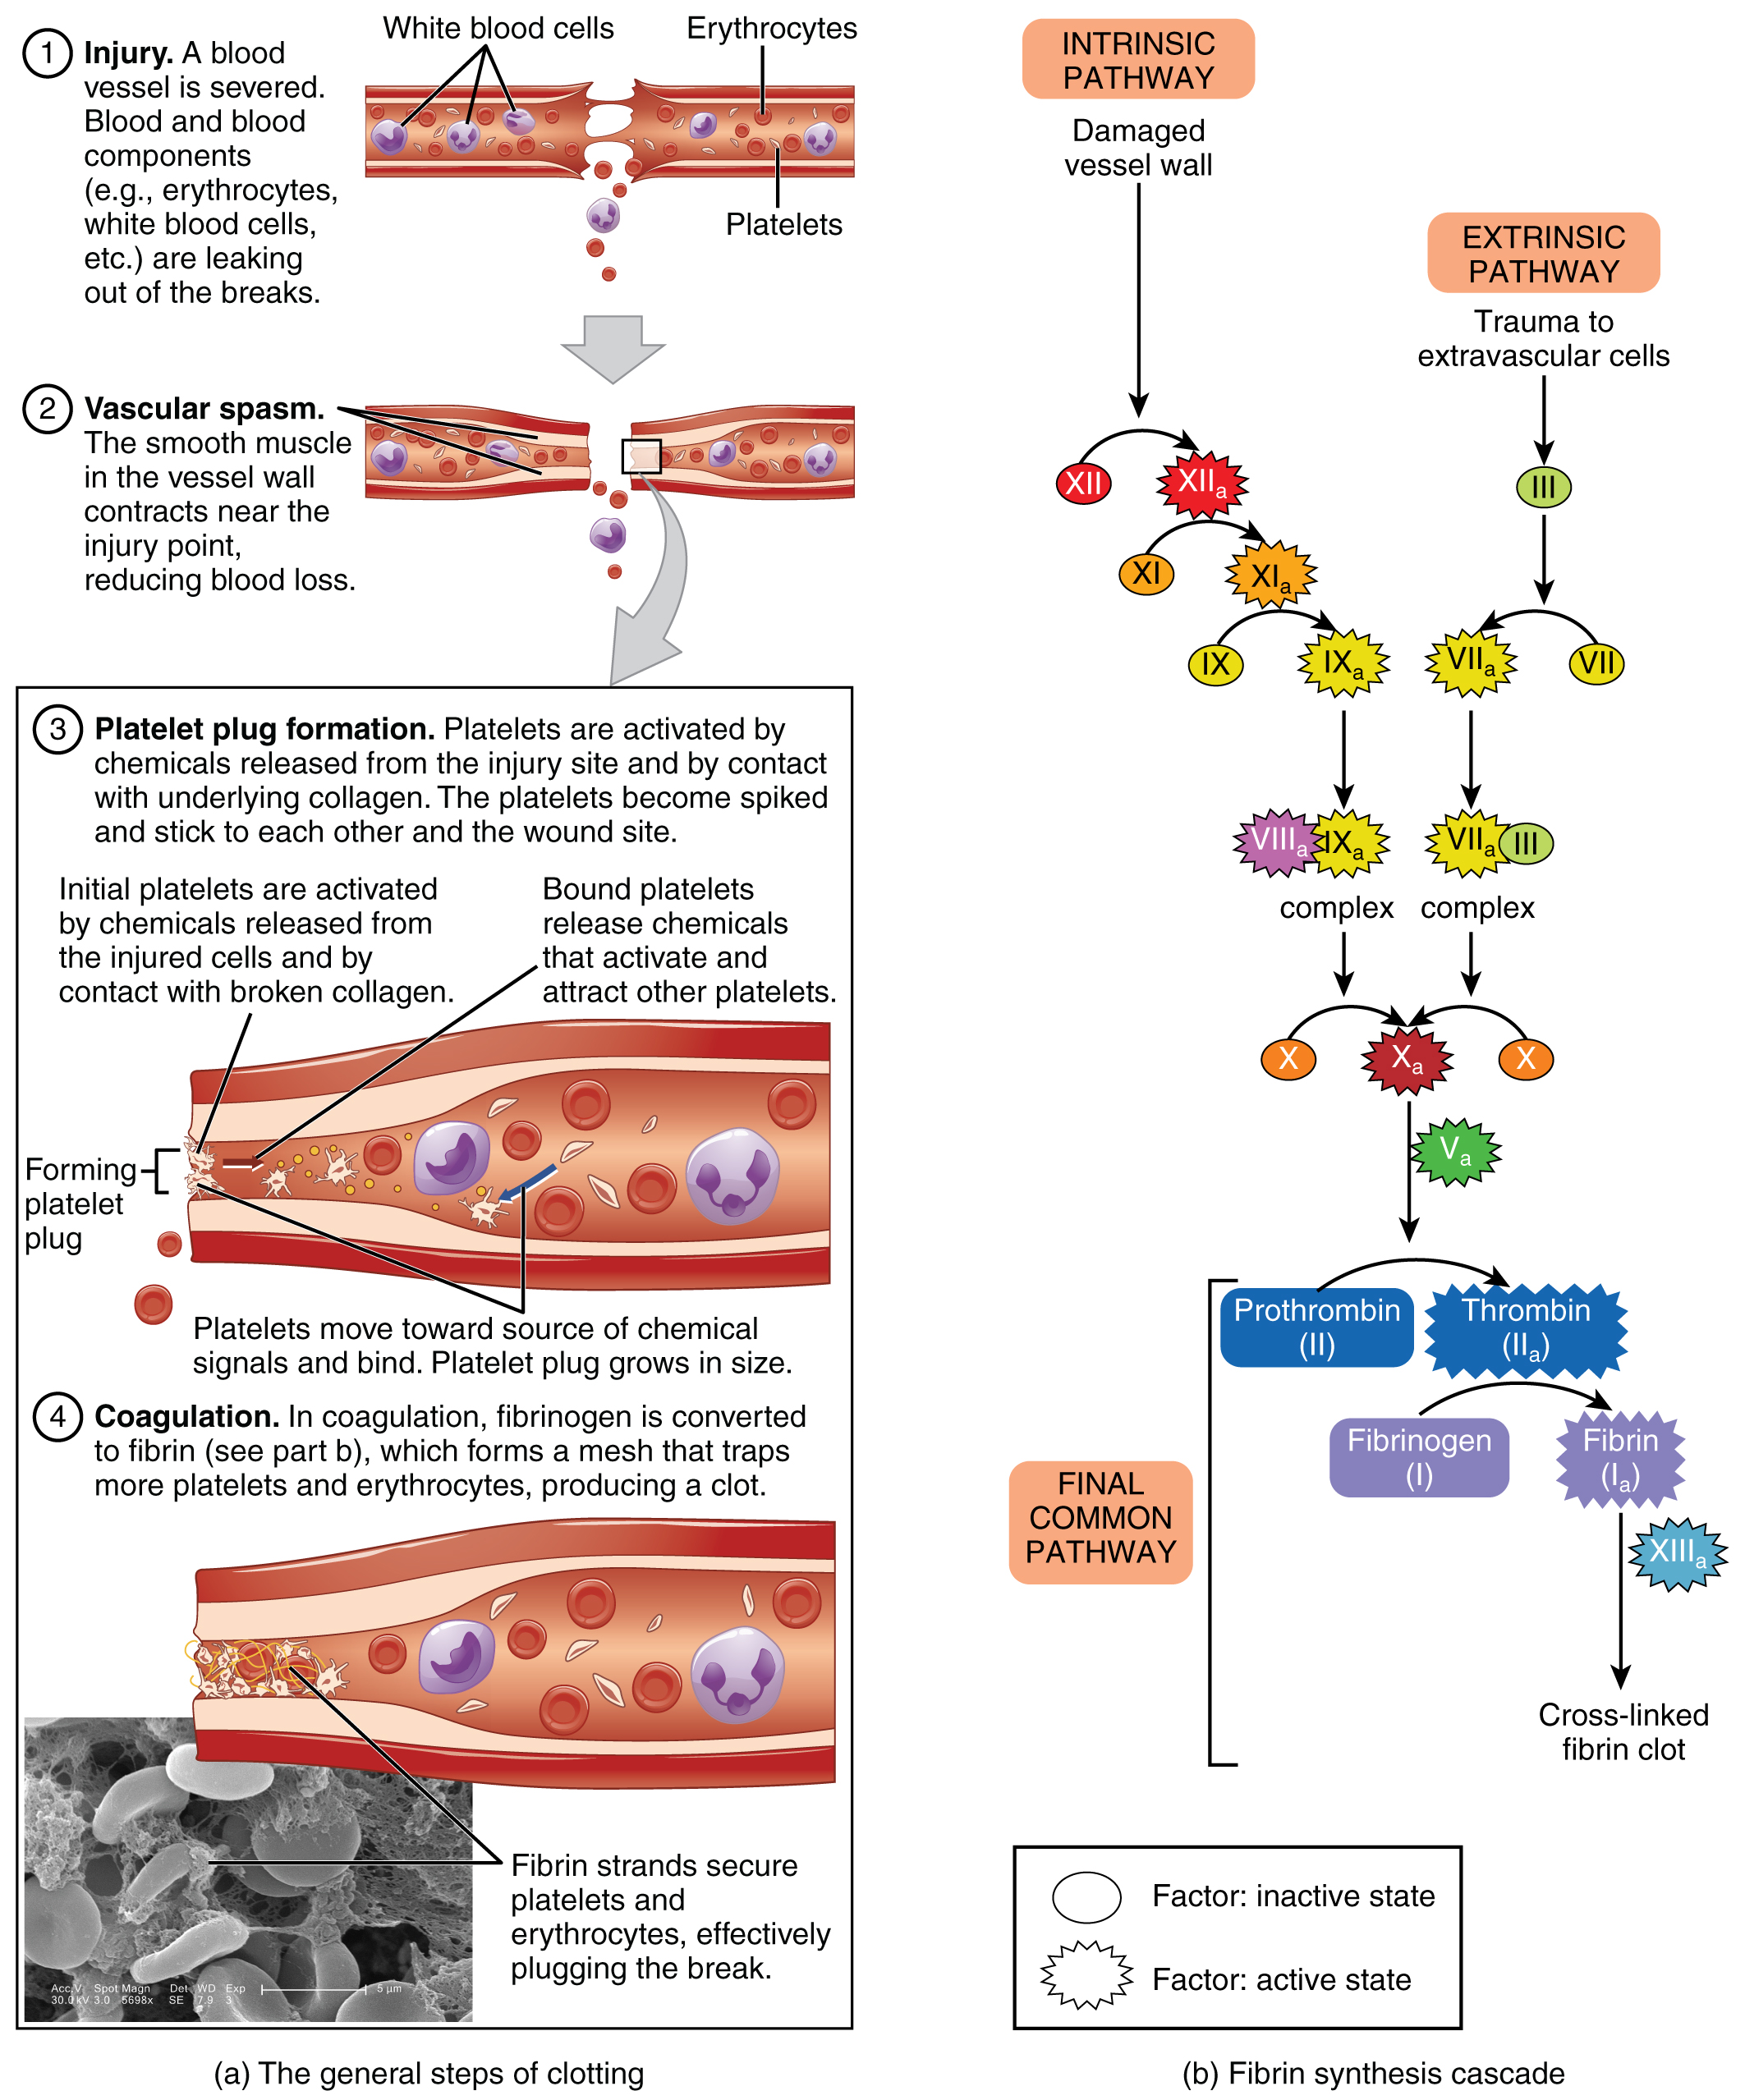
Compare platelet adhesion and plug formation with the development of a fibrin-stabilised clot. Use the labelled intrinsic, extrinsic and common pathways to revise factor deficiencies and laboratory tests. The cascade simplifies the more interconnected process in vivo.
Vascular spasm, platelet plug and blood-clotting cascade · OpenStax College (2013); source micrograph credited to Kevin MacKenzie · CC BY 3.0. Unchanged published image; displayed responsively. Original publication.
Classify the procedure and the person
The relevant SDCEP classification concerns the risk of postoperative bleeding complications. Simple limited extractions differ from multiple adjacent extractions with a large wound, flap surgery, periodontal surgery or biopsy. An apparently small procedure can become more extensive than planned, so anticipate the likely endpoint and whether staging is practical. Separate procedural risk from additional patient factors, including impaired clearance, thrombocytopenia, other medicines and access to urgent help. Tell the patient why the plan balances thrombosis against controllable local bleeding. Do not describe a low-risk procedure as having no possibility of bleeding or reattendance.
Use INR correctly for warfarin
For procedures likely to cause bleeding, obtain INR ideally within 24 hours; SDCEP permits up to 72 hours when control is stable. If INR is below 4, treatment generally proceeds without interrupting warfarin, using local haemostatic measures. If INR is 4 or above, defer invasive care, notify the anticoagulation service or medical practitioner and arrange urgent secondary dental care if treatment cannot wait. A result outside the relevant time window or before a new interacting medicine may be inadequate. Bridging with heparin is not a routine dental solution and must not be independently invented.
Follow the precise DOAC schedule
Low-risk bleeding procedures usually proceed without DOAC interruption. For higher-risk procedures, SDCEP advises missing the morning apixaban or dabigatran dose, or delaying a morning rivaroxaban or edoxaban dose. Once-daily evening rivaroxaban or edoxaban does not need a preoperative change. Restart instructions depend on the regimen and achieved haemostasis: the linked schedule requires at least four hours after haemostasis before the relevant postoperative dose. Do not replace that schedule with a generic instruction to omit treatment for several days. If the morning dose has already been taken, reassess timing and urgency rather than retrospectively applying a missed-dose plan.
Antiplatelets and combinations require different reasoning
Single or dual antiplatelet therapy is usually continued for dental treatment with local bleeding control. Recent coronary stenting makes unplanned interruption particularly hazardous. Ask specifically about aspirin that the patient buys without prescription and whether an anticoagulant is also present. For combined anticoagulant and antiplatelet regimens, therapeutic-dose low-molecular-weight heparin, unusual doses or uncertainty about the indication, obtain medicine-specific advice. Do not use an apparently normal coagulation screen to dismiss platelet inhibition. Confirm any advice with the team responsible for the regimen, and record who will communicate instructions to the patient.
Build haemostasis into the appointment
Choose an appointment that leaves time for observation and access to help, and consider limiting the initial treatment area. Operate atraumatically, identify the bleeding site, use pressure and appropriate absorbable packing, and strongly consider suturing where indicated. Check haemostasis before discharge. The patient needs clear advice about disturbing the clot, what sustained pressure means, what bleeding warrants urgent review and which service to contact. Give explicit dose instructions if a DOAC adjustment was made. A successful extraction is incomplete if the patient leaves with active bleeding or conflicting medicine advice.
Prescribe and review with bleeding in mind
Check interactions and avoid adding avoidable bleeding risk. NSAIDs can increase gastrointestinal and other bleeding risks; some antimicrobials interact with warfarin, so drug choice and monitoring may need adjustment. Review persistent bleeding clinically rather than telling the patient to stop treatment over the telephone without assessment. Look for local causes and systemic illness as well as the anticoagulant. Severe uncontrolled bleeding or physiological compromise needs emergency escalation. When local measures achieve control, preserve the antithrombotic plan unless a responsible clinician identifies a justified change and communicates a clear restart strategy.
A distinction to remember
A normal INR does not measure DOAC activity or platelet inhibition, and a DOAC dose adjustment is not permission for an arbitrary multi-day interruption.
A patient taking evening rivaroxaban is booked for a higher-risk extraction. Should they omit the previous evening dose?
Reveal the reasoning
Not under the standard SDCEP higher-risk schedule for once-daily evening rivaroxaban. Confirm the actual regimen and patient factors, plan local haemostasis and explain that the postoperative evening dose must be no earlier than four hours after haemostasis.
Guidance to read alongside this chapter
Test your recall
Which antithrombotic medicine is monitored using INR?
Show answer
INR is used for warfarin and other vitamin K antagonists. It does not quantify the anticoagulant effect of a DOAC or the effect of aspirin or clopidogrel, so a normal result cannot substitute for identifying the actual medicine.