
Orofacial granulomatous disease
Persistent lip swelling and granulomatous inflammation require a clinical differential, directed investigation and follow-up for disease beyond the mouth.
Quick revision summary
Recognise a pattern of persistent swelling
Orofacial granulomatous disease is a clinical and pathological problem, not one diagnosis established by a swollen lip. Persistent or recurrent lip enlargement, mucosal tags, cobblestoning, linear ulceration and gingival swelling can form a recognisable pattern.
Match treatment to the established problem
Treatment aims to control symptoms and functional impact while addressing any identified systemic condition. Local anti-inflammatory treatment or, in more severe disease, systemic medicines may be considered by the appropriate specialist.
Review disease activity and treatment burden
Monitor swelling, mucosal disease, pain, eating, oral hygiene and the patient’s own priorities. Record benefits and adverse effects of treatment.
Common mistake
Do not equate the presence of oral granulomas with a diagnosis of Crohn’s disease.
Orofacial granulomatous disease: oral findings and systemic assessment
Persistent lip swelling and granulomatous inflammation require a clinical differential, directed investigation and follow-up for disease beyond the mouth.
Recognise a pattern of persistent swelling
Orofacial granulomatous disease is a clinical and pathological problem, not one diagnosis established by a swollen lip. Persistent or recurrent lip enlargement, mucosal tags, cobblestoning, linear ulceration and gingival swelling can form a recognisable pattern. Record duration, fluctuation, pain, fissuring, distribution and any effect on eating, speech or confidence. Photographs with consent help document change.
Distinguish this persistent pattern from sudden swelling with tongue or throat involvement, which needs an acute airway assessment. Dental infection, local trauma, contact reactions, angioedema and other causes of swelling remain relevant according to the history. Do not assume that every recurrent swollen lip is OFG.
Oral mucosa: epithelium, basement membrane and lamina propria
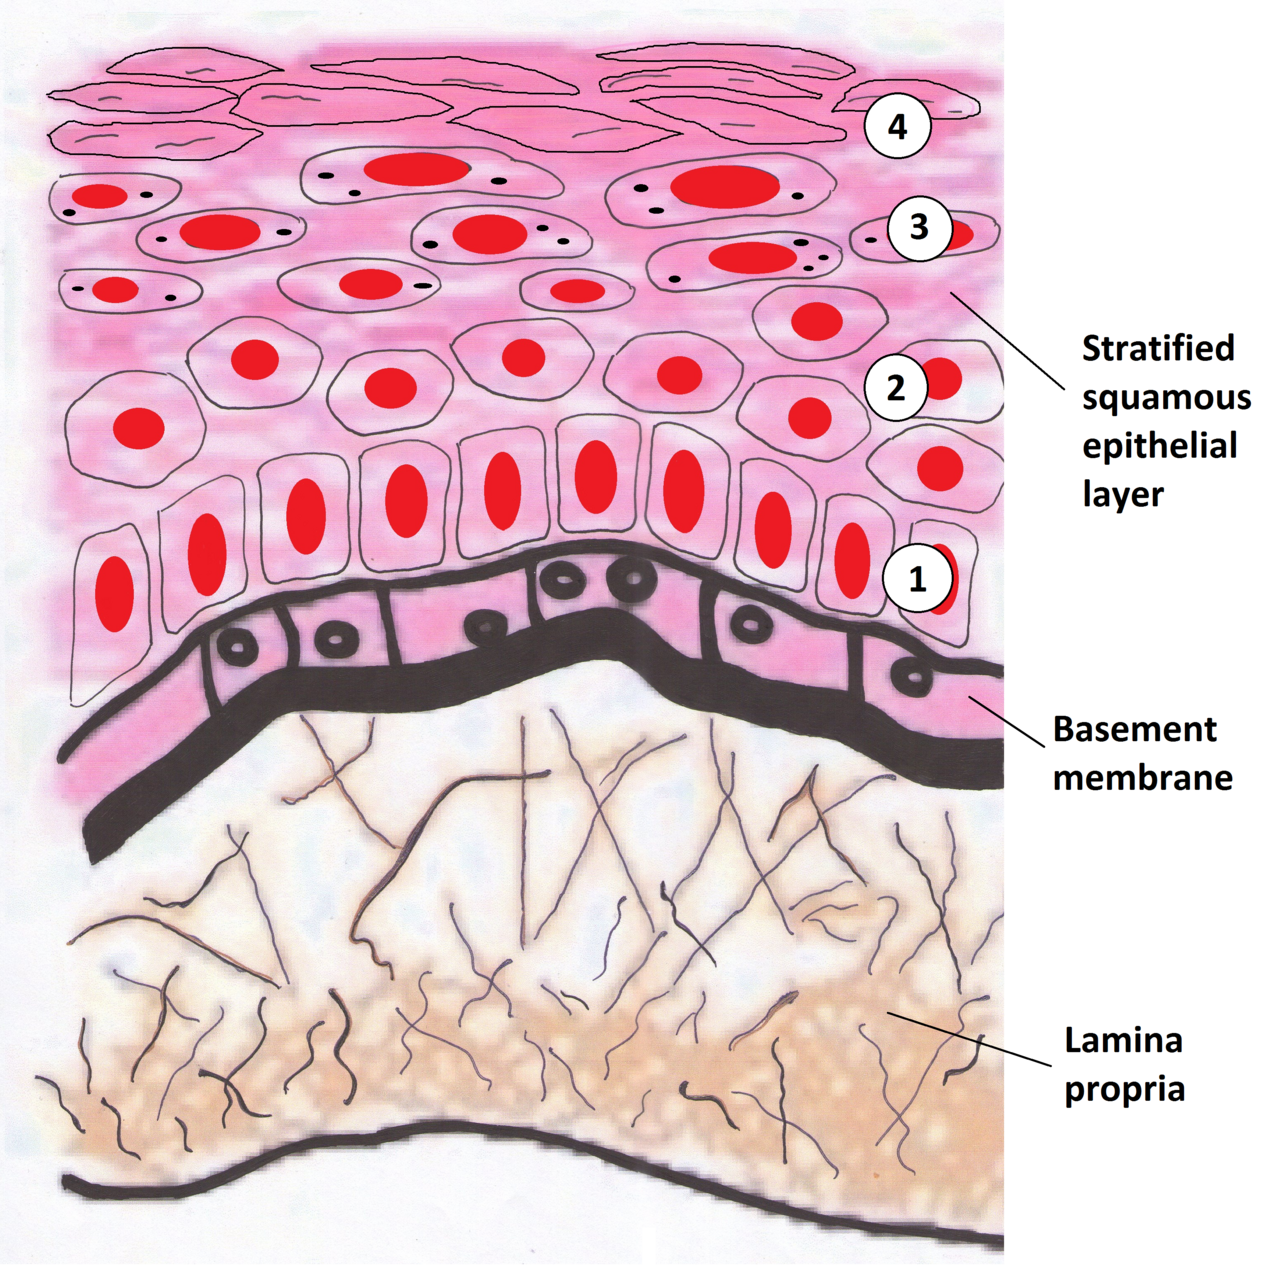
Identify the epithelium, basement membrane and lamina propria. Relate the epithelial–stromal interface to in-situ disease and invasion. This drawing represents a keratinising surface; oral sites have different keratinisation patterns. Use the printed anatomical names for revision.
Oral mucosa: epithelium, basement membrane and lamina propria · Wiki-minor (own work, 2011) · CC BY-SA 3.0. Unchanged published raster preview; displayed responsively. Original available from the source.
Interpret granulomas in their clinical context
A granuloma is an organised collection of inflammatory cells. Finding granulomas in oral tissue narrows the differential but does not identify a single cause. Consider Crohn’s disease, sarcoidosis, relevant infections and foreign material. The term idiopathic orofacial granulomatosis is generally used when a recognised systemic cause has not been established; terminology can vary between services and publications.
Granulomas may be patchy, so their absence in a limited specimen does not resolve every clinical question. The sampling site, depth and clinical information matter. Discuss the result with oral medicine and pathology rather than interpreting a phrase in isolation. Further investigation should follow the findings and plausible differential, not an indiscriminate panel of tests.
Look beyond the mouth
Ask about abdominal pain, persistent diarrhoea, blood in stool, weight change, nutritional problems and, in children, growth. Respiratory, skin and eye symptoms may also direct assessment. The history should identify whether oral findings could be part of a wider inflammatory or infectious condition and whether urgent assessment is needed.
Specialist investigation may include blood or stool tests, targeted imaging and gastroenterology assessment when appropriate. A person can develop systemic features after the initial oral presentation, so a normal initial assessment does not end the need to review new symptoms. Record the basis for the current diagnosis and who is responsible for ongoing follow-up.
Match treatment to the established problem
Treatment aims to control symptoms and functional impact while addressing any identified systemic condition. Local anti-inflammatory treatment or, in more severe disease, systemic medicines may be considered by the appropriate specialist. Treatment response does not by itself establish the original diagnosis. Consider relevant infection and medicine risks before immunosuppression.
Some patients are offered a supervised dietary approach, including review of cinnamon and benzoate exposure. This should be guided by an experienced team and dietitian where appropriate, particularly for children or anyone with nutritional concerns. A reported food association is not proof of allergy, and broad unsupervised restriction can create additional harm.
Review disease activity and treatment burden
Monitor swelling, mucosal disease, pain, eating, oral hygiene and the patient’s own priorities. Record benefits and adverse effects of treatment. Persistent swelling can affect confidence even when it is painless, and this deserves discussion rather than being dismissed as cosmetic.
Ensure that the patient knows how to report new gastrointestinal or other systemic symptoms and whom to contact about a flare. Maintain dental prevention and address plaque-related inflammation alongside the specialist plan. At review, reconsider the diagnosis when the distribution, symptoms or course changes. Chronicity does not make every future symptom part of the same condition.
A distinction to remember
Do not equate the presence of oral granulomas with a diagnosis of Crohn’s disease.
A teenager has persistent lip swelling, buccal cobblestoning and new abdominal pain. What should the oral findings prompt?
Reveal the reasoning
Assess the oral differential and arrange appropriate oral medicine and medical evaluation for possible systemic disease, including Crohn’s disease. Ask about bowel symptoms, weight and growth. Neither the appearance nor granulomas alone establishes the systemic diagnosis.
Guidance to read alongside this chapter
Test your recall
Does a granuloma alone diagnose Crohn's disease?
Show answer
No; it needs clinical and investigative correlation.