
Failure and retreatment
Apical surgery addresses a selected cause of persistent endodontic disease. It does not rescue a tooth with every kind of structural or restorative failure.
Quick revision summary
Diagnose the failure before choosing surgery
Review symptoms, previous treatment, restorability, periodontal support, coronal seal, root anatomy and the current radiographic findings. Consider missed anatomy, persistent intraradicular infection, extraradicular factors, procedural problems and fracture.
Identify what could realistically be corrected
Review the original diagnosis, treatment record, coronal restoration and the course of symptoms. Look for missed anatomy, inadequate disinfection, leakage, procedural problems, periodontal disease and fracture.
Compare review, orthograde treatment, surgery and extraction
Orthograde retreatment can address problems within the canal system but may require removal of restorative components. Apical surgery addresses the root-end region and requires appropriate access, anatomy and a restorable tooth.
Common mistake
Retreatment should address an identified problem in a tooth with a realistic overall prognosis.
Periapical surgery and endodontic decision-making
Apical surgery addresses a selected cause of persistent endodontic disease. It does not rescue a tooth with every kind of structural or restorative failure.
Diagnose the failure before choosing surgery
Review symptoms, previous treatment, restorability, periodontal support, coronal seal, root anatomy and the current radiographic findings. Consider missed anatomy, persistent intraradicular infection, extraradicular factors, procedural problems and fracture. A radiolucency after treatment must be interpreted with timing and prior images rather than automatically called failure.
Compare nonsurgical retreatment, apical surgery, extraction and observation where appropriate. Accessibility of the canal system, restoration complexity, anatomy and patient priorities change the options. A vertical root fracture or an unrestorable tooth usually changes the prognosis substantially; surgery at the apex does not fix a defective coronal or structural foundation.
Tooth & supporting tissues
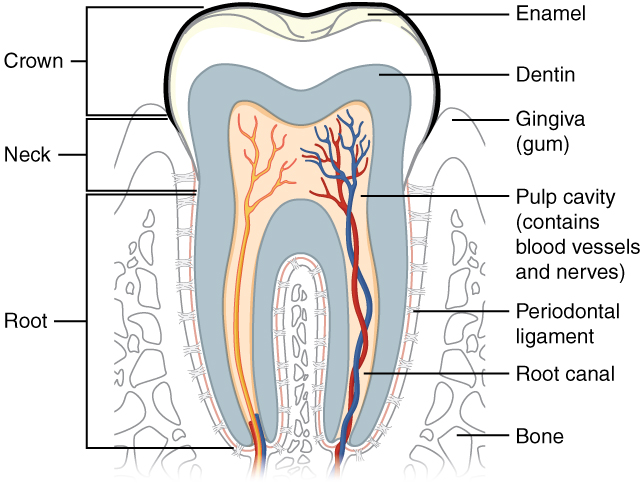
Trace the pulp and root canal to the apical region, then identify the periodontal ligament and supporting bone. Relate these structures to avulsion, apical pathology and extraction. The original uses the spelling “dentin”; cementum is not separately labelled.
Tooth & supporting tissues · OpenStax College · CC BY 3.0. Original image; displayed at a responsive size. Original publication.
Components and adjacent risks
| Component | Purpose | Planning point |
|---|---|---|
| Access / flap | Expose the apical region while preserving tissue | Gingival margin, papilla, aesthetic zone and blood supply matter. |
| Root-end resection | Remove selected apical anatomy / pathology | Retained root length and periodontal support affect prognosis. |
| Root-end preparation | Create a suitable space for an apical seal | Anatomy and instrument control are important. |
| Root-end filling | Provide an appropriate seal with a suitable material | Handling and biological properties affect the choice. |
| Tissue specimen | Confirm associated pathology when indicated | Do not presume every apical lesion is an uncomplicated inflammatory cyst. |
| Anatomical protection | Avoid injury to nerves, sinus and adjacent roots | Use adequate localisation and justified imaging. |
Outcome and follow-up
Clinical comfort, tooth function and radiographic change over time all contribute to outcome assessment. Persistent pain, swelling or a sinus warrants reassessment. A single postoperative image cannot describe the whole healing trajectory.
Document the indication, alternatives, operative findings, materials and specimen result. Explain the possibility of persistent disease and the implications of later extraction or rehabilitation. A surgical endpoint should be judged against the original clinical problem, not only whether the root-end filling looks neat.
Identify what could realistically be corrected
Review the original diagnosis, treatment record, coronal restoration and the course of symptoms. Look for missed anatomy, inadequate disinfection, leakage, procedural problems, periodontal disease and fracture. Persistent pain may also have a non-endodontic source. Repeating canal treatment will not solve a mechanism that was never odontogenic.
Assess access through crowns or posts, remaining tooth tissue and the consequences of dismantling the restoration. A technically possible retreatment may have a poor overall prognosis if the tooth cannot be restored afterwards. Explain which finding makes retreatment likely to help, which uncertainties remain and what alternatives exist. Refer before aggressive removal or retrieval creates avoidable structural damage.
Separated endodontic instrument: a complication example
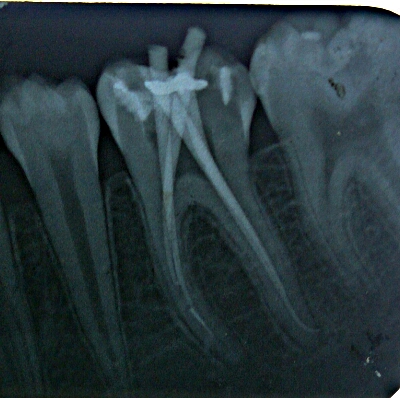
The author identifies a separated instrument in the mesial root canal. Compare the short radiopaque fragment with the longer instruments; this illustrates a complication, not an ideal treatment endpoint.
Broken endodontic file in mesial root canal.jpg · Dr.mohan m.muthal · CC BY-SA 4.0. Image reproduced without alteration; original marks and any embedded credits retained.
Compare review, orthograde treatment, surgery and extraction
Orthograde retreatment can address problems within the canal system but may require removal of restorative components. Apical surgery addresses the root-end region and requires appropriate access, anatomy and a restorable tooth. Extraction removes the tooth but introduces replacement and functional considerations. Monitoring may be appropriate in selected cases with a favourable healing trend and a clear review plan.
These options are not a fixed ladder that every patient must climb. Consider the disease mechanism, previous treatment quality, structural and periodontal prognosis, patient priorities and the risks of each route. Obtain appropriate specialist assessment for complex anatomy or uncertain diagnosis. Record the basis of the recommendation and the plan for judging outcome, including what would trigger an earlier return.
A distinction to remember
Retreatment should address an identified problem in a tooth with a realistic overall prognosis.
Why should restorability be checked before periapical surgery?
Reveal the reasoning
Even successful apical treatment cannot provide a durable outcome for an unrestorable tooth. The decision needs both endodontic and restorative prognosis.
Guidance to read alongside this chapter
Test your recall
What must be excluded before retreating a repeatedly symptomatic tooth?
Show answer
A vertical root fracture and a non-endodontic source of pain.