
Access and anatomy
Find the anatomy while preserving enough tooth tissue for the restoration that must follow.
Quick revision summary
Use external and internal anatomy to guide access
Access should allow canal identification and controlled instrumentation without excessive removal of supporting tissue. The chamber floor, colour change, developmental lines and orifice positions provide clues.
Read the tooth before entering the chamber
Look at root number, curvature, crown angulation and the relationship between an existing restoration and the underlying tooth. The visible crown may not indicate the long axis of a tilted tooth.
Recognise when access risk has changed
Calcification, previous access, crowns and unusual anatomy can make the anticipated path unreliable. Reassess depth and direction when the chamber is not found where expected.
Common mistake
The restored crown’s shape may not reveal the root axis or the position of the pulp chamber.
Access and canal anatomy
Find the anatomy while preserving enough tooth tissue for the restoration that must follow.
Use external and internal anatomy to guide access
Access should allow canal identification and controlled instrumentation without excessive removal of supporting tissue. The chamber floor, colour change, developmental lines and orifice positions provide clues. Restoration and calcification can obscure landmarks. Review preoperative images and tooth alignment, and use illumination and magnification where available. Assuming every tooth has textbook anatomy creates avoidable missed canals and perforations.
Balance access conservatism with effective treatment. An extremely restricted opening can impede location, irrigation and instrumentation; a large unsupported access can weaken the tooth. Rubber dam protects against contamination and instrument or irrigant exposure. If anatomy is unclear, stop and reconsider rather than drilling deeper on an assumed axis. Referral may be appropriate for calcified, unusual or previously altered anatomy.
Tooth & supporting tissues
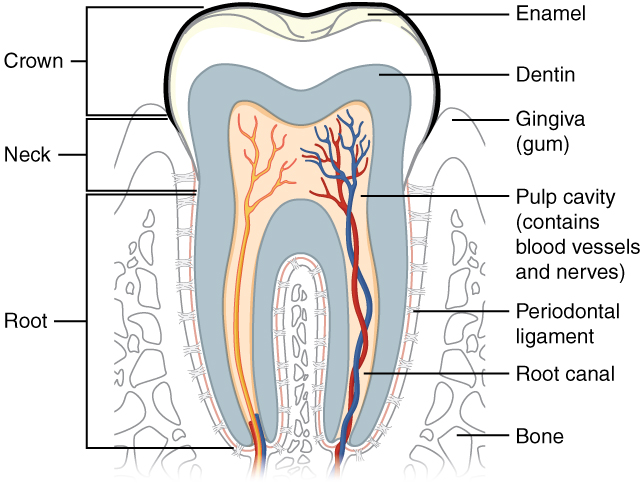
Trace the pulp and root canal to the apical region, then identify the periodontal ligament and supporting bone. Relate these structures to avulsion, apical pathology and extraction. The original uses the spelling “dentin”; cementum is not separately labelled.
Tooth & supporting tissues · OpenStax College · CC BY 3.0. Original image; displayed at a responsive size. Original publication.
Key distinctions in practice
| Finding or option | What it means | Clinical consequence |
|---|---|---|
| Chamber floor | Anatomical guide to canal location | Use colour and grooves without indiscriminate troughing. |
| Calcification | Obscures expected landmarks | Plan the risk and consider specialist assistance. |
| Missed canal | Potential persistent infection source | Reassess anatomy in failure. |
| Perforation | Communication with supporting tissues | Recognise and manage promptly. |
Read the tooth before entering the chamber
Look at root number, curvature, crown angulation and the relationship between an existing restoration and the underlying tooth. The visible crown may not indicate the long axis of a tilted tooth. Estimate chamber position from suitable imaging and external landmarks before cutting. Removing caries or a defective restoration can clarify restorability and expose useful orientation information.
The cervical outline and chamber floor help organise the search for orifices. Developmental grooves and differences in colour can guide inspection, but aggressive troughing risks removing the chamber floor. Additional canals may be present even when the initial radiograph appears simple. Use magnification and illumination as aids to careful interpretation, not as permission for blind dentine removal.
Root-filled molar: trace the visible canals
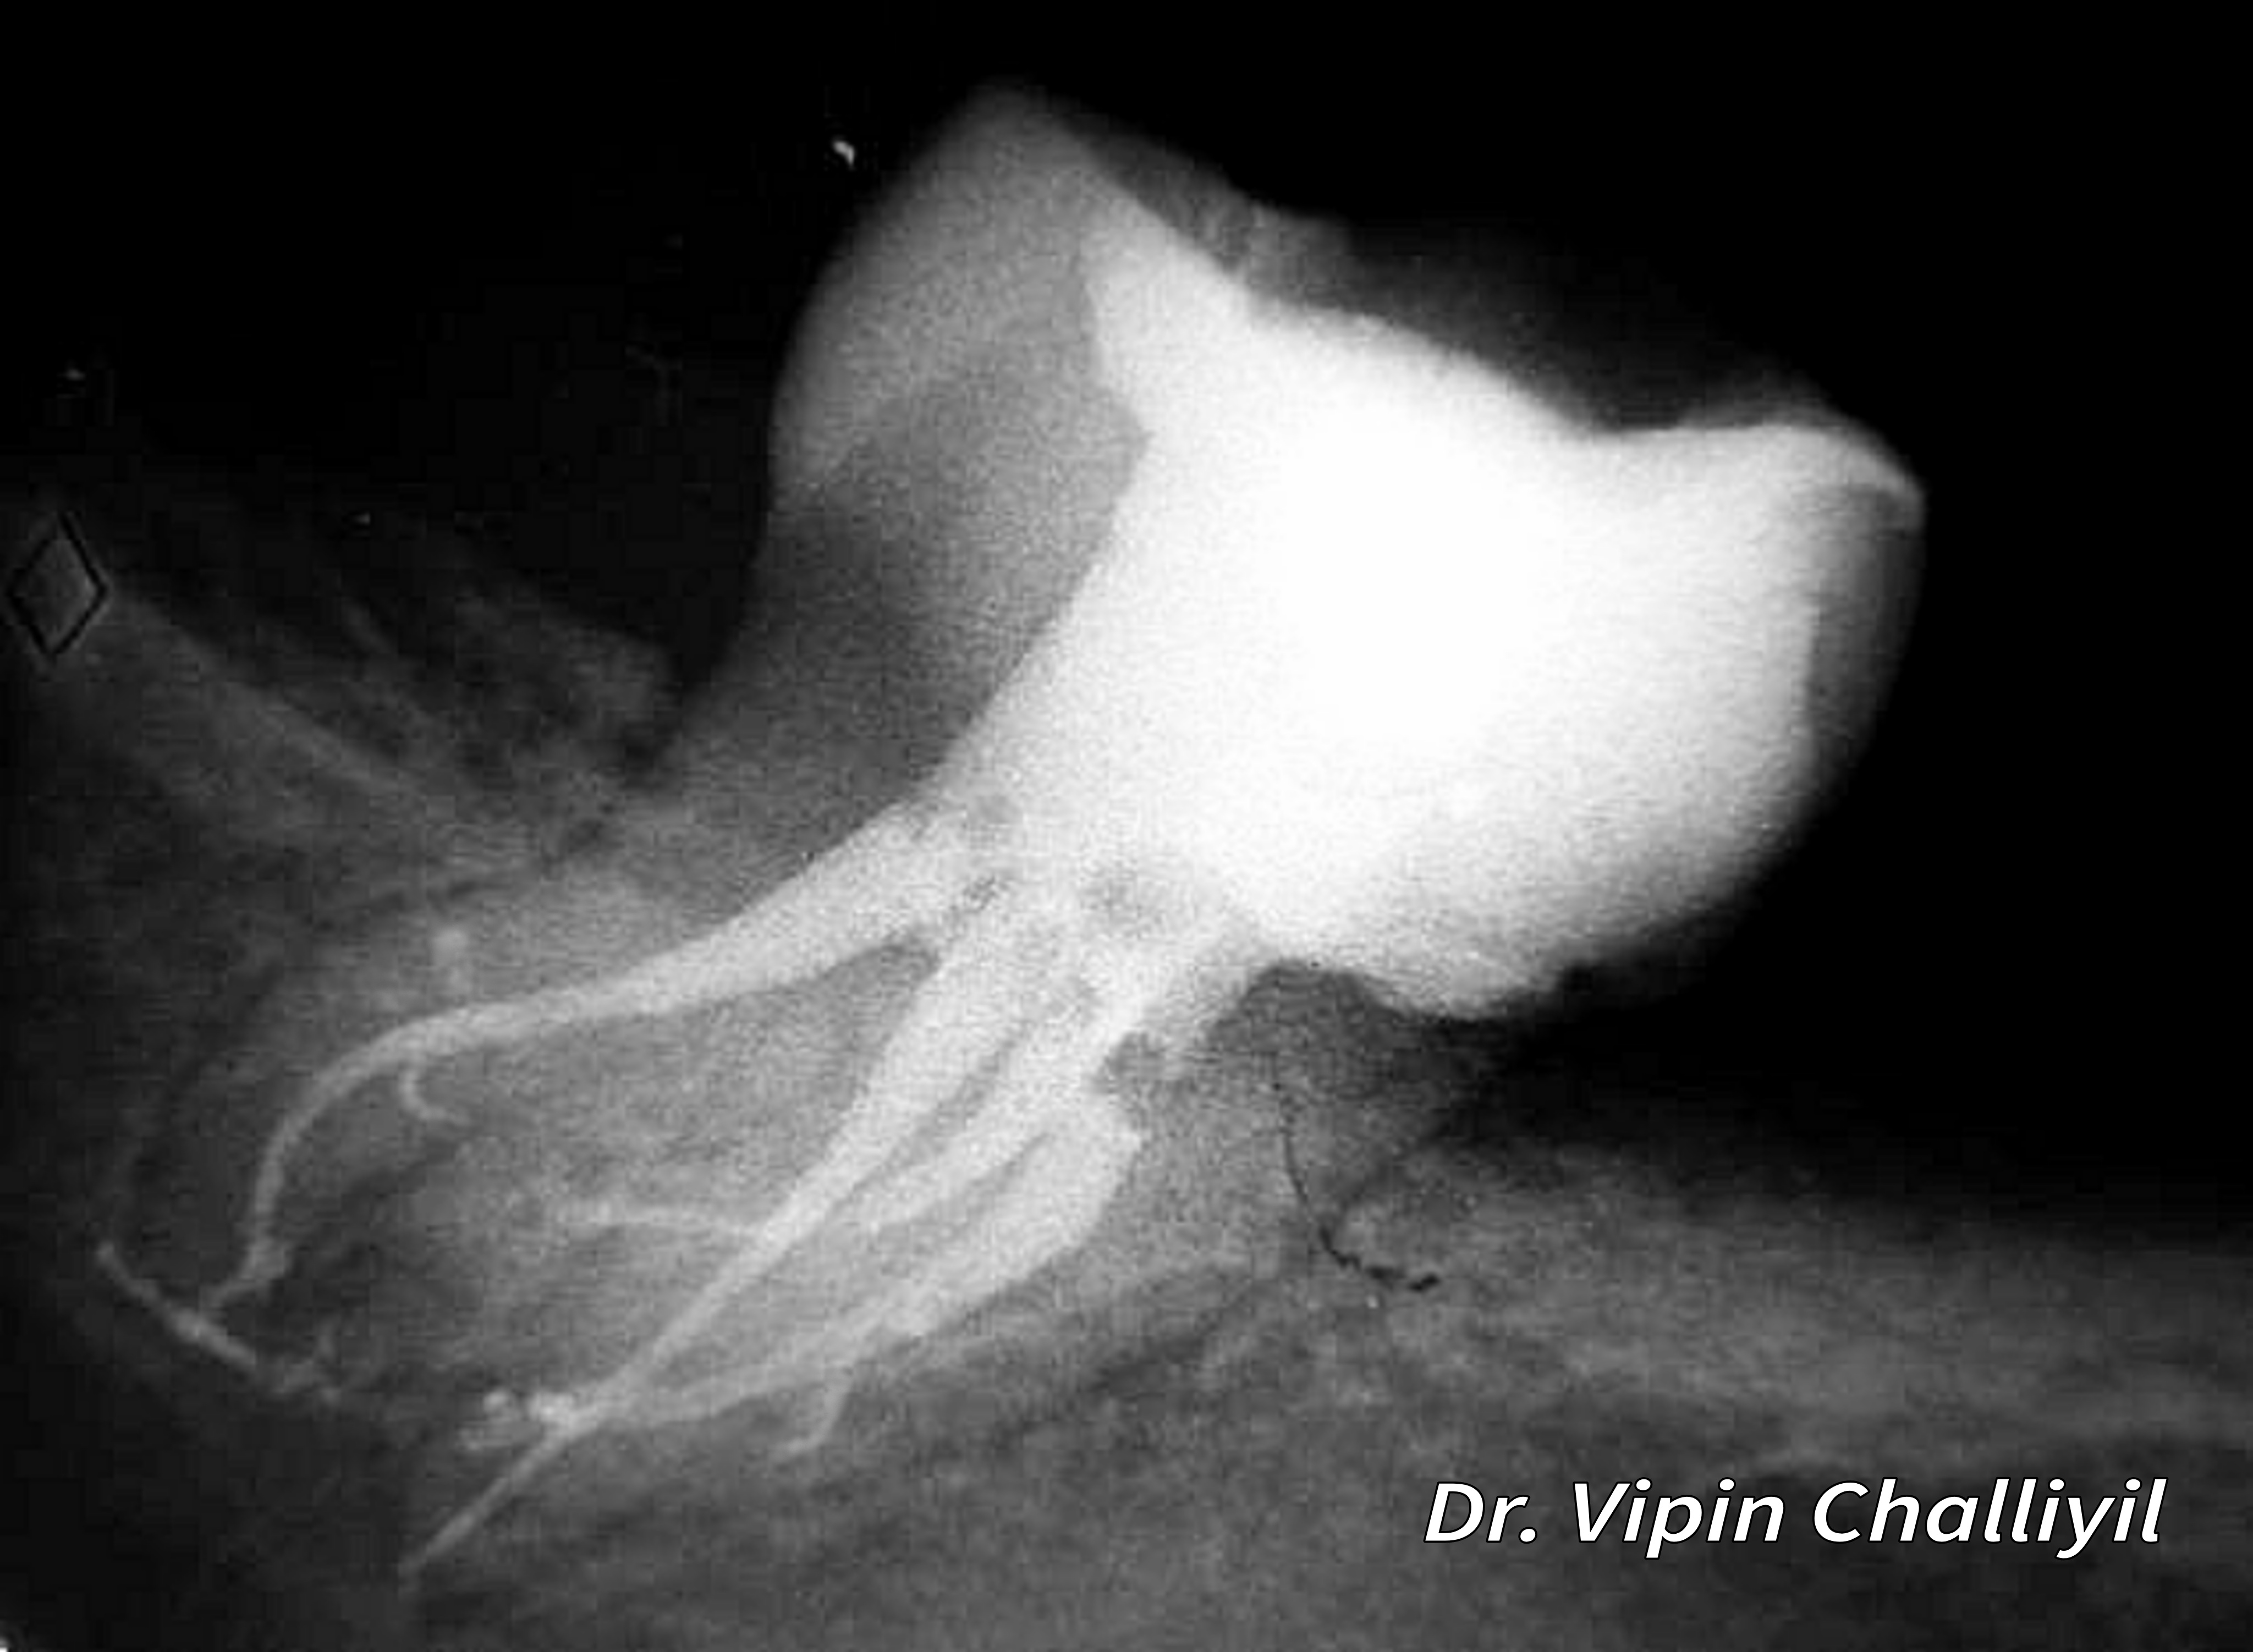
Follow the radiopaque root fillings and the surrounding root outlines. The image illustrates canal anatomy after treatment; radiographic appearance alone does not establish disinfection or healing.
Root canal treatment of lone standing molar.jpg · Challiyan (Dr Vipin Challiyil) · CC BY-SA 4.0. Image reproduced without alteration; original marks and any embedded credits retained.
Recognise when access risk has changed
Calcification, previous access, crowns and unusual anatomy can make the anticipated path unreliable. Reassess depth and direction when the chamber is not found where expected. An unexplained bleeding point, inconsistent canal path or suspected communication with periodontal tissues should prompt assessment for perforation. Continuing to drill to find a canal may enlarge an injury.
Referral is particularly valuable before extensive damage has occurred. Send preoperative and current images and an honest description of what has been attempted. Once canals are located, confirm that access permits controlled instrumentation and irrigation without unnecessarily weakening the tooth. The best outline is determined by the anatomy and treatment needs of this tooth, not by copying a small or large cavity from a demonstration.
A distinction to remember
The restored crown’s shape may not reveal the root axis or the position of the pulp chamber.
Why can an overly small access cavity be harmful despite preserving tooth tissue?
Reveal the reasoning
It may prevent adequate identification, irrigation and instrumentation. Tissue preservation must still permit effective and safe treatment.
Guidance to read alongside this chapter
Test your recall
Why inspect the pre-operative radiograph closely?
Show answer
It informs root number, curvature, calcification and procedural risk.