
Third molars
Impaction describes position, not a diagnosis that automatically requires extraction. Third-molar assessment brings together disease, effects on the second molar, surgical anatomy and patient preferences. Learn how classification and imaging inform the choice between observation, complete removal and selected coronectomy without substituting for clinical judgement.
Quick revision summary
Establish the indication
Assess pericoronitis, caries, periodontal disease, resorption, pulpal or periapical disease and associated follicular pathology. Examine the distal surface and periodontal support of the second molar as well as the third molar.
Compare observation and complete removal
Observation includes clinical review of symptoms, eruption, hygiene and neighbouring disease, with imaging when justified. It is a documented plan, not abandonment. Explain what changes should prompt reassessment, including repeated inflammation, new decay or adjacent tooth disease.
Plan recovery and reassessment
Select anaesthetic and setting through medical, anatomical and psychological assessment. Give suitable analgesic and hygiene advice, a bleeding plan and clear emergency contacts. Antibiotics are not automatically required merely because the operation is surgical; infection risk and current prescribing guidance determine their use.
Common mistake
A high-risk panoramic appearance establishes a risk discussion, not an indication for removal. Coronectomy is a selected treatment option with its own future-care implications.
Third molars: indications, anatomy and treatment choices
Impaction describes position, not a diagnosis that automatically requires extraction. Third-molar assessment brings together disease, effects on the second molar, surgical anatomy and patient preferences. Learn how classification and imaging inform the choice between observation, complete removal and selected coronectomy without substituting for clinical judgement.
Establish the indication
Assess pericoronitis, caries, periodontal disease, resorption, pulpal or periapical disease and associated follicular pathology. Examine the distal surface and periodontal support of the second molar as well as the third molar. Symptoms may underestimate disease, while pain near an impacted tooth may have another cause.
NICE TA1 advises against routine prophylactic removal of pathology-free impacted wisdom teeth. A first episode of pericoronitis is generally insufficient unless particularly severe; subsequent episodes and demonstrated pathology change the discussion. Record the actual indication, alternatives and expected benefit rather than writing only “impacted tooth”.
Mandibular landmarks
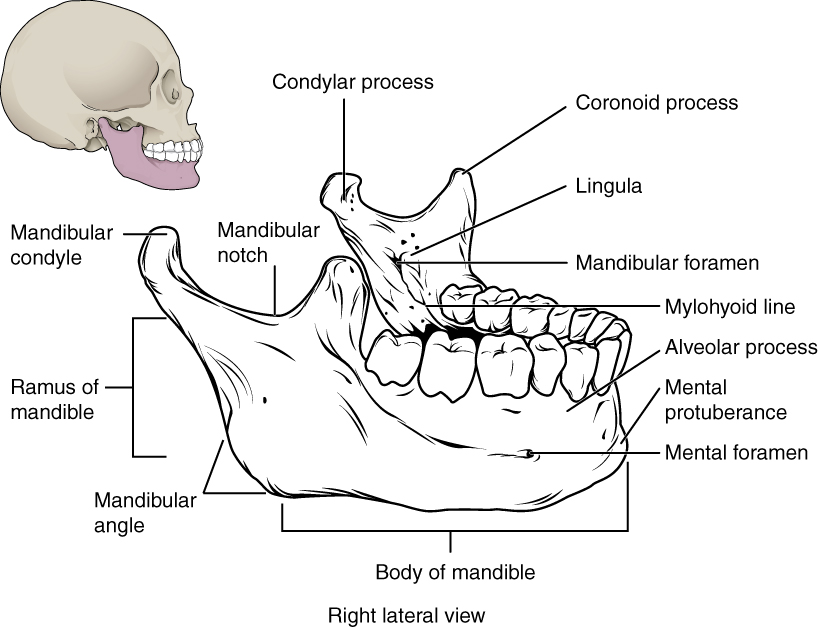
Locate the mental and mandibular foramina, lingula and mylohyoid line. The mandibular foramen, lingula and mylohyoid line are medial landmarks; this schematic brings several surfaces together. Relate the landmarks to nerve risk and fracture assessment.
Mandibular landmarks · OpenStax College · CC BY 3.0. Original image; displayed at a responsive size. Original publication.
Describe position and difficulty
Winter’s classification describes angulation relative to the second molar, including mesioangular, horizontal, vertical and distoangular positions. Pell and Gregory describes depth and available space relative to the ramus. These systems communicate part of the anatomy, but they do not capture every determinant of difficulty.
Root curvature, divergence, age, bone density, opening, crown access, periodontal condition and operator experience modify the risk. Deep position may require greater access or bone removal; a superficially positioned tooth with unfavourable roots can still be challenging. Assess upper third molars for sinus, tuberosity and displacement risks.
Interpret imaging with a specific question
Panoramic signs suggesting a close canal relationship include root darkening, interruption of the canal’s cortical outline, diversion or narrowing of the canal and root changes. These findings indicate concern rather than proving nerve contact or predicting an inevitable injury. Review associated disease and the second molar.
CBCT can clarify a three-dimensional relationship when the answer could change the procedure or consent. It is not routine screening for every third molar and does not itself prevent nerve injury. Explain why the additional exposure is justified and what decision depends on it.
Impacted third molar beside distal second-molar caries
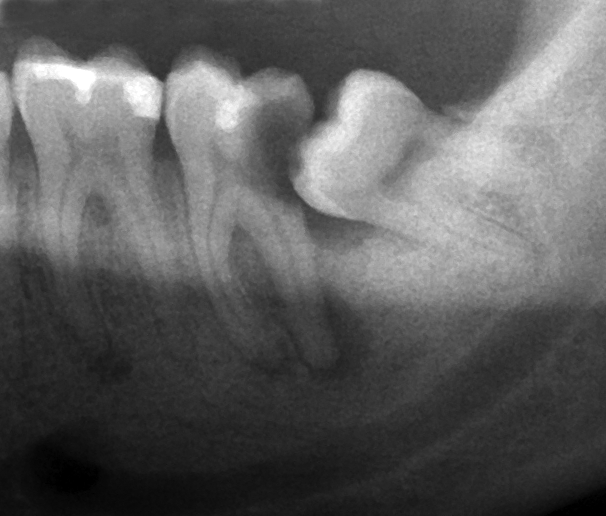
The source identifies caries on the second molar beside an impacted lower third molar. Describe the tooth positions and adjacent surface before deciding the clinical significance.
Wisdom tooth causing dental caries.png · Coronation Dental Specialty Group · CC BY-SA 3.0. Image reproduced without alteration; original marks and any embedded credits retained.
Compare observation and complete removal
Observation includes clinical review of symptoms, eruption, hygiene and neighbouring disease, with imaging when justified. It is a documented plan, not abandonment. Explain what changes should prompt reassessment, including repeated inflammation, new decay or adjacent tooth disease.
Complete removal eliminates the tooth and associated crown/root disease but creates operative risks. Access, bone removal and sectioning should follow the individual delivery path. Discuss expected recovery and relevant complications, including bleeding, dry socket, infection, adjacent damage, sinus complications where relevant and sensory disturbance.
Select coronectomy carefully
Coronectomy intentionally removes the crown and retains suitable roots to reduce manipulation close to the inferior alveolar nerve. It is considered for selected high-risk mandibular third molars with an indication for treatment. Roots affected by relevant pathology or made mobile during treatment may not be suitable for retention.
Discuss migration, root exposure, infection and possible later surgery, plus possible conversion to full removal during the original procedure. Coronectomy reduces a particular risk; it does not remove every sensory risk or substitute for case selection. It is different from accidentally leaving an infected fractured root.
Understand the consequences of nerve injury
The inferior alveolar nerve is relevant to lower lip and chin sensation; the lingual nerve supplies general sensation to the ipsilateral anterior tongue and is associated with taste fibres through the chorda tympani. Symptoms can include numbness, tingling, dysaesthesia and neuropathic pain. Motor tongue weakness suggests a different pathway.
Consent should explain functional consequences and patient-specific uncertainty, rather than a single percentage applied to every case. New postoperative sensory symptoms need a documented distribution, baseline examination, follow-up and timely advice when the deficit or operative mechanism is concerning.
Plan recovery and reassessment
Select anaesthetic and setting through medical, anatomical and psychological assessment. Give suitable analgesic and hygiene advice, a bleeding plan and clear emergency contacts. Antibiotics are not automatically required merely because the operation is surgical; infection risk and current prescribing guidance determine their use.
Review persistent or worsening symptoms against the operative record. Delayed severe socket pain differs from progressive cellulitis, and neither should be managed simply by issuing another antibiotic. Retained-root follow-up after coronectomy should follow the treating service’s plan, with symptoms and migration interpreted in context.
A distinction to remember
A high-risk panoramic appearance establishes a risk discussion, not an indication for removal. Coronectomy is a selected treatment option with its own future-care implications.
A healthy patient has a first mild episode of pericoronitis without spreading infection. Is extraction automatically indicated?
Reveal the reasoning
No. Manage the acute local problem and assess its cause and severity. NICE does not usually treat a first episode as sufficient unless particularly severe. Discuss prevention and reassessment; repeated episodes or other demonstrated pathology may support later intervention.
Test your recall
What does Winter’s classification describe?
Show answer
It describes third-molar angulation relative to the adjacent tooth, such as mesioangular, horizontal, vertical or distoangular position. This helps communicate access and likely sectioning considerations, but does not account for root form, bone density, patient factors or operator experience.