
Surgical extraction
A surgical extraction creates controlled access or a deliverable tooth shape when a closed approach is unsuitable. Its biological aims are to preserve vascular tissue and healing capacity; its mechanical aim is to reduce avoidable force. Technique must be learned under supervision, with anatomy and a complication plan understood.
Quick revision summary
Select the approach before starting
Indications include inaccessible retained roots, unfavourable root morphology, impacted teeth and teeth that cannot be delivered safely with a closed technique. Distinguish difficulty from indication: technical feasibility does not establish that extraction benefits the patient.
Section the tooth with a defined objective
Sectioning changes a large or divergent tooth into smaller components that can follow separate delivery paths. A multirooted molar may become simpler after root separation, but the cut should reflect the actual anatomy rather than a memorised diagram.
Review outcomes, not just the wound surface
Document technique, relevant anatomy, retained material, intraoperative events, haemostasis and aftercare. Explain expected pain, swelling and restricted opening in the context of the procedure, then describe symptoms that require review.
Common mistake
A surgical approach should improve visibility and mechanics. A flap and a drill do not make blind force safe.
Surgical extraction: access, sectioning and tissue preservation
A surgical extraction creates controlled access or a deliverable tooth shape when a closed approach is unsuitable. Its biological aims are to preserve vascular tissue and healing capacity; its mechanical aim is to reduce avoidable force. Technique must be learned under supervision, with anatomy and a complication plan understood.
Select the approach before starting
Indications include inaccessible retained roots, unfavourable root morphology, impacted teeth and teeth that cannot be delivered safely with a closed technique. Distinguish difficulty from indication: technical feasibility does not establish that extraction benefits the patient. Review alternatives, the entire image and adjacent structures.
Assess crown and root form, bone density, mouth opening, soft-tissue access and likely delivery direction. Previous endodontics, ankylosis and large restorations may alter purchase. Combine these with medical history, anxiety and operator competence when choosing the setting. A failed simple extraction needs reassessment rather than an automatic continuation with unfamiliar surgery.
Tooth & supporting tissues
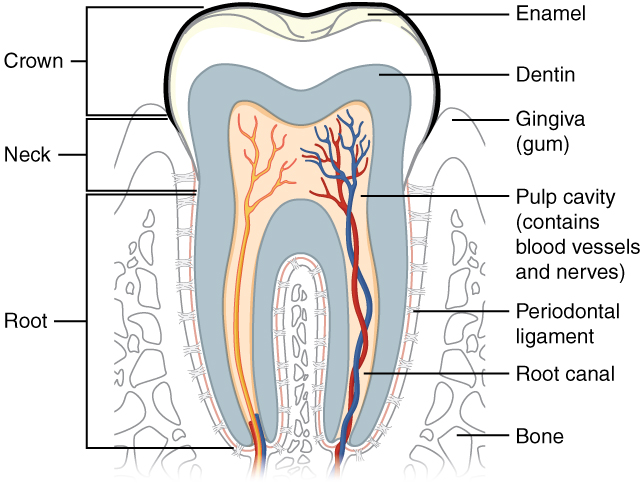
Trace the pulp and root canal to the apical region, then identify the periodontal ligament and supporting bone. Relate these structures to avulsion, apical pathology and extraction. The original uses the spelling “dentin”; cementum is not separately labelled.
Tooth & supporting tissues · OpenStax College · CC BY 3.0. Original image; displayed at a responsive size. Original publication.
Design access around blood supply and anatomy
A mucoperiosteal flap includes mucosa and periosteum, exposing bone while allowing the soft tissues to be repositioned. Envelope and releasing-incision designs provide different exposure. The flap needs adequate access, a viable base and a closure plan; an undersized flap can tear during retraction and compromise visibility.
Incisions and retractors must account for the mental nerve, lingual tissues, adjacent teeth and expected bony defect. Protect the cheek and tongue, support the jaw and avoid crushing tissue. Retraction is an active source of risk if force or instrument placement injures tissues outside the visible operative target.
Adult mandible: labelled lateral anatomy
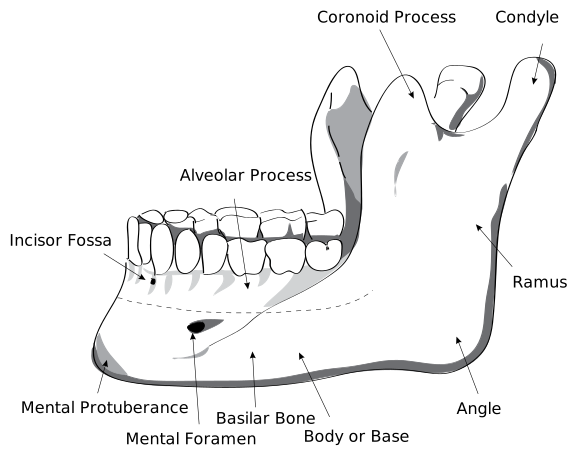
Locate the body, ramus, angle, condylar process, coronoid process and mental foramen. Use the labels to distinguish the two superior processes and the landmarks relevant to local anaesthesia and surgery.
HumanMandibleLeft.svg · Djexplo · CC0. None; reproduced without alteration.
Which nerve emerges through the mental foramen?
The mental nerve, a terminal branch of the inferior alveolar nerve, supplying the lower lip and chin.
Use bone removal to create clearance
The purpose of bone removal is to expose a useful purchase point or remove a specific obstruction to delivery. Its extent follows tooth geometry and local anatomy. Unnecessary bone loss increases morbidity and can compromise neighbouring teeth, a thin mandibular border or later rehabilitation.
Bone cutting requires a suitable surgical instrument, effective cooling and a clear view. Heat injury can impair healing. Equipment that forces air into tissues can cause surgical emphysema; use devices appropriate to the procedure and local safety requirements. Sudden swelling with crepitus is a different problem from ordinary postoperative oedema and needs assessment.
Section the tooth with a defined objective
Sectioning changes a large or divergent tooth into smaller components that can follow separate delivery paths. A multirooted molar may become simpler after root separation, but the cut should reflect the actual anatomy rather than a memorised diagram. Plan which component will be removed first and how the remaining components will be controlled.
Protect adjacent roots and soft tissues during sectioning. Avoid deep blind cuts toward a canal or uncontrolled apical pressure. If a fragment is not behaving as predicted, reassess the completeness of the cut, clearance and root form. A controlled change of plan is preferable to escalating leverage.
Manage altered anatomy and unexpected events
Potential problems include root fracture or displacement, haemorrhage, tuberosity fracture, oroantral communication, adjacent tooth damage and nerve injury. Stop, make the field safe and establish what has occurred. Maintain direct vision; blind attempts at retrieval can convert a local event into deeper displacement or neurovascular damage.
A small non-infected fragment near a vital structure may sometimes be retained after appropriate assessment. A displaced fragment needs localisation and an informed specialist plan. For suspected sinus communication, avoid repeatedly probing or forcing pressure through the wound; confirm the diagnosis using a suitable clinical and imaging assessment.
Irrigate, inspect and close appropriately
After delivery, check tooth and root completeness, wound condition and neighbouring structures. Irrigate to remove loose debris, with attention to the operative anatomy. Remove sharp bone or pathological tissue when indicated rather than treating all sockets identically. Histology may be required for abnormal tissue.
Closure aims to stabilise the wound and support healing. Suture choice depends on tissue handling, expected tension, contamination and follow-up. Approximate rather than strangulate tissue; closure under excessive tension can fail. Absorbable material does not remove the need to assess wound problems, and non-absorbable material requires removal arrangements.
Review outcomes, not just the wound surface
Document technique, relevant anatomy, retained material, intraoperative events, haemostasis and aftercare. Explain expected pain, swelling and restricted opening in the context of the procedure, then describe symptoms that require review. Advice must include a usable contact route and suitable analgesia.
Progressive swelling, systemic illness, swallowing or breathing difficulty, uncontrolled bleeding or new sensory symptoms require assessment. Wound dehiscence, exposed sharp bone and delayed pain have different causes and management. Future operations should be informed by what actually happened at the first procedure rather than an incomplete account of a difficult extraction.
A distinction to remember
A surgical approach should improve visibility and mechanics. A flap and a drill do not make blind force safe.
A molar remains immobile after a flap is raised. What should be reassessed before applying more force?
Reveal the reasoning
Check bone clearance, root divergence, ankylosis, completeness of any sectioning and the intended delivery path. A flap alone does not remove a mechanical obstruction. Improve the plan within competence or obtain suitable assistance before further force causes avoidable injury.
Guidance to read alongside this chapter
Test your recall
What are the main purposes of a mucoperiosteal flap?
Show answer
It provides visibility and access to bone or tooth while preserving tissue that can be repositioned for healing. Its design must account for vascularity, nearby structures and closure. More exposure is not automatically better, but inadequate access can cause tearing and uncontrolled force.