
Nerve injury
Injury to a sensory nerve can affect comfort, eating, speech and confidence, even when a surgical wound looks satisfactory. Prevention begins with anatomical planning. After an injury, useful care depends on honest explanation, reproducible assessment, attention to neuropathic pain and appropriately timed specialist advice.
THE ANATOMY LAB / INTERACTIVE 3DExplore the source dental nerve anatomy in 3D↗Quick revision summary
Localise the relevant nerve
The inferior alveolar nerve enters the mandibular canal and supplies mandibular teeth, continuing to the mental and incisive branches. Its mental distribution includes the lower lip and chin. The lingual nerve supplies general sensation to the ipsilateral anterior tongue and carries associated chorda tympani fibres relevant to taste.
Take a focused postoperative history
Record onset relative to anaesthetic resolution, distribution, degree of numbness, tingling, pain and change over time. Ask about tongue or lip biting, drooling, eating, speech, brushing, sleep and psychological impact.
Respond to displaced material and maintain continuity
If a fragment is lost or displaced, stop blind retrieval and localise it appropriately, considering aspiration when the mechanism suggests it. Material near a nerve can change assessment and urgency.
Common mistake
“It will settle” is not a management plan. Suspected transection and painful or severe deficits need a purposeful pathway rather than indefinite observation.
Trigeminal nerve injury: prevention, assessment and referral
Injury to a sensory nerve can affect comfort, eating, speech and confidence, even when a surgical wound looks satisfactory. Prevention begins with anatomical planning. After an injury, useful care depends on honest explanation, reproducible assessment, attention to neuropathic pain and appropriately timed specialist advice.
Localise the relevant nerve
The inferior alveolar nerve enters the mandibular canal and supplies mandibular teeth, continuing to the mental and incisive branches. Its mental distribution includes the lower lip and chin. The lingual nerve supplies general sensation to the ipsilateral anterior tongue and carries associated chorda tympani fibres relevant to taste.
The lingual nerve is close to the medial mandibular tissues in the third-molar region and crosses the submandibular duct anteriorly. Soft-tissue retraction, incision and instrumentation can therefore matter as much as root position. Tongue motor function is primarily hypoglossal; true weakness or deviation should not be described simply as a lingual sensory deficit.
Trigeminal nerve & dental branches
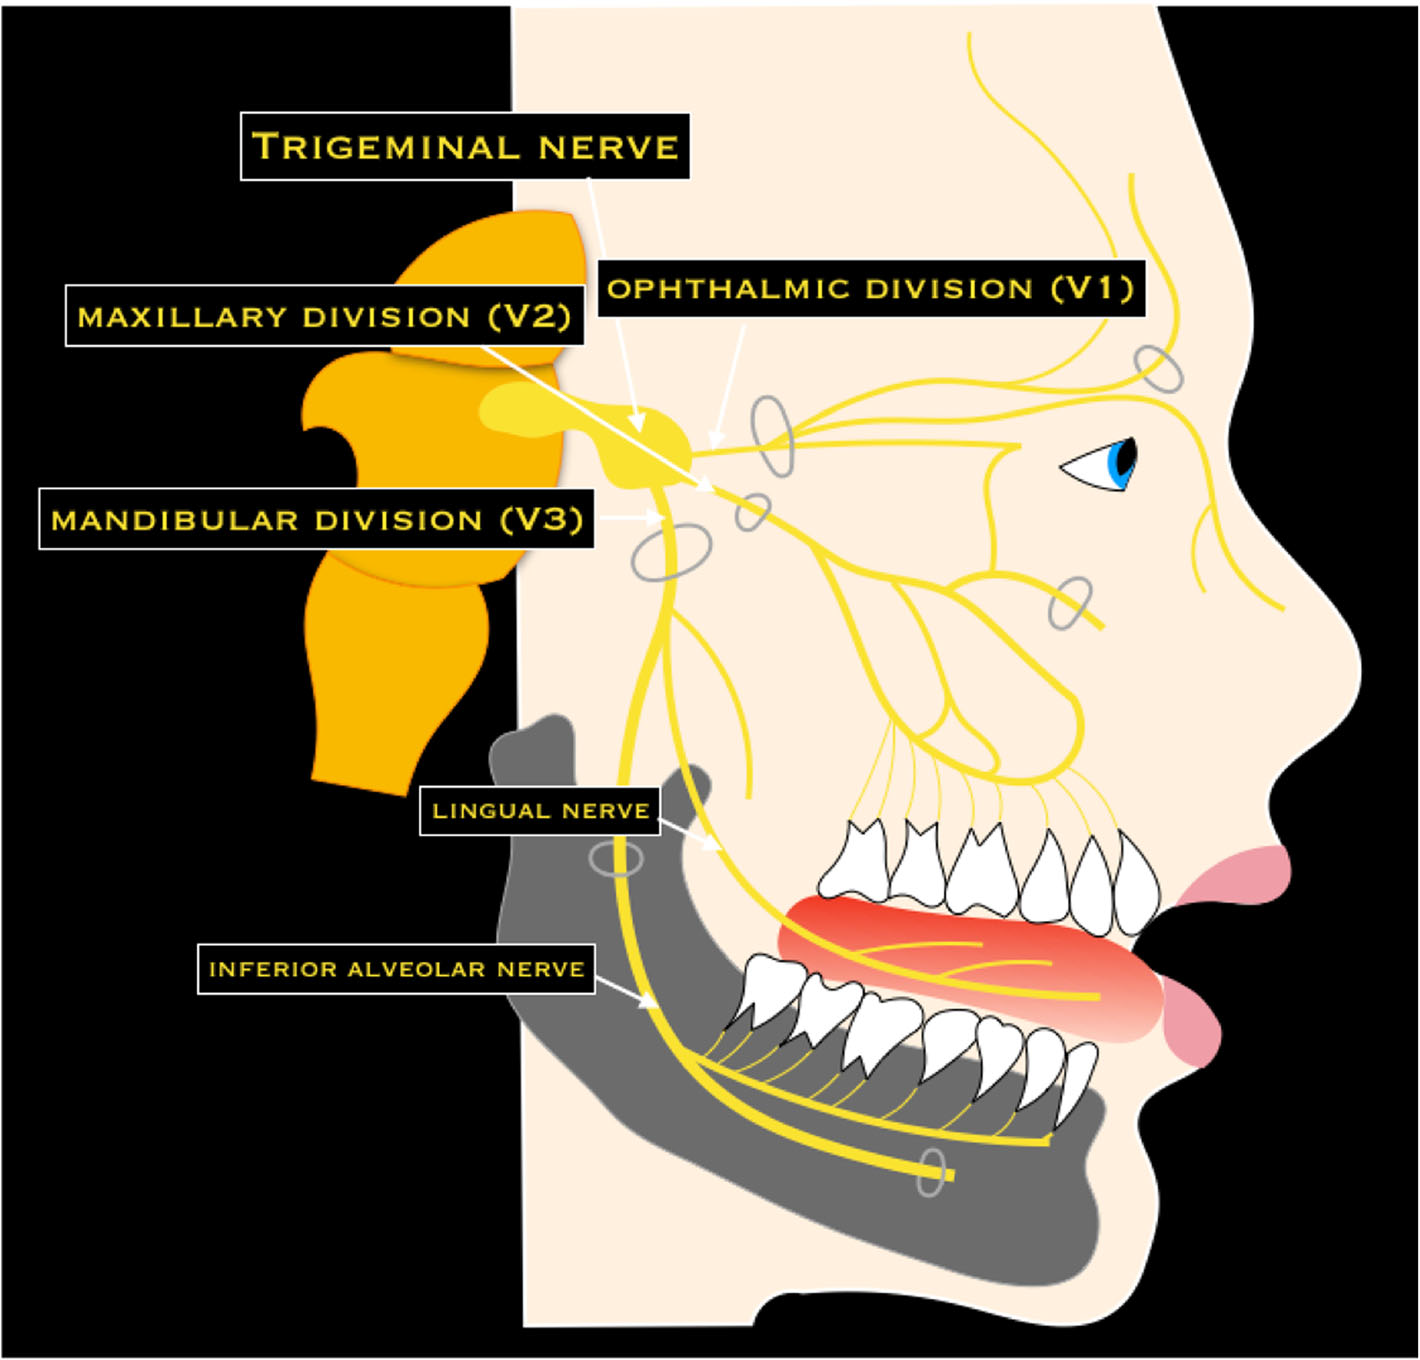
Trace V1, V2 and V3, then the lingual and inferior alveolar nerves. Connect each to the sensory examination after lower third-molar surgery. This is a branch overview, rather than an injection-placement diagram.
Trigeminal nerve & dental branches · Nicola Romano, Margherita Federici and Antonio Castaldi · CC BY 4.0. Original image; displayed at a responsive size. Original publication.
Understand mechanisms and injury severity
Compression, traction, direct laceration, thermal injury, chemical exposure and injection-related mechanisms can injure nerves. Neurapraxia describes a conduction block without axonal disruption; axonotmesis involves axonal injury with variable preservation of supporting structures; neurotmesis describes severe disruption including transection.
The precise biological category often cannot be established at the first postoperative examination. A mild improving altered sensation differs from dense anaesthesia, suspected transection or painful dysaesthesia. Do not infer prognosis solely from the size of the numb patch or reassure that all dental nerve injuries recover spontaneously.
Trigeminal divisions and facial sensory territories
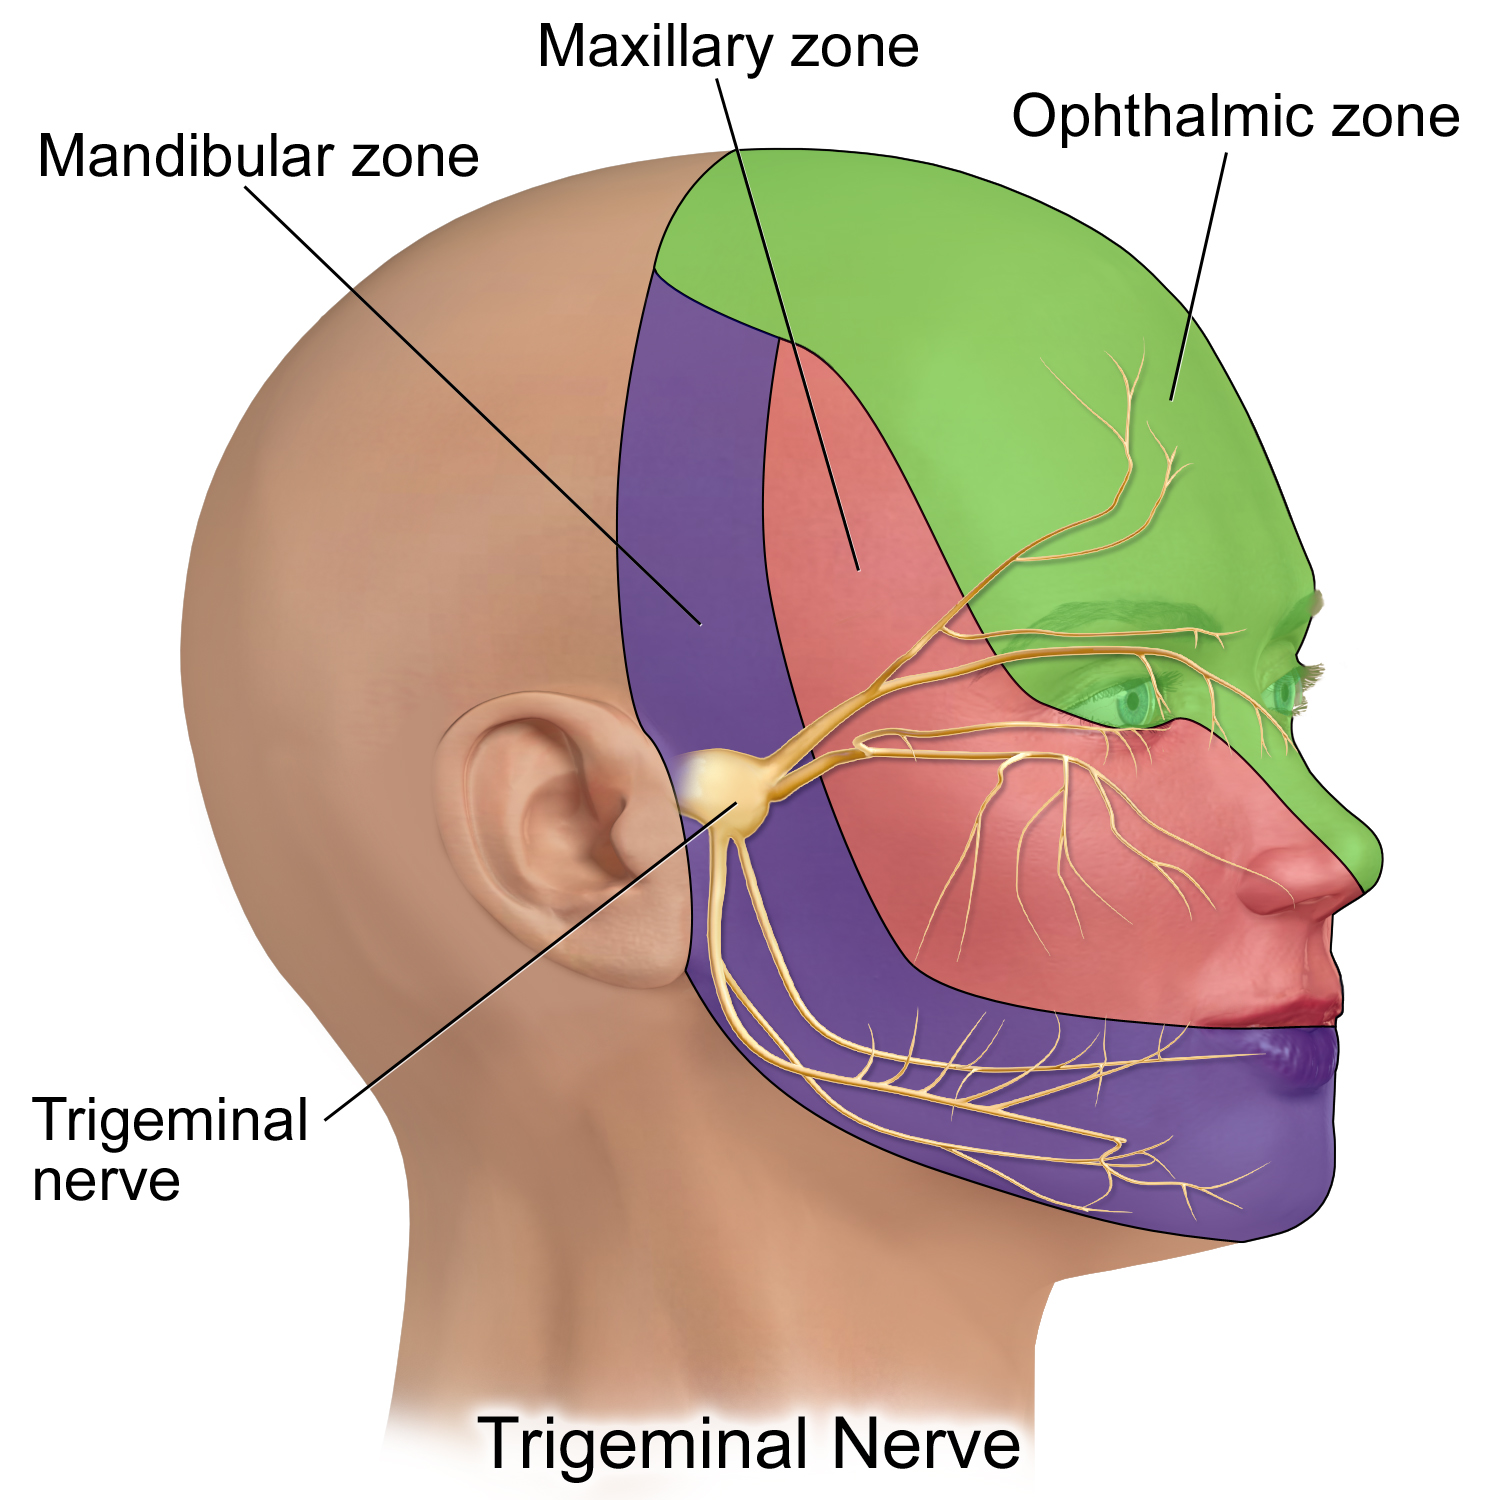
V1 is ophthalmic, V2 maxillary and V3 mandibular. This is a schematic sensory territory map, not a detailed map of every peripheral branch; V3 also carries motor fibres.
Trigeminal Nerve.png · BruceBlaus · CC BY-SA 4.0. None; reproduced without alteration.
Which division gives rise to the inferior alveolar and lingual nerves?
The mandibular division, V3. Distinguish lower lip/chin sensory change from altered tongue sensation.
Plan prevention and meaningful consent
Review anatomy, imaging and the intended procedure, including possible alternatives such as selected coronectomy for a high-risk lower third molar. Protect soft tissues and avoid blind manipulation. If a root or implant position creates concern, changing the planned procedure or obtaining specialist help may be safer than continuing.
Explain patient-specific sensory risks and their consequences, including painful altered sensation, taste disturbance when relevant and uncertainty about recovery. Record pre-existing symptoms where present. A form signed with generic wording does not establish that a patient understood how the risk might affect their work or daily function.
Take a focused postoperative history
Record onset relative to anaesthetic resolution, distribution, degree of numbness, tingling, pain and change over time. Ask about tongue or lip biting, drooling, eating, speech, brushing, sleep and psychological impact. Review the operative record and any event suggesting direct injury or a displaced fragment.
Distinguish spontaneous pain from stimulus-evoked pain and unpleasant altered sensation. Neuropathic pain can occur alongside reduced sensation. Consider other causes when the pattern does not fit the procedure, especially progressive unexplained numbness, multiple cranial nerve findings or motor weakness.
Make the sensory examination reproducible
Map the affected area on a diagram and compare with the contralateral side. Assess appropriate modalities such as light touch, pinprick, directional discrimination and two-point discrimination using a consistent method. Document what was actually tested and the patient’s responses rather than writing only “nerve intact”.
Record taste or tongue function when relevant and trained to assess it. Repeat the same examination to identify change, acknowledging subjectivity and variability. Serial findings are more useful than unexplained numerical thresholds. A normal wound appearance does not assess the sensory territory or exclude painful injury.
Know when observation needs specialist support
Explain findings and uncertainty, give practical protection advice for numb tissues and arrange a defined review. Obtain timely specialist advice for suspected transection, dense or concerning deficits, neuropathic pain and poor improvement according to the local nerve-injury pathway. Do not wait for a universal recovery deadline.
The Sheffield lingual nerve pathway distinguishes observed transection from postoperative sensory symptoms and supports urgent referral when a nerve is divided. Microsurgical assessment and pain care address different issues and may both be needed. A diagnosis of neuropathic pain does not automatically mean that further surgery will help.
Respond to displaced material and maintain continuity
If a fragment is lost or displaced, stop blind retrieval and localise it appropriately, considering aspiration when the mechanism suggests it. Material near a nerve can change assessment and urgency. Further probing can worsen the original injury, so management should be based on a defined anatomical problem.
Document disclosure, examinations, advice, referrals and agreed follow-up. Provide a contact route for changing symptoms and communicate with the receiving service. Persistent sensory disability can require multidisciplinary pain or psychological support; recognising its impact is part of care rather than evidence that symptoms are imaginary.
A distinction to remember
“It will settle” is not a management plan. Suspected transection and painful or severe deficits need a purposeful pathway rather than indefinite observation.
A patient has tongue numbness after lower third-molar surgery but normal movement. Which nerve is most relevant?
Reveal the reasoning
The lingual nerve is the likely sensory pathway in the appropriate distribution. Record taste symptoms, pain and functional impact and perform a reproducible sensory examination. Normal motor movement does not exclude sensory injury because tongue movement is mainly supplied by the hypoglossal nerve.
Guidance to read alongside this chapter
Test your recall
Which sensory areas help distinguish inferior alveolar and lingual nerve injury?
Show answer
Inferior alveolar or mental injury commonly affects the lower lip and chin, while lingual injury affects the ipsilateral anterior tongue, with possible taste disturbance. Map the actual distribution and assess function; overlapping symptoms or an atypical pattern need broader clinical interpretation.