
Advanced imaging pathways
The modality should fit the tissue, urgency and management question.
Quick revision summary
Choose a modality for the suspected process
Cross-sectional CT, MRI and ultrasound have different strengths. CT can be useful for selected bony, traumatic and acute hospital questions; MRI offers soft-tissue and related structural information without ionising radiation; ultrasound can assess suitable superficial glands and masses and support guided sampling.
Compare the information each modality supplies
CT can show bony injury and provide contrast-enhanced assessment of selected deep infection or tumour questions in the appropriate setting. MRI is useful for many soft-tissue, marrow and joint questions and does not use ionising radiation.
Plan safety checks and result ownership
Imaging selection also depends on implants or devices, renal and contrast considerations, pregnancy where relevant, claustrophobia, movement and the patient’s ability to lie or cooperate. These issues require modality-specific assessment by the responsible imaging team.
Common mistake
Choose imaging to answer the clinical question; a scan does not replace an appropriate urgent referral.
Advanced imaging as a clinical pathway
The modality should fit the tissue, urgency and management question.
Choose a modality for the suspected process
Cross-sectional CT, MRI and ultrasound have different strengths. CT can be useful for selected bony, traumatic and acute hospital questions; MRI offers soft-tissue and related structural information without ionising radiation; ultrasound can assess suitable superficial glands and masses and support guided sampling. These are broad roles, not automatic indications. Availability and the patient’s ability to tolerate the examination also matter.
A suspected serious infection or malignancy requires the appropriate clinical pathway rather than an isolated imaging request from a routine dental setting. Provide a focused question and relevant examination findings. Check modality-specific safety and contrast considerations through the imaging team. Tissue sampling, endoscopy or specialist examination may still be needed after imaging. Establish who reviews and communicates results so investigation does not become an uncompleted sequence.
Ameloblastoma: expansion on axial CT
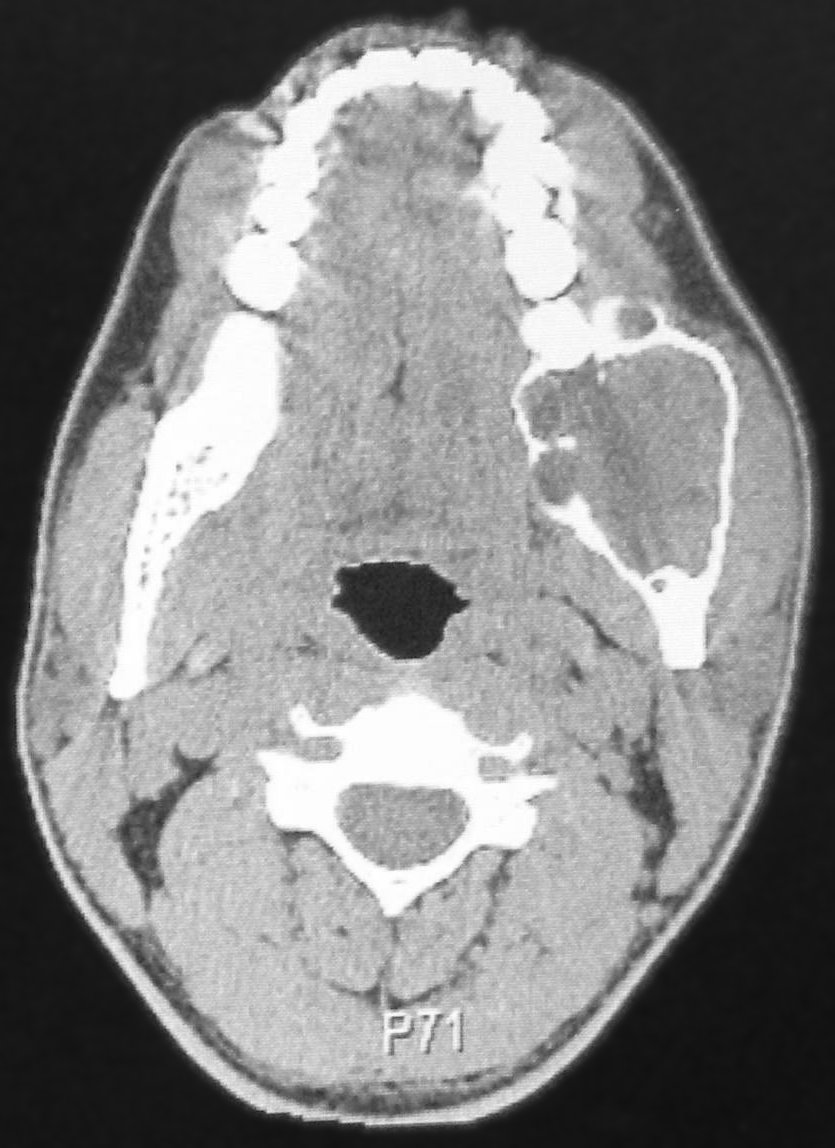
Compare the expanded posterior mandible on the right of the displayed image with the opposite side. The source reports a left mandibular ameloblastoma. Trace the remaining cortex and internal compartmental appearance. This CT example and the histology example elsewhere in the atlas come from separate teaching cases.
CT Scan of ameloblastoma.jpg · Berto1286; source-file crop and tonal adjustment by Hellerhoff · Public domain. Reproduced without alteration. Labels, arrows and circles, where present, belong to the source image.
What does this axial view show that a panoramic projection may conceal?
Buccolingual expansion and the relationship to the cortical boundaries are more directly visible. The imaging pattern informs the differential and extent assessment; tissue findings establish classification.
Key distinctions in practice
| Finding or option | What it means | Clinical consequence |
|---|---|---|
| CT | Selected acute, bony or cross-sectional questions | Assess exposure, contrast and urgency through the appropriate service. |
| MRI | Selected soft-tissue and structural questions | Check safety, tolerability and the clinical aim. |
| Ultrasound | Suitable superficial soft tissues | Operator skill and lesion accessibility affect usefulness. |
| Specialist pathway | Coordinates diagnosis and treatment | Imaging alone does not complete assessment. |
Compare the information each modality supplies
CT can show bony injury and provide contrast-enhanced assessment of selected deep infection or tumour questions in the appropriate setting. MRI is useful for many soft-tissue, marrow and joint questions and does not use ionising radiation. Ultrasound can assess accessible superficial tissues, glands and lymph nodes and guide selected sampling. None is a universal “best scan”.
A dental CBCT emphasises mineralised anatomy but does not replace a contrast-enhanced hospital examination when deep-space infection is suspected. Similarly, a dental projection cannot stage a head and neck malignancy. The referral should describe the suspected process and the decision that imaging needs to inform so that the receiving service can choose the appropriate examination.
Plan safety checks and result ownership
Imaging selection also depends on implants or devices, renal and contrast considerations, pregnancy where relevant, claustrophobia, movement and the patient’s ability to lie or cooperate. These issues require modality-specific assessment by the responsible imaging team. Do not assume that a device is MRI-safe or that a contrast history is irrelevant.
For a rapidly deteriorating infection, arrange urgent clinical care; do not leave the patient waiting in a routine imaging pathway. For a persistent suspicious lesion, a scan may complement examination and biopsy but does not necessarily replace either. Agree who requests the test, reviews the result, tells the patient and responds if the result is delayed or indeterminate.
A distinction to remember
Choose imaging to answer the clinical question; a scan does not replace an appropriate urgent referral.
Why does a reassuring image not automatically close a persistent clinically suspicious oral lesion?
Reveal the reasoning
Imaging has limits and cannot replace appropriate direct examination or tissue diagnosis. Persistent discordance requires specialist reassessment.
Guidance to read alongside this chapter
Test your recall
Which modality usually gives better soft tissue contrast: CT or MRI?
Show answer
MRI generally provides better soft-tissue contrast. The appropriate modality still depends on the clinical question, patient factors and the information needed; CT may be preferred for other questions such as selected acute bony or contrast-enhanced assessments.