
Periodontitis classification
A periodontal diagnosis should identify the disease, historical severity, distribution, progression estimate and current status. State the classification implementation used: simplified UK/BSP criteria and the full international scheme are related but not identical.
Quick revision summary
Classify after diagnosing
Exclude non-periodontitis reasons for attachment loss, then record stage, grade and extent. Name the classification implementation because simplified UK/BSP rules and the full international framework differ.
Calculate and explain grade
The simplified UK bone-loss-to-age ratio is below 0.5 for A, 0.5–1.0 for B and above 1.0 for C. Record smoking and diabetes in the risk profile.
Retain historical severity
Successful therapy changes current stability, not the historical stage. Use site-level bleeding, depths and trends to guide further care; a classification threshold alone does not prove active progression.
Common mistake
Do not blend the full international scheme with simplified UK rules or downstage a successfully treated patient.
Periodontitis classification
A periodontal diagnosis should identify the disease, historical severity, distribution, progression estimate and current status. State the classification implementation used: simplified UK/BSP criteria and the full international scheme are related but not identical.
Confirm the case before assigning a stage
Interdental attachment loss at two non-adjacent teeth supports periodontitis once other causes are excluded. The international definition also includes specified buccal or oral attachment loss with pocketing at two or more teeth. Traumatic recession, an endodontic drainage tract, a root fracture and a local post-surgical defect should not automatically determine the diagnosis.
Map the pattern clinically and with indicated imaging. The former chronic and aggressive labels are no longer the routine principal categories. Necrotising periodontitis and disease as a manifestation of certain systemic conditions remain distinct. A classification name does not identify a particular organism or prove one mechanism in an individual patient.
Periodontitis: pocket formation and loss of support
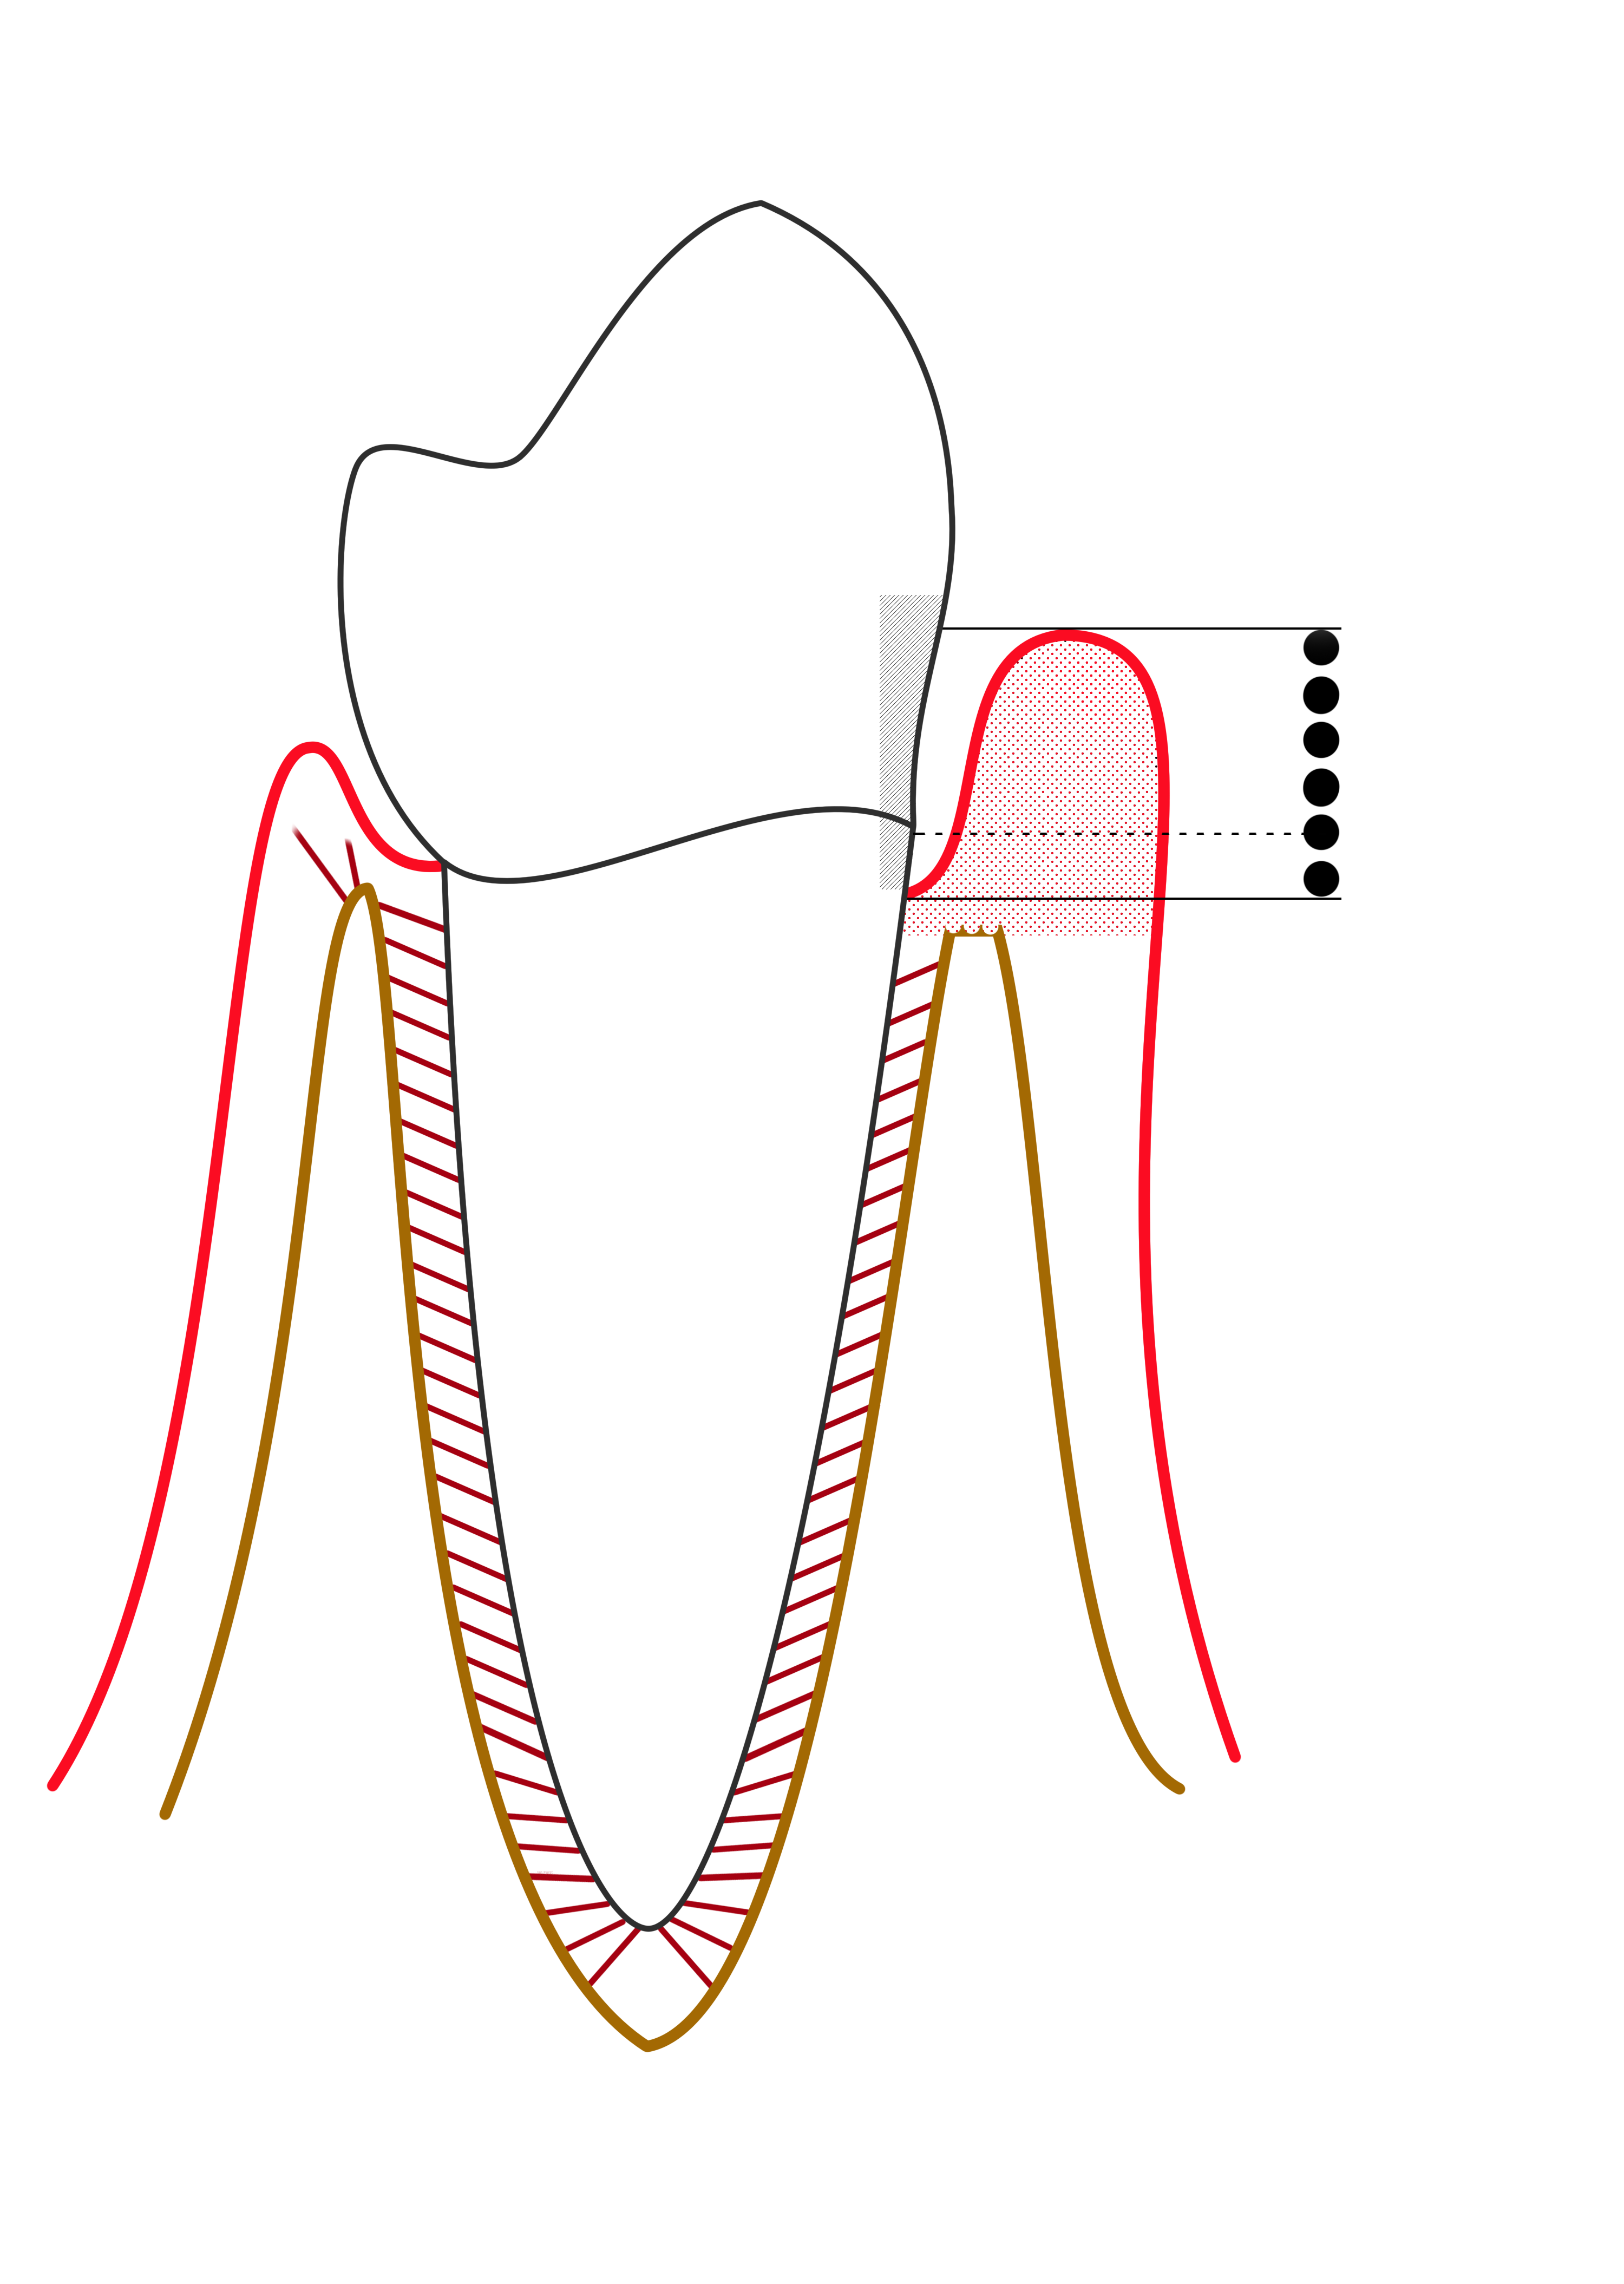
Compare the apical extent of the pocket and the reduced supporting bone on the affected side. This simplified diagram is labelled “mild periodontitis” by its author; it is not a modern stage/grade classification chart.
Mild periodontitis.png · Ian Furst · CC BY-SA 4.0. None; reproduced without alteration.
Why is probing depth different from clinical attachment level?
Probing depth runs from the gingival margin to the pocket base. Clinical attachment level uses the cemento-enamel junction as its reference; recession or enlargement changes their relationship.
Understand what stage represents
The full international framework uses interdental attachment loss, radiographic bone loss, periodontal tooth loss and management complexity. Stages I and II describe less advanced loss; stages III and IV describe severe disease, with stage IV particularly concerned with functional and rehabilitation complexity. Loss from caries must not be counted as periodontal tooth loss.
The simplified UK/BSP approach described by SDCEP primarily stages the worst periodontitis-related bone loss: stage I below 15%, stage II within the coronal third, stage III reaching the middle third and stage IV reaching the apical third. Known tooth loss from advanced periodontitis may also support stage IV. Use the framework requested by the clinical service or examination and record its supporting evidence.
Periodontal bone loss on a periapical radiograph
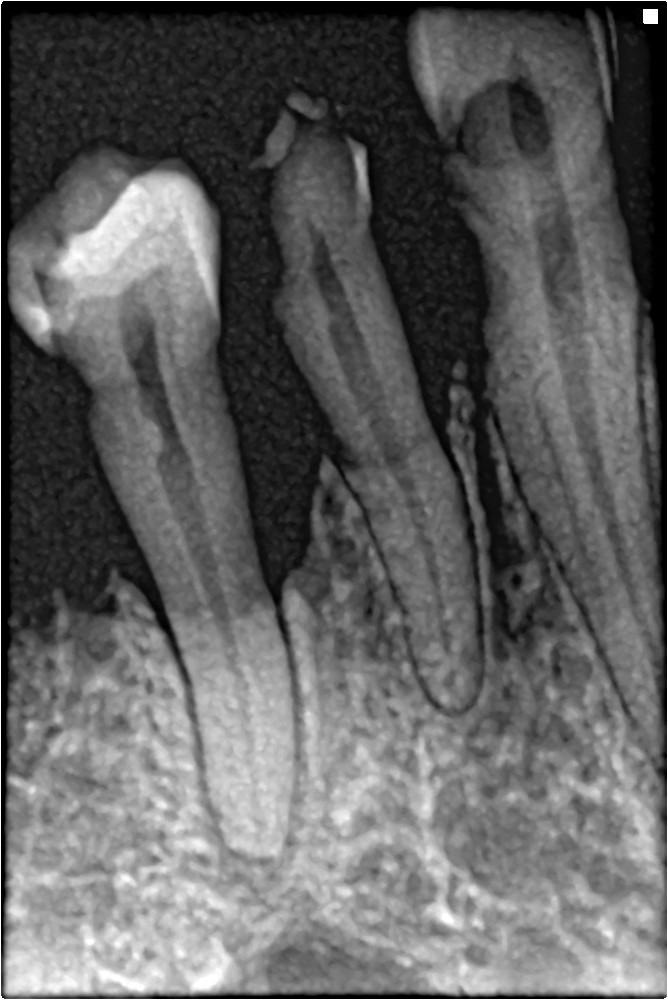
Trace the reduced bone height and irregular contour between the teeth. Correlate with full periodontal charting; this single image cannot establish the patient’s complete stage and grade.
Bone loss in periapical xray.jpg · Shaimaa Abdellatif · CC BY-SA 4.0. Image reproduced without alteration; original marks and any embedded credits retained.
Calculate grade without blending schemes
The UK simplification divides worst percentage bone loss by age in years: below 0.5 supports grade A, 0.5–1.0 grade B, and above 1.0 grade C. A 30-year-old with 45% loss has a ratio of 1.5. This is an indirect estimate of past progression, not a measured annual rate.
The original international framework also considers direct longitudinal evidence and permits smoking and diabetes modifiers. The UK simplification records these factors alongside the diagnosis rather than automatically changing grade on their basis. Mixing the numerical rule from one implementation with modifiers from another can produce an unexplained diagnosis. State the scheme and keep serial records of actual change.
Describe extent using the right denominator
Periodontitis extent concerns teeth affected by support loss; gingival bleeding extent concerns bleeding sites. They describe different things. A patient can have generalised historical bone loss and very little bleeding after treatment. A molar–incisor distribution is also useful to name where it describes the pattern.
The international convention commonly uses localised below 30% and generalised at least 30% of teeth; the SDCEP online table prints generalised above 30%. At the boundary, record the actual number and percentage and follow the convention used by the service. Precise underlying findings are more valuable than concealing a borderline case within a label.
Assess current stability separately
The UK stable description requires bleeding below 10%, pockets no deeper than 4 mm and no bleeding at 4 mm sites. More widespread bleeding with shallow pockets and no bleeding 4 mm sites can fit remission. A pocket of at least 5 mm or a bleeding 4 mm site falls outside stability.
These categories support planning but do not prove site activity by themselves. A recently treated, non-bleeding deeper site may need observation and reassessment rather than immediate surgery. Consider healing time, reproducibility, deposits, anatomy and previous change. Treatment should respond to the clinical problem, not only a category name.
Keep historical severity visible after success
Successful treatment can reduce inflammation and pocket depth without restoring original support. Do not downstage the patient simply because the tissues now look healthy. Retain the historical stage and describe current stability and relevant risks. This preserves the reason for supportive care and the context of future changes.
An example statement is generalised periodontitis, stage III, grade C, currently unstable; current smoker. Add key sites, prognosis, the shared plan and review arrangements. For a young adult with disproportionate loss, the grade supports careful assessment and monitoring; it does not mean every tooth is hopeless or that antibiotics are automatically required.
A distinction to remember
Do not blend the full international scheme with simplified UK rules or downstage a successfully treated patient.
A 30-year-old has 45% bone loss at the worst site. What is the simplified UK grade?
Reveal the reasoning
The ratio is 45 divided by 30, or 1.5, supporting grade C. Confirm that the loss is periodontal in origin and document risk factors separately. This calculation estimates progression history; it does not establish activity at every site today.
Test your recall
What does stage describe?
Show answer
Stage summarises historical severity and, in the full international framework, management complexity and periodontal tooth loss. It is separate from today’s inflammation. Record the evidence and implementation because the simplified UK/BSP approach differs from the complete international matrix.