
Pulp therapy in children
Pulp treatment has different objectives in a primary molar and an immature permanent incisor. Decide which tissue can be retained, what the final restoration can achieve and how success will be monitored.
Quick revision summary
Separate vital inflammation from infection
A vital primary molar with irreversible symptoms may be suitable for pulpotomy under current SDCEP guidance. Abscess, sinus, inter-radicular pathology or necrotic canals change the options and require a different assessment.
Preserve development where possible
In immature permanent teeth, maintaining healthy pulp can support continued root development. Apex status, injury or caries, tissue findings and restoratability guide vital pulp therapy or appropriate specialist endodontic alternatives.
The seal and review matter
Pulp treatment requires suitable case selection, effective isolation, tissue management and a durable restoration. Arrange clinical and justified radiographic review, and explain persistent pain, swelling or sinus formation as reasons to return.
Common mistake
A negative cold response in a recently traumatised immature permanent tooth does not, by itself, diagnose necrosis or justify pulpectomy.
Pulp therapy in children
Pulp treatment has different objectives in a primary molar and an immature permanent incisor. Decide which tissue can be retained, what the final restoration can achieve and how success will be monitored.
Diagnose before choosing the procedure
History should distinguish short provoked pain from spontaneous, lingering or sleep-disturbing symptoms, while recognising that children may struggle to localise or describe pain. Examine caries, restorability, swelling, sinus, tenderness and mobility. Assess root maturity or physiological resorption and the supporting tissues on justified radiographs. Primary molar infection often appears in the furcation.
Pulp sensibility tests measure neural response, not blood flow. Young or recently traumatised permanent teeth may not respond despite viable pulp. Combine baseline and serial findings rather than diagnosing necrosis from a single negative test. Symptoms describe a clinical category; the condition of remaining pulp can only be further assessed during properly isolated treatment.
Tooth development: cap, bell and root formation
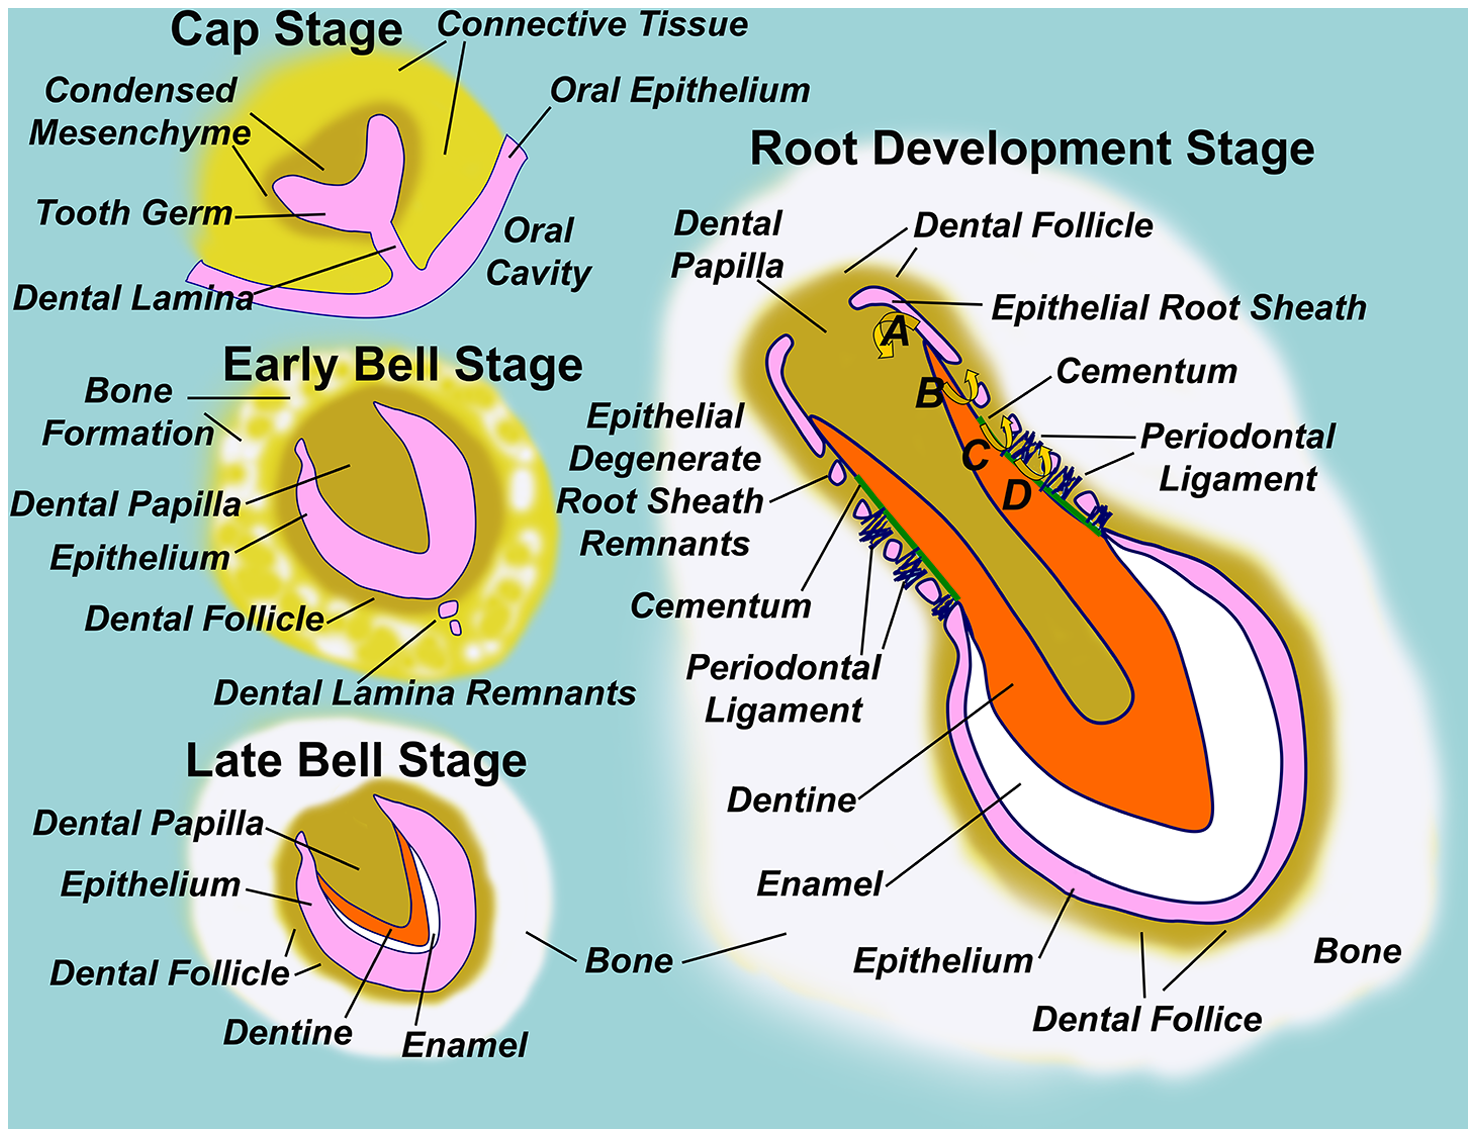
Follow the dental lamina, enamel organ, dental papilla and dental follicle through development. Locate the epithelial root sheath in the root-development panel.
Diagram illustrating normal tooth formation.png · Sarrafpour B, Swain M, Li Q, Zoellner H · CC BY 4.0. None; reproduced without alteration.
Which structure gives rise to dentine and pulp?
The dental papilla. The enamel organ gives rise to enamel; the dental follicle contributes to supporting periodontal tissues.
Use the correct biological terms
Indirect pulp treatment or selective caries removal avoids exposure while controlling a deep lesion beneath a durable restoration. Direct pulp capping places a suitable material on an exposure in a carefully selected vital tooth. Partial pulpotomy removes a limited depth of inflamed coronal pulp; full pulpotomy removes the entire coronal pulp. Pulpectomy removes pulp from the canals.
Apexogenesis describes continued physiological root development supported by vital pulp; it is an outcome rather than one material. Apexification creates or induces an apical barrier in a necrotic immature tooth. Regenerative endodontic procedures seek healing and, where possible, further development in selected immature necrotic teeth. These approaches are not interchangeable labels for treating an open apex.
Tooth & supporting tissues
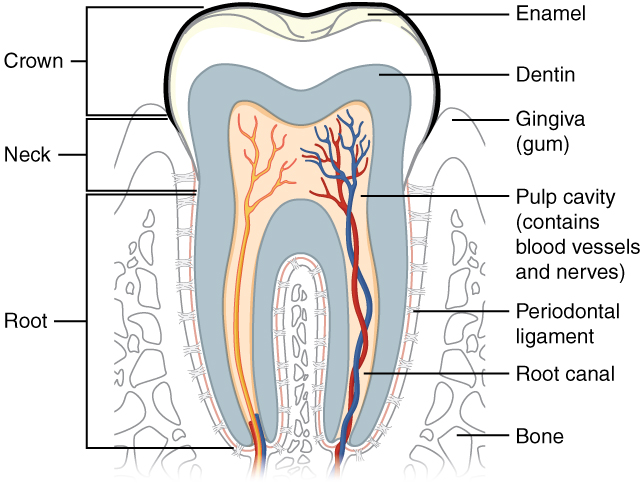
Trace the pulp and root canal to the apical region, then identify the periodontal ligament and supporting bone. Relate these structures to avulsion, apical pathology and extraction. The original uses the spelling “dentin”; cementum is not separately labelled.
Tooth & supporting tissues · OpenStax College · CC BY 3.0. Original image; displayed at a responsive size. Original publication.
Vital treatment in a primary molar
The aim is comfortable retention until appropriate exfoliation. Consider pulpotomy in a restorable vital tooth with suitable remaining radicular tissue and no abscess. SDCEP includes selected teeth with irreversible symptoms. Anaesthesia, isolation, removal of coronal tissue, evaluation of haemostasis and a suitable calcium-silicate material form part of the approach; formocresol is not recommended.
A preformed metal crown placed with a durable coronal seal is important. Persistent uncontrolled bleeding, necrotic tissue, infection, marked resorption or poor restorability can change the plan. Avoid describing every painful primary tooth as suitable for pulpotomy. Primary anatomy has thin chamber floors and divergent roots, requiring careful access without damaging the furcation or successor.
When a primary tooth is non-vital
A primary tooth with a sinus, abscess or inter-radicular pathology is not managed by a simple vital pulp dressing. Extraction often offers reliable source control. In selected restorable teeth with adequate root length and a worthwhile remaining lifespan, specialist pulpectomy may be considered, using a primary-tooth protocol and resorbable filling material.
Evaluate the child’s cooperation, medical status, number of affected teeth and the consequences of failure. Multiple complex procedures can be a large burden for a young child. Antibiotics cannot substitute for source control. Choosing extraction after a balanced appraisal is not a failure of minimally invasive care; leaving a non-vital tooth infected is not tissue preservation.
Preserve development in young permanent teeth
Following a traumatic pulp exposure, partial pulpotomy can preserve healthy deeper pulp while removing superficially inflamed tissue. The extent and contamination of the injury, tissue appearance, haemostasis, associated luxation, root maturity and restorability influence the choice. A small exposure is not the only criterion and elapsed time alone does not define all prognosis.
For selected cariously exposed permanent teeth, modern vital pulp therapy can be appropriate even with irreversible symptoms if suitable tissue and normal apical conditions support it. Strict asepsis and a calcium-silicate material are important. Do not extrapolate a primary-tooth procedure unchanged to a permanent incisor. If tissue is necrotic or bleeding cannot be controlled appropriately, reconsider the treatment objective.
Plan non-vital immature treatment and review
Thin root walls and an open apex make conventional preparation and obturation difficult. Specialist options include an apical calcium-silicate barrier or a regenerative procedure, depending on infection, anatomy, cooperation and follow-up. An artificial barrier does not guarantee that the root will lengthen or thicken. Explain fracture risk and uncertain developmental outcomes.
Follow clinical symptoms, swelling, sinus, tenderness, mobility and restoration integrity together with appropriate radiographic evidence of healing and development. Review schedules depend on the injury or treatment protocol; radiographs must remain justified. Continued pain, new pathology or resorption is not a successful outcome because the tooth was initially comfortable. Maintain access to definitive care if the original approach fails.
A distinction to remember
A negative cold response in a recently traumatised immature permanent tooth does not, by itself, diagnose necrosis or justify pulpectomy.
A newly erupted permanent incisor has a traumatic pulp exposure but healthy bleeding tissue. What is the treatment priority?
Reveal the reasoning
Preserve suitable vital tissue and obtain a durable seal where the injury and clinical findings support vital pulp treatment. Partial pulpotomy may allow continued root development. Assess associated injuries and establish a structured review plan rather than removing all pulp simply because it is exposed.
Test your recall
What is removed during a pulpotomy?
Show answer
Part or all of the coronal pulp is removed while suitable deeper tissue is retained. Partial and full pulpotomy differ in the amount removed. The aim is to retain healthy vital tissue beneath a durable seal, not merely to stop pain temporarily.