
Molar incisor hypomineralisation
MIH is a developmental enamel problem that can make an otherwise diligent child sensitive and difficult to restore. Separate the diagnosis, the prognosis of each tooth and the long-term treatment burden.
Quick revision summary
Recognise the enamel defect
MIH produces demarcated hypomineralised enamel affecting one or more first permanent molars, sometimes with incisors. Sensitivity, post-eruptive breakdown and atypical restorations may be more important than the initial visible opacity.
Treat sensitivity and instability
Support brushing, fluoride and feasible prevention while assessing restorative needs and anaesthetic difficulty. Judge each tooth’s remaining structure and prognosis; the child’s comfort and willingness to attend affect what can be maintained.
Plan extraction with development and occlusion
A compromised first permanent molar needs joint paediatric and orthodontic consideration. Timing depends on developing teeth and the wider bite; routine removal of sound matching or opposing molars is not justified.
Common mistake
A fixed extraction age or opacity colour alone cannot determine treatment. MIH needs tooth-level prognosis and coordinated developmental planning.
Molar incisor hypomineralisation
MIH is a developmental enamel problem that can make an otherwise diligent child sensitive and difficult to restore. Separate the diagnosis, the prognosis of each tooth and the long-term treatment burden.
Identify the pattern and mechanism
Molar incisor hypomineralisation is a qualitative enamel defect affecting at least one first permanent molar, often with permanent incisor involvement. Demarcated white, cream, yellow or brown opacities can occur. The enamel may have normal thickness initially but inadequate mineral quality, making it porous and susceptible to post-eruptive breakdown under load.
The cause is multifactorial and incompletely understood. A history of illness during development can be relevant, but an individual episode does not prove causation. Explain that the defect formed before eruption and is not simply a result of poor brushing. Plaque-mediated caries can develop alongside MIH and requires its own assessment.
Tooth development: cap, bell and root formation
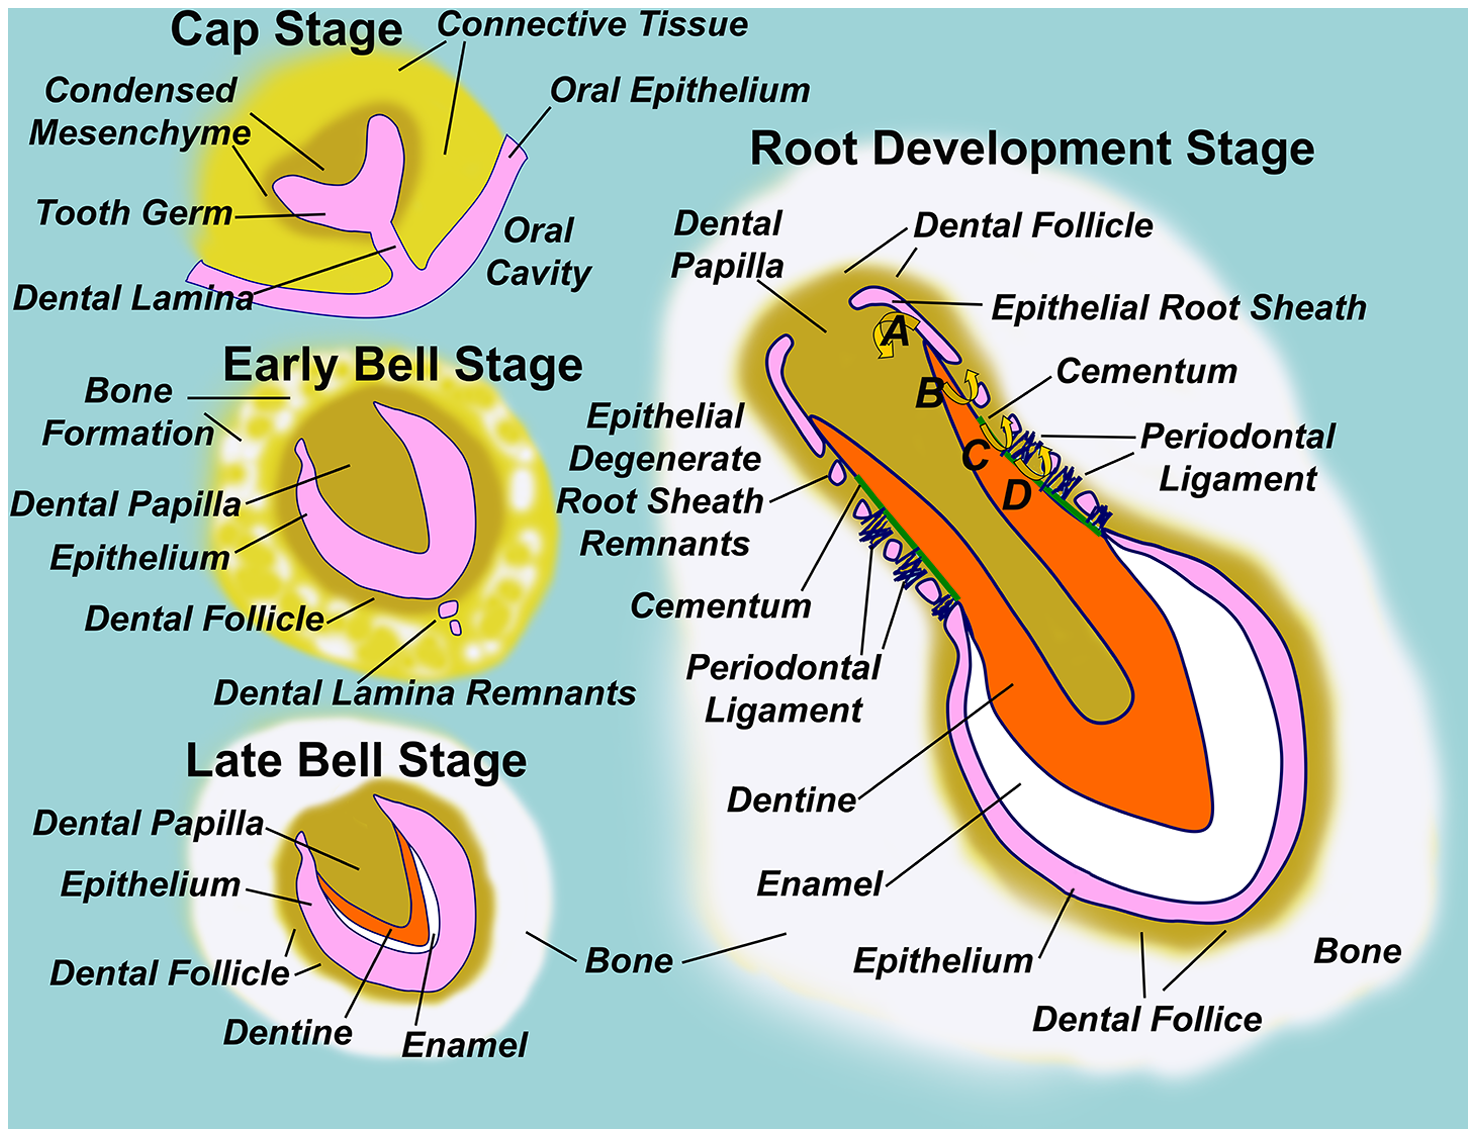
Follow the dental lamina, enamel organ, dental papilla and dental follicle through development. Locate the epithelial root sheath in the root-development panel.
Diagram illustrating normal tooth formation.png · Sarrafpour B, Swain M, Li Q, Zoellner H · CC BY 4.0. None; reproduced without alteration.
Which structure gives rise to dentine and pulp?
The dental papilla. The enamel organ gives rise to enamel; the dental follicle contributes to supporting periodontal tissues.
Distinguish MIH from other enamel defects
Hypoplasia is a quantitative reduction in enamel thickness and can present with pits, grooves or missing enamel already present at eruption. Fluorosis more often produces diffuse, bilateral changes without the same sharply demarcated pattern. Amelogenesis imperfecta usually has a more generalised distribution and may have a family history. A local predecessor injury can affect one successor.
Look at all first permanent molars and incisors and ask whether breakdown followed eruption. Atypical large restorations or prior first-molar extraction may conceal the original defect. Opacity colour contributes to assessment, but symptoms, extent, breakdown, caries, pulp status and restorability determine severity and treatment. Do not classify every white incisor opacity as MIH.
Control sensitivity and protect erupting teeth
Sensitivity to cold, brushing and chewing can reduce plaque control and increase anxiety. Introduce preventive care gently, provide effective pain management and use appropriate fluoride measures. Toothpaste choice must suit age and risk. Review professional varnish and desensitising measures as part of a wider plan, explaining that they cannot rebuild lost tooth form.
Partially erupted molars can be difficult to isolate and seal. A glass-ionomer seal or restoration may provide interim protection when a definitive adhesive procedure is not yet feasible. Once isolation is adequate, resin sealants may protect appropriate intact fissures. Follow eruption and material retention: an early protective intervention can fail as more defective enamel becomes exposed.
Choose a restoration that can survive
Bonding to defective enamel is less predictable, so an adhesive restoration needs sound, supported margins and effective isolation. Removing only visibly broken enamel can leave a weak margin; removing extensive defective tissue can sacrifice a large amount of tooth. Balance these issues with pulp proximity, symptoms and the expected lifespan of the restoration.
Preformed metal crowns can protect severely affected molars, reduce sensitivity and provide time for definitive planning. Other direct or indirect restorations may be appropriate according to age, cooperation and tissue condition. Anaesthesia can be difficult in a hypersensitive tooth; reassess the method and do not continue through pain. Frequent patch repairs can become a substantial burden even when each visit seems minor.
Plan poor-prognosis molars with the whole dentition
An extraction decision should compare durable retention with the lifetime maintenance burden, symptoms and orthodontic possibilities. Assess second-molar development and angulation, other missing or ectopic teeth, crowding and skeletal relationship. The 2023 RCS guidance highlights individual planning: the familiar approximate eight-to-ten-year window is not a universal instruction or guarantee of space closure.
Lower-arch space outcomes are less predictable than upper-arch outcomes. Do not routinely remove a sound opposite-side first molar merely to balance the arch, or a sound opposing molar without a clear reason. Urgent pain or infection may require action before ideal developmental timing. Stabilise when safe to permit joint paediatric and orthodontic advice, then monitor the resulting eruption.
Address incisor appearance and the child’s experience
Ask whether incisor opacities actually concern the child and how they affect confidence. Appearance management may include monitoring, microabrasion, resin infiltration, carefully selected composite or other approaches after an appropriate assessment of lesion depth, colour and age. These methods have different limitations; an opacity may not disappear completely.
Explain options without creating an aesthetic concern that the child did not have. Record baseline photographs with valid consent and review tooth breakdown, sensitivity, restorations and treatment experience. A successful plan can include preserving one molar and extracting another with a different prognosis. The MIH label should not force identical treatment on every affected tooth.
A distinction to remember
A fixed extraction age or opacity colour alone cannot determine treatment. MIH needs tooth-level prognosis and coordinated developmental planning.
A nine-year-old has repeated breakdown of a sensitive lower first molar despite several repairs. What should be discussed now?
Reveal the reasoning
Reassess pulp status, remaining structure, pain and the likely durability of another restoration. Compare protective full coverage with planned extraction using orthodontic development and the whole dentition. Avoid promising spontaneous space closure from age alone, and address sensitivity while the decision is coordinated.
Test your recall
What teeth must be involved for the usual diagnosis of MIH?
Show answer
At least one first permanent molar is affected, with or without permanent incisor involvement. An isolated incisor opacity needs a broader differential. Examine the full distribution and any atypical restorations or previous molar extractions that may conceal the original defect.