
Dental trauma in children
Treat the child first, then define the injured tooth and supporting tissues. Permanent and primary injuries require separate pathways, and early comfort does not remove the need for long-term review.
Quick revision summary
Identify dentition and injury first
Distinguish primary from permanent teeth and record displacement, mobility, fractures, occlusion and soft-tissue injury. Check for associated head injury and missing fragments before deciding on dental treatment and follow-up.
Avulsion is time sensitive
An avulsed permanent tooth requires urgent appropriate action, with extraoral time, storage and root maturity affecting prognosis. Primary teeth are not replanted. Use the injury-specific trauma guidance rather than transferring one protocol to every injury.
Follow-up detects delayed complications
Initial sensibility tests can be misleading after trauma. Serial examination and appropriate imaging help identify infection, resorption or developmental effects; the splint type, duration and review schedule depend on the actual injury.
Common mistake
Never transfer permanent-avulsion instructions to a primary tooth. Equally, an initially negative sensibility test is not enough to diagnose permanent-tooth pulp necrosis.
Dental trauma in children
Treat the child first, then define the injured tooth and supporting tissues. Permanent and primary injuries require separate pathways, and early comfort does not remove the need for long-term review.
Initial assessment and documentation
Check for airway concerns, head injury, cervical injury, facial fracture and significant bleeding before concentrating on teeth. Ask when, where and how the injury occurred, including loss of consciousness, vomiting and missing tooth fragments. Unaccounted teeth may be intruded, embedded, swallowed or aspirated. Respiratory symptoms or aspiration concerns require urgent medical assessment.
Identify dentition and root maturity. Record displacement, mobility, percussion, occlusion, soft-tissue injury, baseline sensibility and relevant photographs. Palpate for alveolar segment movement and examine lips for embedded fragments. Use justified radiographs to answer fracture or displacement questions; a single view can miss a root fracture. Consider safeguarding if the account or developmental abilities do not fit the injury.
Tooth & supporting tissues
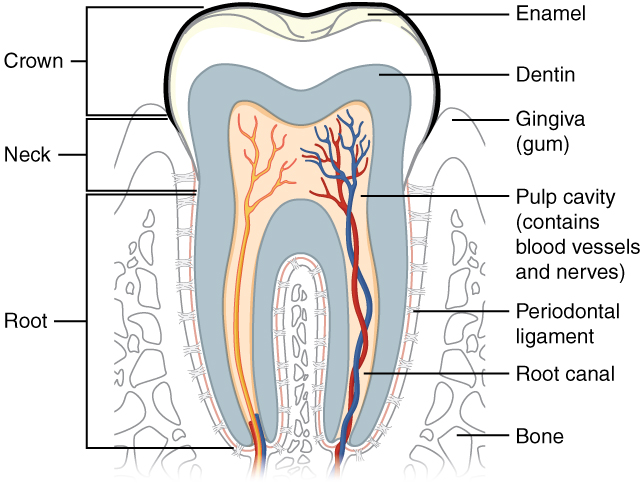
Trace the pulp and root canal to the apical region, then identify the periodontal ligament and supporting bone. Relate these structures to avulsion, apical pathology and extraction. The original uses the spelling “dentin”; cementum is not separately labelled.
Tooth & supporting tissues · OpenStax College · CC BY 3.0. Original image; displayed at a responsive size. Original publication.
Distinguish the periodontal injuries
Concussion causes tenderness without abnormal mobility or displacement. Subluxation adds mobility without displacement. Extrusion displaces a tooth partly out of its socket; lateral luxation displaces it sideways, often locking it into injured bone. Intrusion drives the tooth into alveolar bone. Avulsion means complete displacement from the socket.
These labels affect repositioning, splinting, pulpal risk and review. Do not apply one splint duration to every injury. Mature intruded permanent teeth and immature teeth differ in their potential for spontaneous re-eruption and pulp survival. Urgent injury-specific advice is appropriate when repositioning or surgical/orthodontic management is required.
Fractures and exposed pulp
An enamel fracture may need smoothing or adhesive repair; exposed dentine needs protection and a seal. Locate and retain fragments when possible because reattachment may be feasible. A complicated crown fracture exposes pulp, creating a vital-pulp decision rather than automatic root canal treatment, particularly when the root is immature.
Assess a crown-root fracture for restorability, fracture extent and periodontal involvement. In a root fracture, the coronal segment may be displaced while the apical portion remains in place. Repositioning and flexible splinting may preserve healing; endodontic treatment, if later needed, usually concerns the necrotic coronal segment. Fracture location and associated injuries change prognosis.
Permanent-tooth avulsion is time-critical
Handle the crown and avoid scrubbing the root. Prompt appropriate replantation gives the best periodontal opportunity; if it cannot be done immediately, prevent drying with a suitable medium such as milk or a physiological storage solution and seek urgent dental care. Record extraoral dry time separately from time stored wet. Never replant an avulsed primary tooth.
For an uncomplicated replanted permanent tooth, IADT commonly recommends passive flexible splinting for two weeks, with a different plan for associated alveolar fracture. Closed-apex teeth generally require root canal treatment initiated within two weeks. Open-apex teeth may revascularise and need close monitoring rather than automatic immediate endodontics. Check tetanus and appropriate antibiotic advice. Prolonged dry time worsens prognosis but does not automatically mean discard the tooth.
Primary trauma prioritises the child and successor
Primary roots lie close to developing permanent teeth. Intrusion or avulsion can disturb successor formation; explain that possibility without predicting inevitable damage. Many displaced primary teeth can be observed when safe, with analgesia, hygiene advice and review. Occlusal interference, aspiration risk, infection and inability to manage safely can require intervention.
Do not extract an intruded primary tooth solely because its root appears directed towards the successor: current IADT guidance no longer recommends that rule. Darkening alone does not automatically justify pulp treatment or extraction. Persistent pain, swelling, sinus or pathological mobility is more concerning. Sensibility testing is of limited value in primary teeth, so use the appropriate primary-injury protocol.
Monitor pulp, resorption and growth
Cold and electric tests assess neural response and can be falsely negative early after trauma. Repeat tests with clinical and radiographic findings. Pulp canal obliteration may follow healing and does not itself require prophylactic root canal treatment. Infection-related resorption and ankylosis-related replacement resorption are different complications with different management implications.
An ankylosed tooth may appear progressively infra-positioned as the child grows. Specialist planning can include decoronation or other future reconstruction when appropriate. Give written injury-specific review and return advice for pain, swelling, sinus, bite change or loosening. Follow-up can extend for years because a replanted tooth that initially looks normal can later develop serious complications.
A distinction to remember
Never transfer permanent-avulsion instructions to a primary tooth. Equally, an initially negative sensibility test is not enough to diagnose permanent-tooth pulp necrosis.
A nine-year-old’s upper permanent incisor was knocked out and has been in milk for twenty minutes. What is urgent?
Reveal the reasoning
Arrange immediate dental trauma care, handling the crown and preserving the root surface. Prompt appropriate replantation, assessment of associated injury and an injury-specific splint/endodontic plan are priorities. Establish actual dry time, root maturity and tetanus status, and explain that long-term review is essential.
Guidance to read alongside this chapter
Test your recall
How does subluxation differ from extrusion?
Show answer
Subluxation produces abnormal mobility without displacement. Extrusion partly displaces the tooth out of its socket. The distinction matters because extrusion usually requires repositioning and injury-specific stabilisation, while subluxation may need supportive care or selected stabilisation according to the findings.