
Immunology and inflammation
Immune defence contains rapid recognition systems, antigen-specific responses and mechanisms that restrain damage. The same response can protect against microbes yet injure host tissues when it is excessive, misdirected or persistent.
Quick revision summary
Barriers and innate recognition
Intact oral epithelium, salivary flow, mucins, antimicrobial proteins and resident microbial competition form an initial defence. Barrier damage or loss of saliva changes the environment before any blood test becomes abnormal.
B cells, antibodies and oral mucosal defence
Activated B cells can become antibody-secreting plasma cells and memory B cells. Antibodies bind specific antigen and can neutralise toxins or viral attachment, promote opsonisation and activate complement. They do not all kill a target directly.
Use immune mechanisms to choose investigations and actions
Recurrent ulcers, mucosal blistering or persistent lip swelling should be assessed with their oral distribution, medicines and systemic features. Skin, eye, gastrointestinal and joint symptoms can change the differential. Histology, immunofluorescence, blood tests and microbiology answer different questions and require the appropriate sampling approach.
Common mistake
Inflammation is not synonymous with infection, and an adverse effect is not synonymous with allergy. Anaphylaxis is a clinical emergency and must not wait for an IgE result.
Immunology and inflammation
Immune defence contains rapid recognition systems, antigen-specific responses and mechanisms that restrain damage. The same response can protect against microbes yet injure host tissues when it is excessive, misdirected or persistent.
Barriers and innate recognition
Intact oral epithelium, salivary flow, mucins, antimicrobial proteins and resident microbial competition form an initial defence. Barrier damage or loss of saliva changes the environment before any blood test becomes abnormal. Innate cells recognise conserved microbial patterns and signals from damaged cells through pattern-recognition receptors.
Neutrophils rapidly migrate to sites of infection and kill organisms by phagocytosis and other mechanisms. Macrophages clear debris, secrete mediators and help coordinate repair; dendritic cells link local recognition to adaptive immunity through antigen presentation. Innate responses are rapid and do not require the same antigen-specific clonal expansion as a first adaptive response.
Oral mucosa: epithelium, basement membrane and lamina propria
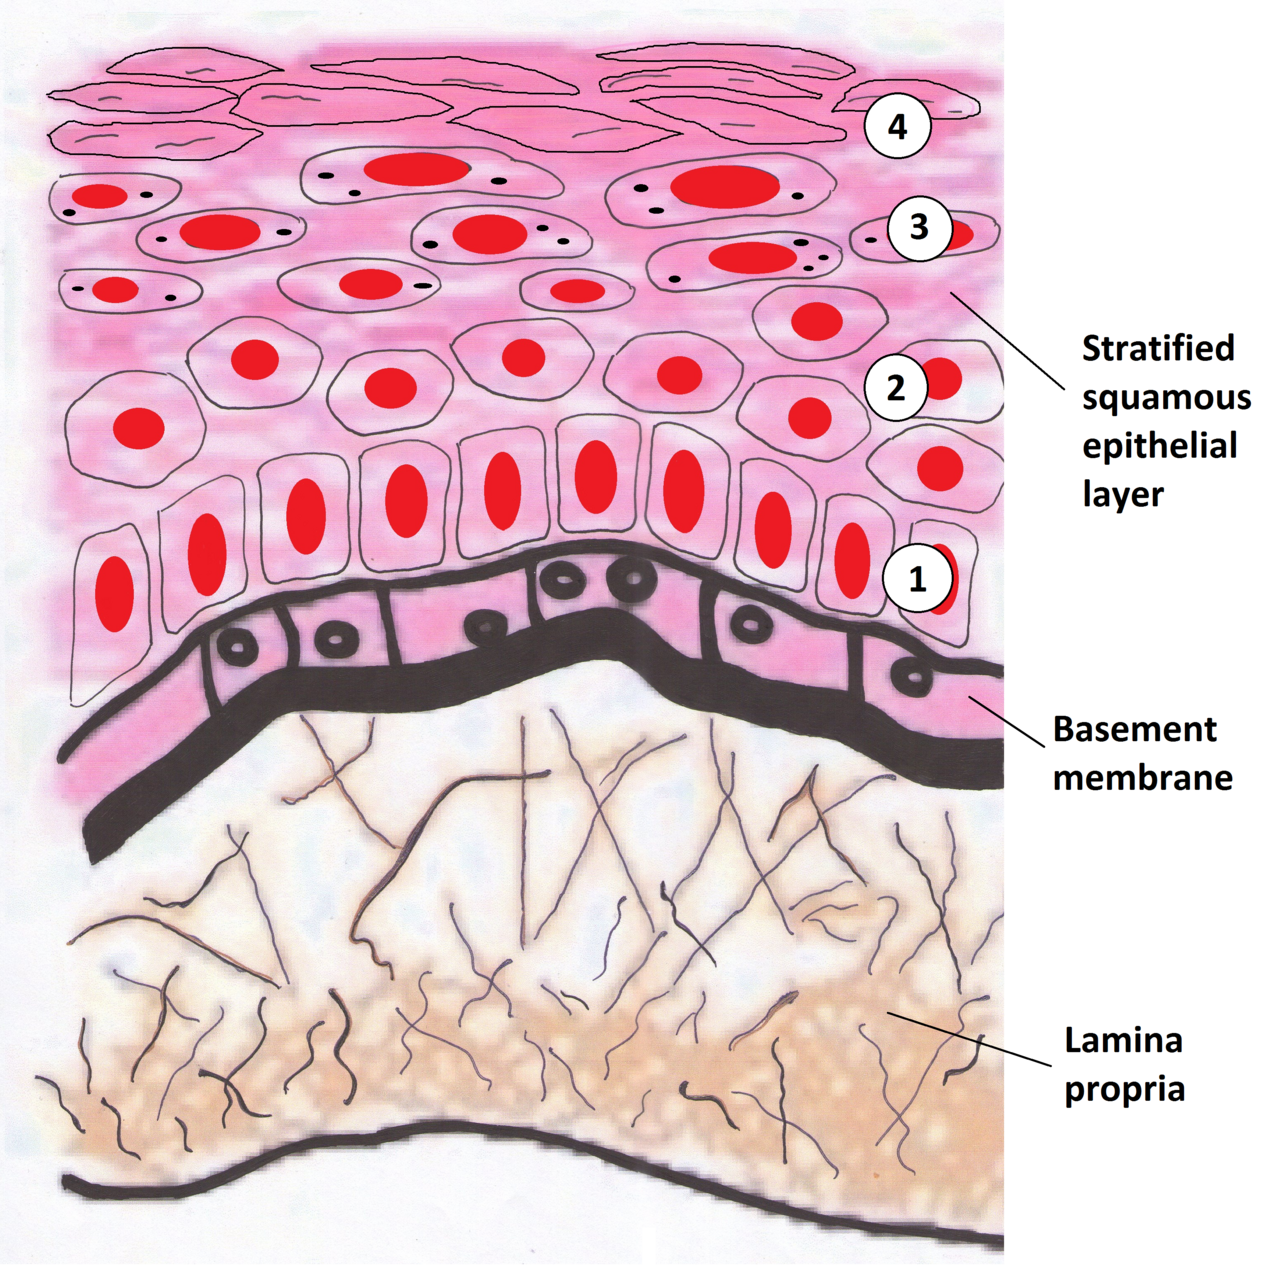
Identify the epithelium, basement membrane and lamina propria. Relate the epithelial–stromal interface to in-situ disease and invasion. This drawing represents a keratinising surface; oral sites have different keratinisation patterns. Use the printed anatomical names for revision.
Oral mucosa: epithelium, basement membrane and lamina propria · Wiki-minor (own work, 2011) · CC BY-SA 3.0. Unchanged published raster preview; displayed responsively. Original available from the source.
Vascular inflammation and complement
Vasodilatation increases local blood flow, while increased vascular permeability permits fluid and proteins to enter tissues. Endothelial adhesion and chemotactic signals recruit leucocytes. Heat, redness, swelling, pain and loss of function result from these vascular and mediator changes. Inflammation can follow sterile trauma as well as infection, so redness is not proof that an antibiotic is needed.
Complement is a circulating protein cascade activated through several pathways. Its effects include opsonisation, recruitment and activation of inflammatory cells and membrane attack against susceptible targets. Opsonisation means coating a target to make phagocytosis easier. Complement supports antibody-mediated defence but also participates in innate recognition, so it is not restricted to one side of an innate–adaptive division.
Antigen presentation and T-cell responses
Adaptive responses select and expand lymphocytes with receptors recognising particular antigens. Antigen-presenting cells provide peptide–MHC signals and additional activating information. MHC class I generally presents intracellular peptides to CD8 T cells; MHC class II presents peptides to CD4 helper T cells. Recognition without the appropriate context is not equivalent to a fully activated protective response.
CD8 cytotoxic cells can kill infected or abnormal host cells. CD4 subsets coordinate responses through cytokines, including help for macrophages and B cells; regulatory mechanisms restrain unwanted activity. Memory cells permit a faster response on later exposure. Vaccination exploits that memory without requiring the person to experience the full disease as the route to protection.
B cells, antibodies and oral mucosal defence
Activated B cells can become antibody-secreting plasma cells and memory B cells. Antibodies bind specific antigen and can neutralise toxins or viral attachment, promote opsonisation and activate complement. They do not all kill a target directly. Class switching changes the antibody’s effector function while maintaining antigen specificity.
Secretory IgA is important at mucosal surfaces, including saliva, where it limits microbial adherence and helps neutralise targets. IgG is prominent in serum and extracellular fluids, IgM is important early in many responses, and IgE is associated with mast-cell activation and parasite defence. A measured antibody can reflect exposure or immune activity; it does not automatically prove current symptomatic disease.
Hypersensitivity: identify the mechanism
Hypersensitivity describes harmful immune responses to an antigen. The four-type framework is useful for revision, but clinical diseases can involve overlapping pathways. A reaction history needs the actual exposure, symptoms, timing, severity and subsequent tolerance rather than the unspecific word “allergy”.
Type I commonly involves IgE-dependent mast-cell activation and rapid mediator release. Type II involves antibodies against cell-surface or matrix targets; type III involves inflammatory deposition of immune complexes. Type IV is T-cell mediated and often delayed. Not every adverse medicine effect is immune hypersensitivity, and a severe delayed drug reaction must not be dismissed merely because it was not immediate.
| Pattern | Principal mechanism | Illustrative connection |
|---|---|---|
| Type I | Mast-cell mediator release, often IgE-mediated | Some immediate allergies and anaphylaxis |
| Type II | Antibodies directed at tissue or cell targets | Antibody-mediated blistering disorders |
| Type III | Immune-complex deposition with inflammation | Some systemic inflammatory tissue injury |
| Type IV | T-cell-mediated response | Allergic contact reactions and some lichenoid reactions |
Chronic inflammation, autoimmunity and immunodeficiency
Persistent antigen, tissue injury or immune dysregulation can sustain macrophage and lymphocyte activity alongside attempted repair. In periodontitis, the host response contributes to destruction as well as defence against a dysbiotic biofilm. A granuloma is an organised macrophage response to a persistent stimulus; infectious, foreign-body and inflammatory causes must be considered.
Autoimmunity involves loss of tolerance to self, while immunodeficiency is inadequate defence arising from inherited disease, acquired illness or treatment. Different defects have different consequences: neutropenia, impaired T-cell function and antibody deficiency are not interchangeable. Immunosuppressive drugs may reduce visible inflammation while increasing infection susceptibility, making a quiet-looking lesion potentially misleading.
Use immune mechanisms to choose investigations and actions
Recurrent ulcers, mucosal blistering or persistent lip swelling should be assessed with their oral distribution, medicines and systemic features. Skin, eye, gastrointestinal and joint symptoms can change the differential. Histology, immunofluorescence, blood tests and microbiology answer different questions and require the appropriate sampling approach.
Do not infer an immune diagnosis solely from one positive antibody or a nonspecific inflammatory biopsy. Equally, negative screening tests do not exclude every immune disease. If infection is plausible, assess it before escalating immunosuppression. For a rapid reaction with airway, breathing or circulation compromise, recognise anaphylaxis and follow the current emergency algorithm rather than waiting for immunological confirmation.
A distinction to remember
Inflammation is not synonymous with infection, and an adverse effect is not synonymous with allergy. Anaphylaxis is a clinical emergency and must not wait for an IgE result.
A patient develops wheeze, throat swelling and collapse shortly after a medicine. Is this simply an exaggerated local inflammatory response?
Reveal the reasoning
No. Rapid airway, breathing and circulatory compromise after exposure is consistent with anaphylaxis and requires immediate treatment under the current emergency algorithm. Document the suspected trigger and timing after urgent care; immunological confirmation is a later question.
Test your recall
Which cells link local innate recognition to activation of T cells?
Show answer
Dendritic cells are important antigen-presenting cells that carry information from tissues to adaptive lymphocyte responses. Macrophages and B cells can also present antigen. Presentation includes the context of activation, so antigen recognition alone is not the whole process.