
Risk assessment
Risk assessment predicts plausible future harm and identifies actions that can reduce it. Separate the risk of developing oral disease from the risk associated with a particular procedure, medicine or care setting.
Quick revision summary
Define the outcome, time frame and evidence
A statement such as “high risk” is incomplete unless it says risk of what and under which circumstances. Caries progression, periodontal recurrence, cancer, bleeding, impaired healing and difficulty maintaining a restoration are different outcomes.
Medical and medicine-related procedural risk
Match the medical history to the actual intervention. Consider bleeding, infection, healing, cardiovascular or respiratory tolerance, drug interactions and recovery support. A restoration, a single extraction, extensive surgery and sedation create different physiological demands.
Record mitigation, residual uncertainty and review
For each important risk, document the factor, possible consequence and agreed response. Explain benefits, burdens and alternatives in terms relevant to the patient. Distinguish an established contraindication from an uncertainty requiring information, and a modifiable factor from one that must be accommodated.
Common mistake
Risk is specific to an outcome, procedure and time point. A favourable past test or a single medicine label is not an adequate current procedural assessment.
Risk assessment
Risk assessment predicts plausible future harm and identifies actions that can reduce it. Separate the risk of developing oral disease from the risk associated with a particular procedure, medicine or care setting.
Define the outcome, time frame and evidence
A statement such as “high risk” is incomplete unless it says risk of what and under which circumstances. Caries progression, periodontal recurrence, cancer, bleeding, impaired healing and difficulty maintaining a restoration are different outcomes. A patient may have low current caries risk but substantial extraction-related bleeding considerations.
Start with current disease activity, past experience, protective factors and modifying factors, then identify how each could change the outcome. Risk is not certainty: some exposures are associated with disease without being sufficient causes, and a scoring tool cannot capture every interaction. Document the reasoning and a practical response instead of treating the score as the treatment plan.
Osteoclast resorption and osteoblast formation during bone remodelling
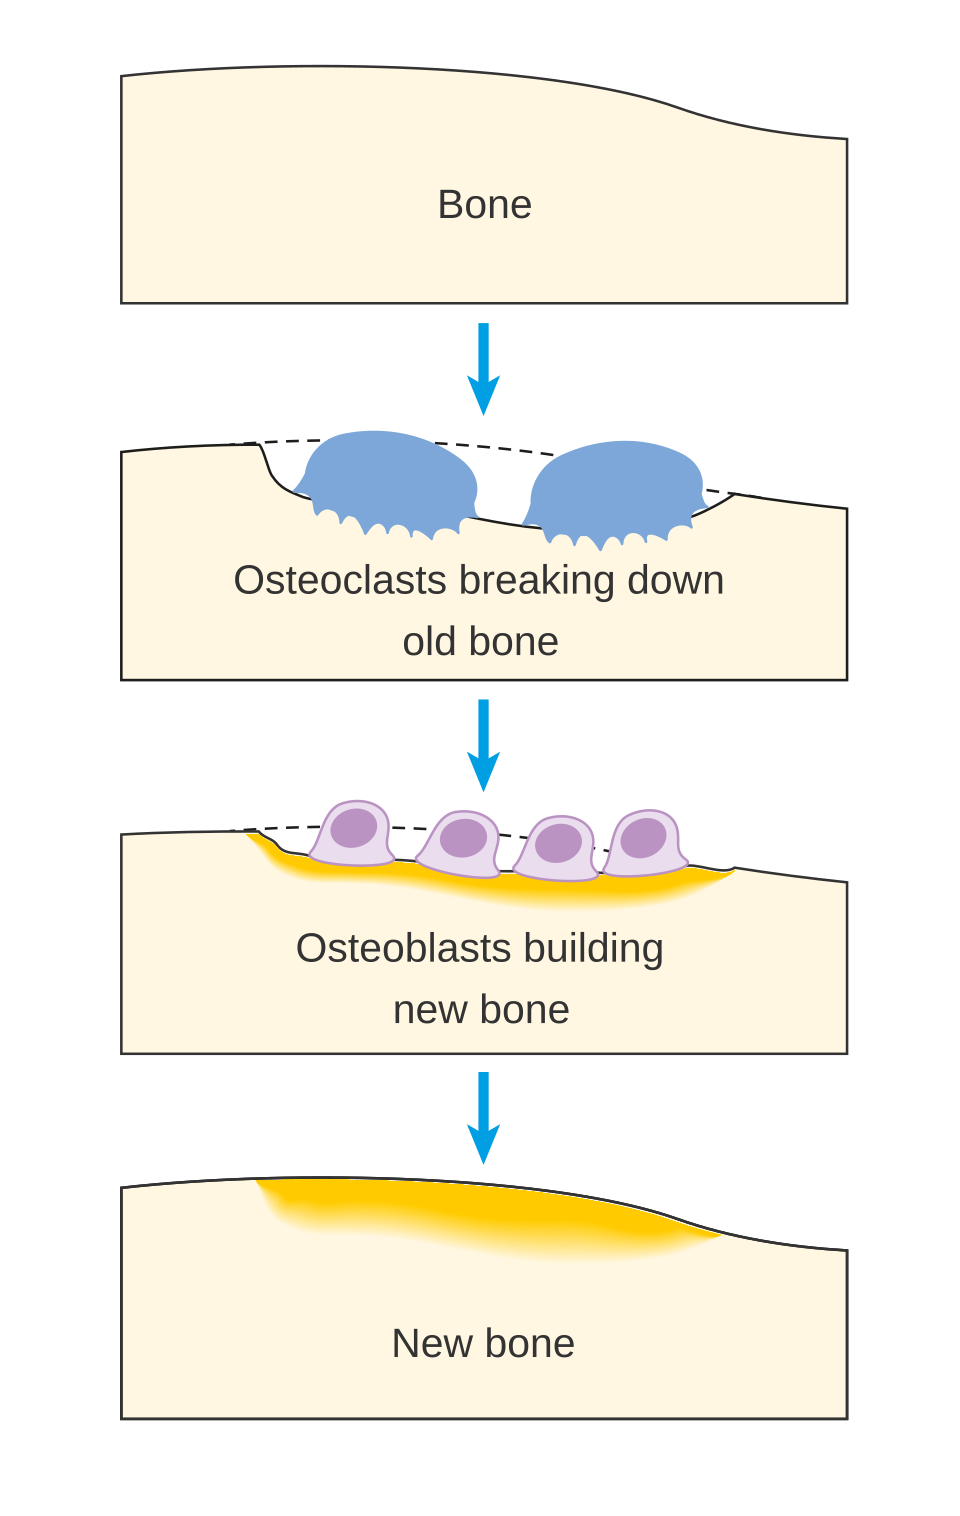
Follow osteoclast resorption and osteoblast replacement, then connect the cycle to antiresorptive therapy and MRONJ. Add osteocyte regulation and the RANK–RANKL–OPG system to this simplified sequence.
Osteoclast resorption and osteoblast formation during bone remodelling · Cancer Research UK (2014; source revision 2016) · CC BY-SA 4.0. Unchanged published raster preview; displayed responsively. Original available from the source.
Caries susceptibility and protective factors
Recent or active caries is important evidence of future susceptibility. Assess dietary frequency, fluoride exposure, plaque control, saliva, exposed roots, appliances and factors affecting self-care. A patient with numerous old restorations does not necessarily have the same current activity as someone developing new lesions every year.
A change in medicines, salivary function, diet or support can alter risk quickly. Consider what can be modified and how prevention will be delivered. In children, combine disease experience, family and social context with clinical findings without assuming that a postcode explains an individual’s whole situation. Review risk regularly and use it to inform prevention and justified review decisions.
Periodontal, wear and oral cancer risk
Periodontal assessment combines historical attachment loss, current pocket and bleeding findings, smoking, diabetes and local factors. A treated patient can be stable while retaining a history and susceptibility that require maintenance. Current appearance does not erase previous disease, and stage, grade and current status describe different aspects.
For tooth wear, assess active exposure and evidence of progression as well as existing tissue loss. Dietary acids, reflux, abrasion and parafunction can interact. For oral cancer, tobacco, alcohol and other exposures inform prevention and suspicion, but absence of classic risk factors does not exclude a concerning lesion. A visible suspicious finding requires its own action rather than waiting for a calculated risk threshold.
Medical and medicine-related procedural risk
Match the medical history to the actual intervention. Consider bleeding, infection, healing, cardiovascular or respiratory tolerance, drug interactions and recovery support. A restoration, a single extraction, extensive surgery and sedation create different physiological demands. Clarify disease stability, organ function and the exact medicines and their indications.
For antithrombotic therapy, use current procedure-specific guidance and local haemostasis rather than stopping medicines automatically. For antiresorptive or associated medicines, distinguish indication, exposure and other risk factors; for prior jaw radiotherapy, establish field and treatment details with specialist input. The harm of leaving disease untreated must be considered alongside procedural harm.
| Risk domain | Decision-changing detail | Action the assessment should produce |
|---|---|---|
| Caries | New lesions, saliva change and diet/fluoride pattern | Personalised prevention and review |
| Periodontal | Historical loss plus current pocket/bleeding status | Maintenance and modifiable-factor management |
| Bleeding | Medicine, procedure and relevant current test when indicated | Guideline-based timing and local haemostasis |
| Infection / healing | Immune status, treatment timing, perfusion and bone-risk exposure | Appropriate setting, liaison and follow-up |
| Practical feasibility | Communication, dexterity, attendance and support | Reasonable adjustments and a maintainable design |
Timing, investigations and useful medical liaison
Risk belongs to a time point. A remote normal blood count may not reflect a patient receiving cyclical anticancer treatment at the intended procedure date. Where indicated, coordinate relevant neutrophil and platelet information, symptoms, organ function and treatment timing with the responsible team. One laboratory number does not describe the full clinical state.
Ask a specific question: describe the proposed dental procedure, likely bleeding or healing burden, urgency and the information needed. A request for generic “medical clearance” transfers little useful reasoning. Record the response, any agreed responsibilities and how it changes the dental plan. Investigate only where the result can alter management.
Communication, capacity, anxiety and maintenance
Assess the patient’s ability to understand the decision with appropriate support and to complete the planned care and maintenance. Disability, language, sensory impairment or anxiety may require accessible information, an interpreter, additional time or a different setting. These are adjustments to assessment and care, not evidence of incapacity by themselves.
Dexterity, carer help, transport, finances and willingness to attend influence whether a technically possible plan is sustainable. Identify barriers early and discuss alternatives without blame. A prosthesis that cannot be cleaned or a plan requiring unavailable support may create avoidable risk despite excellent operative technique.
Record mitigation, residual uncertainty and review
For each important risk, document the factor, possible consequence and agreed response. Explain benefits, burdens and alternatives in terms relevant to the patient. Distinguish an established contraindication from an uncertainty requiring information, and a modifiable factor from one that must be accommodated.
Set review points after disease control or a change in medical treatment. Record what finding would change the recommendation and how deterioration should be managed. A high-risk label should not leave a patient with untreated infection and no pathway; the assessment should identify a feasible route to care, including referral when necessary.
A distinction to remember
Risk is specific to an outcome, procedure and time point. A favourable past test or a single medicine label is not an adequate current procedural assessment.
A patient previously had little caries, but now takes several xerogenic medicines and has new root lesions. Should the old low-risk category be retained?
Reveal the reasoning
No. New disease and a changed protective environment require reassessment. Review saliva, actual medicines, cleaning, diet and fluoride, then agree enhanced prevention and appropriate review. Risk categories should reflect current evidence rather than remain attached to the person indefinitely.
Guidance to read alongside this chapter
Test your recall
What makes “high risk” an incomplete clinical statement?
Show answer
It does not name the outcome, procedure or time frame. Caries, bleeding and healing risks have different causes and mitigations. State the factor, possible consequence and planned response so the assessment produces a useful decision.