
Conscious sedation
Conscious sedation reduces anxiety while maintaining verbal contact and the required protective function. The intended endpoint and the ability to recognise deeper-than-intended sedation are central.
Quick revision summary
Assess more than anxiety
Review health, medicines, substance use, prior sedation / anaesthesia, airway, OSA risk, functional reserve and the procedure. Establish whether the patient can cooperate and communicate and whether the service has the necessary competence, staff and recovery arrangements.
Define the intended clinical state
Conscious sedation aims to reduce anxiety while maintaining the ability to respond appropriately and preserving protective function within the relevant technique and standard. It is distinct from general anaesthesia.
Watch ventilation and plan a safe recovery
Clinical observation includes breathing, airway patency, responsiveness and circulation. Pulse oximetry measures oxygenation, not ventilation; supplemental oxygen can delay a fall in saturation despite hypoventilation.
Common mistake
An alert appearance or a normal oxygen saturation alone does not establish safe recovery.
Conscious sedation: assessment, titration and monitoring
Conscious sedation reduces anxiety while maintaining verbal contact and the required protective function. The intended endpoint and the ability to recognise deeper-than-intended sedation are central.
Assess more than anxiety
Review health, medicines, substance use, prior sedation / anaesthesia, airway, OSA risk, functional reserve and the procedure. Establish whether the patient can cooperate and communicate and whether the service has the necessary competence, staff and recovery arrangements. Consent must include reasonable alternatives, including behavioural support or another setting.
Agree preparation and fasting instructions for the specific technique and service rather than applying a GA rule to every sedation route. Check escort and discharge arrangements, transport and the patient’s ability to follow the instructions. Cannulation anatomy and a visible secure access site matter for intravenous techniques.
Superficial and deep veins of the upper limb
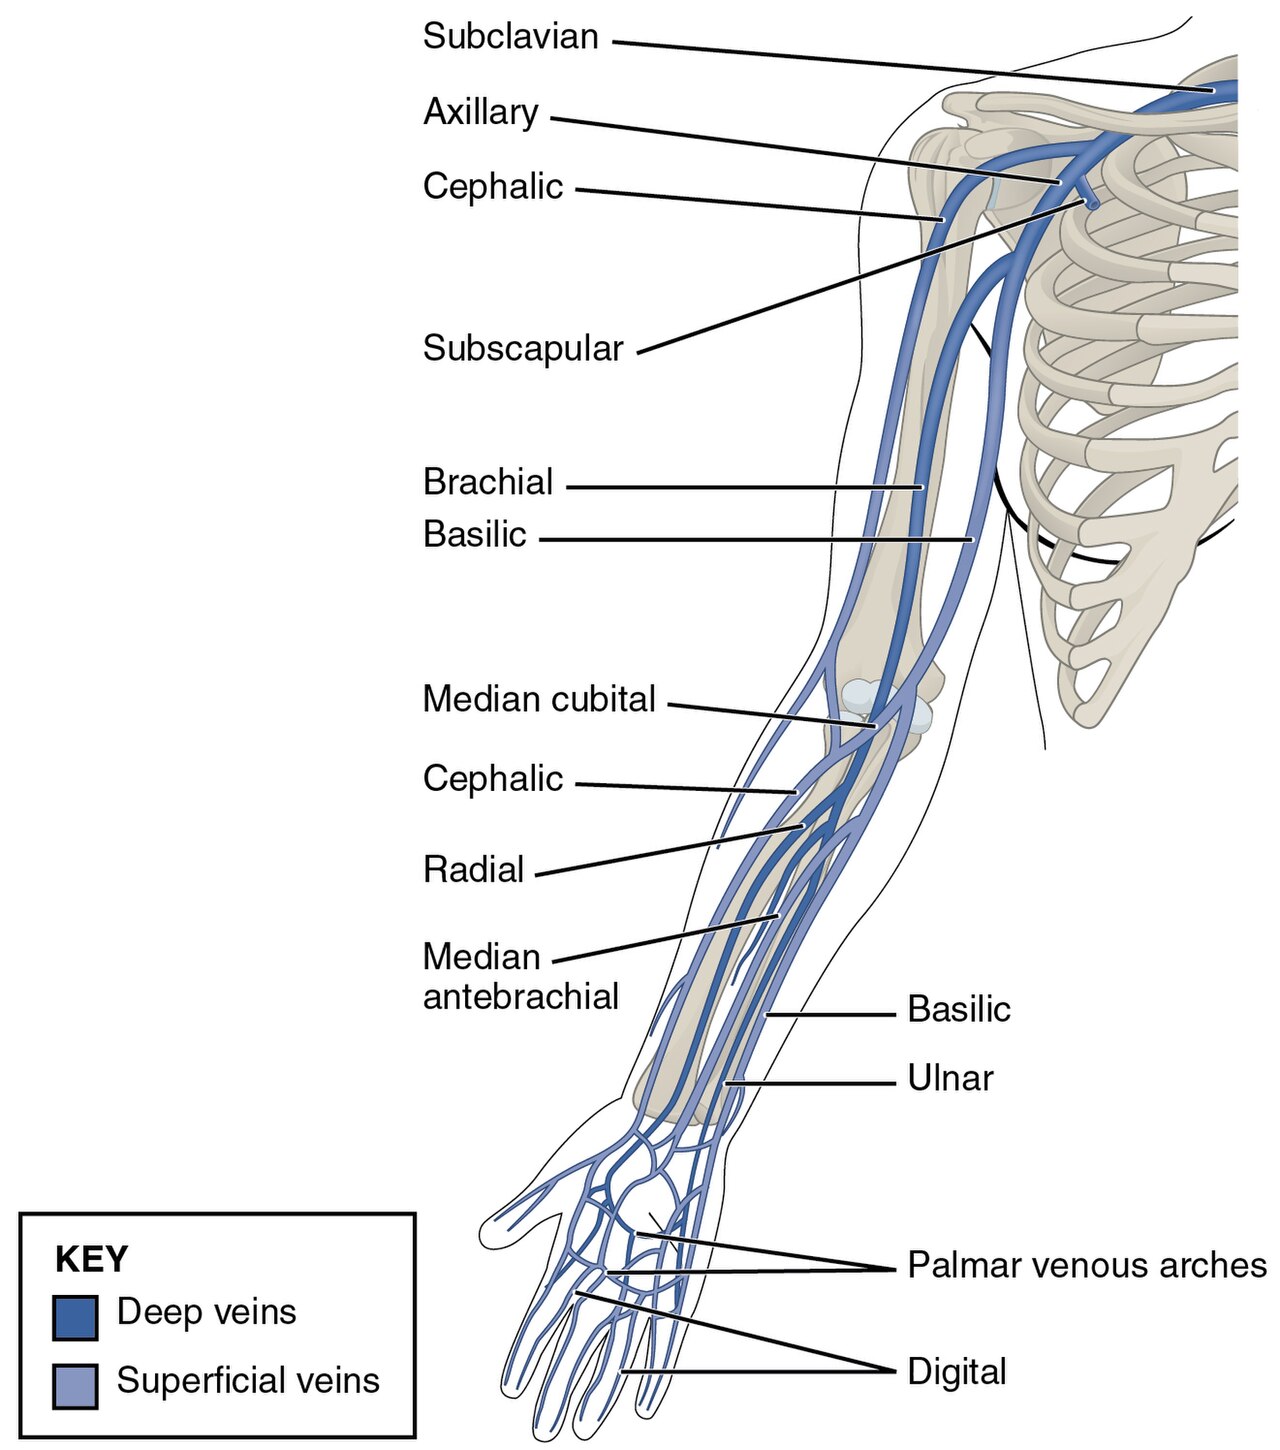
Identify cephalic, basilic, median cubital and median antebrachial veins. Use the colour key to distinguish superficial and deep drainage, and relate the anatomy to venous-access assessment. Individual superficial-vein patterns vary.
Superficial and deep veins of the upper limb · OpenStax College (2013) · CC BY 3.0. Unchanged published raster preview; displayed responsively. Original available from the source. Original publication.
Medicines and endpoint
| Concept | Key point | Common trap |
|---|---|---|
| Midazolam | Benzodiazepine with anxiolytic and amnesic effects through GABA-related mechanisms | Amnesia is not adequate analgesia. |
| Nitrous oxide / oxygen | A different titratable technique with its own assessment and delivery requirements | Assuming all sedation routes have identical preparation and recovery. |
| Titration | Incremental dosing to a suitable clinical effect with time to observe response | Giving rapid increments towards a memorised total. |
| Depressant combinations | Opioids, alcohol and other sedatives can add respiratory effects | Treating each dose as safe in isolation. |
| Conscious endpoint | Communication and clinical responsiveness are maintained | Interpreting immobility or silence as a satisfactory conscious-sedation endpoint. |
Observe the patient through recovery
Monitoring combines continuous clinical observation with the technique-appropriate equipment and recorded physiological measurements. Assess breathing, colour, responsiveness, airway and circulation; pulse oximetry alone is not a measure of ventilation. Supplemental oxygen can make a saturation display remain reassuring despite hypoventilation.
Continue appropriate observation into recovery and assess discharge against the service’s criteria, including orientation, physiological stability, mobility where relevant and practical support. Give written and verbal instructions and a contact route. The operation ending does not mean the medicine effect or supervision requirement has ended.
Define the intended clinical state
Conscious sedation aims to reduce anxiety while maintaining the ability to respond appropriately and preserving protective function within the relevant technique and standard. It is distinct from general anaesthesia. Technique selection depends on the patient, procedure, assessment, operator training and the facilities available; a familiar drug is not sufficient justification for providing sedation in an unsuitable setting.
Local anaesthesia still treats procedural pain. Sedation does not replace effective pain control, communication or consent. Confirm consent and practical arrangements before sedative effects impair decision-making. For intravenous techniques, titration and observation must account for drug onset and interaction rather than using a fixed amount for every patient. Deeper-than-intended sedation requires prompt recognition and rescue capability.
Watch ventilation and plan a safe recovery
Clinical observation includes breathing, airway patency, responsiveness and circulation. Pulse oximetry measures oxygenation, not ventilation; supplemental oxygen can delay a fall in saturation despite hypoventilation. Apply the monitoring required by the technique, patient and current standard rather than relying on one reassuring number.
Recovery continues after the dental procedure ends. Use defined discharge criteria and the required escort, transport and supervision arrangements for the technique. Explain restrictions and whom to contact, in written and verbal form. Reversal of a medicine does not automatically end risk because recurrent sedation may occur; continue appropriate observation and follow the rescue and discharge protocol.
A distinction to remember
An alert appearance or a normal oxygen saturation alone does not establish safe recovery.
Why is a patient taking opioid analgesia relevant to IV sedation planning?
Reveal the reasoning
Opioids and benzodiazepines can produce additive CNS and respiratory depression. Review the actual exposure, risk and technique and ensure suitable titration, monitoring and support.
Guidance to read alongside this chapter
Test your recall
What is central to safe discharge?
Show answer
Documented recovery against defined criteria with appropriate escort advice.