
Anaphylaxis
Anaphylaxis is a rapidly developing reaction with potentially life-threatening airway, breathing or circulation problems. Treat the clinical pattern promptly; skin changes can help recognition but are not required before giving first-line treatment.
Quick revision summary
Recognise physiological danger
Rapid airway swelling, bronchospasm or circulatory compromise after a plausible exposure suggests anaphylaxis. Skin changes can be absent, so do not wait for a rash before treating a compatible life-threatening reaction.
Give prompt intramuscular adrenaline
Call for emergency help, position appropriately and give adrenaline through the current age-specific intramuscular protocol. For adults, RCUK specifies 500 micrograms from 1 mg/mL solution, with repeat assessment and dosing when indicated.
Continue care after improvement
Maintain observation and arrange emergency hospital assessment even if initial treatment works. Do not allow the patient to stand or walk; provide a precise handover and distinguish suspected exposures from subsequently confirmed allergies.
Common mistake
Do not wait for a rash, use antihistamines first, or confuse intramuscular 1 mg/mL adrenaline with an intravenous adrenaline regimen.
Anaphylaxis
Anaphylaxis is a rapidly developing reaction with potentially life-threatening airway, breathing or circulation problems. Treat the clinical pattern promptly; skin changes can help recognition but are not required before giving first-line treatment.
Recognise what makes the reaction dangerous
Anaphylaxis can involve mediator-driven airway swelling, bronchospasm, vasodilation and capillary leak. In dentistry, possible exposures include medicines, chlorhexidine and latex, although a suspected trigger is not always confirmed. Look for a rapidly evolving pattern after exposure: voice change, tongue or throat swelling, stridor, wheeze, breathing difficulty or circulatory collapse. Urticaria, flushing and itching may occur, but absence of a rash does not exclude a severe reaction. Gastrointestinal symptoms and a feeling of impending doom can accompany the event. Focus on airway, breathing and circulation rather than waiting for every textbook feature.
Larynx: anterior and right lateral views
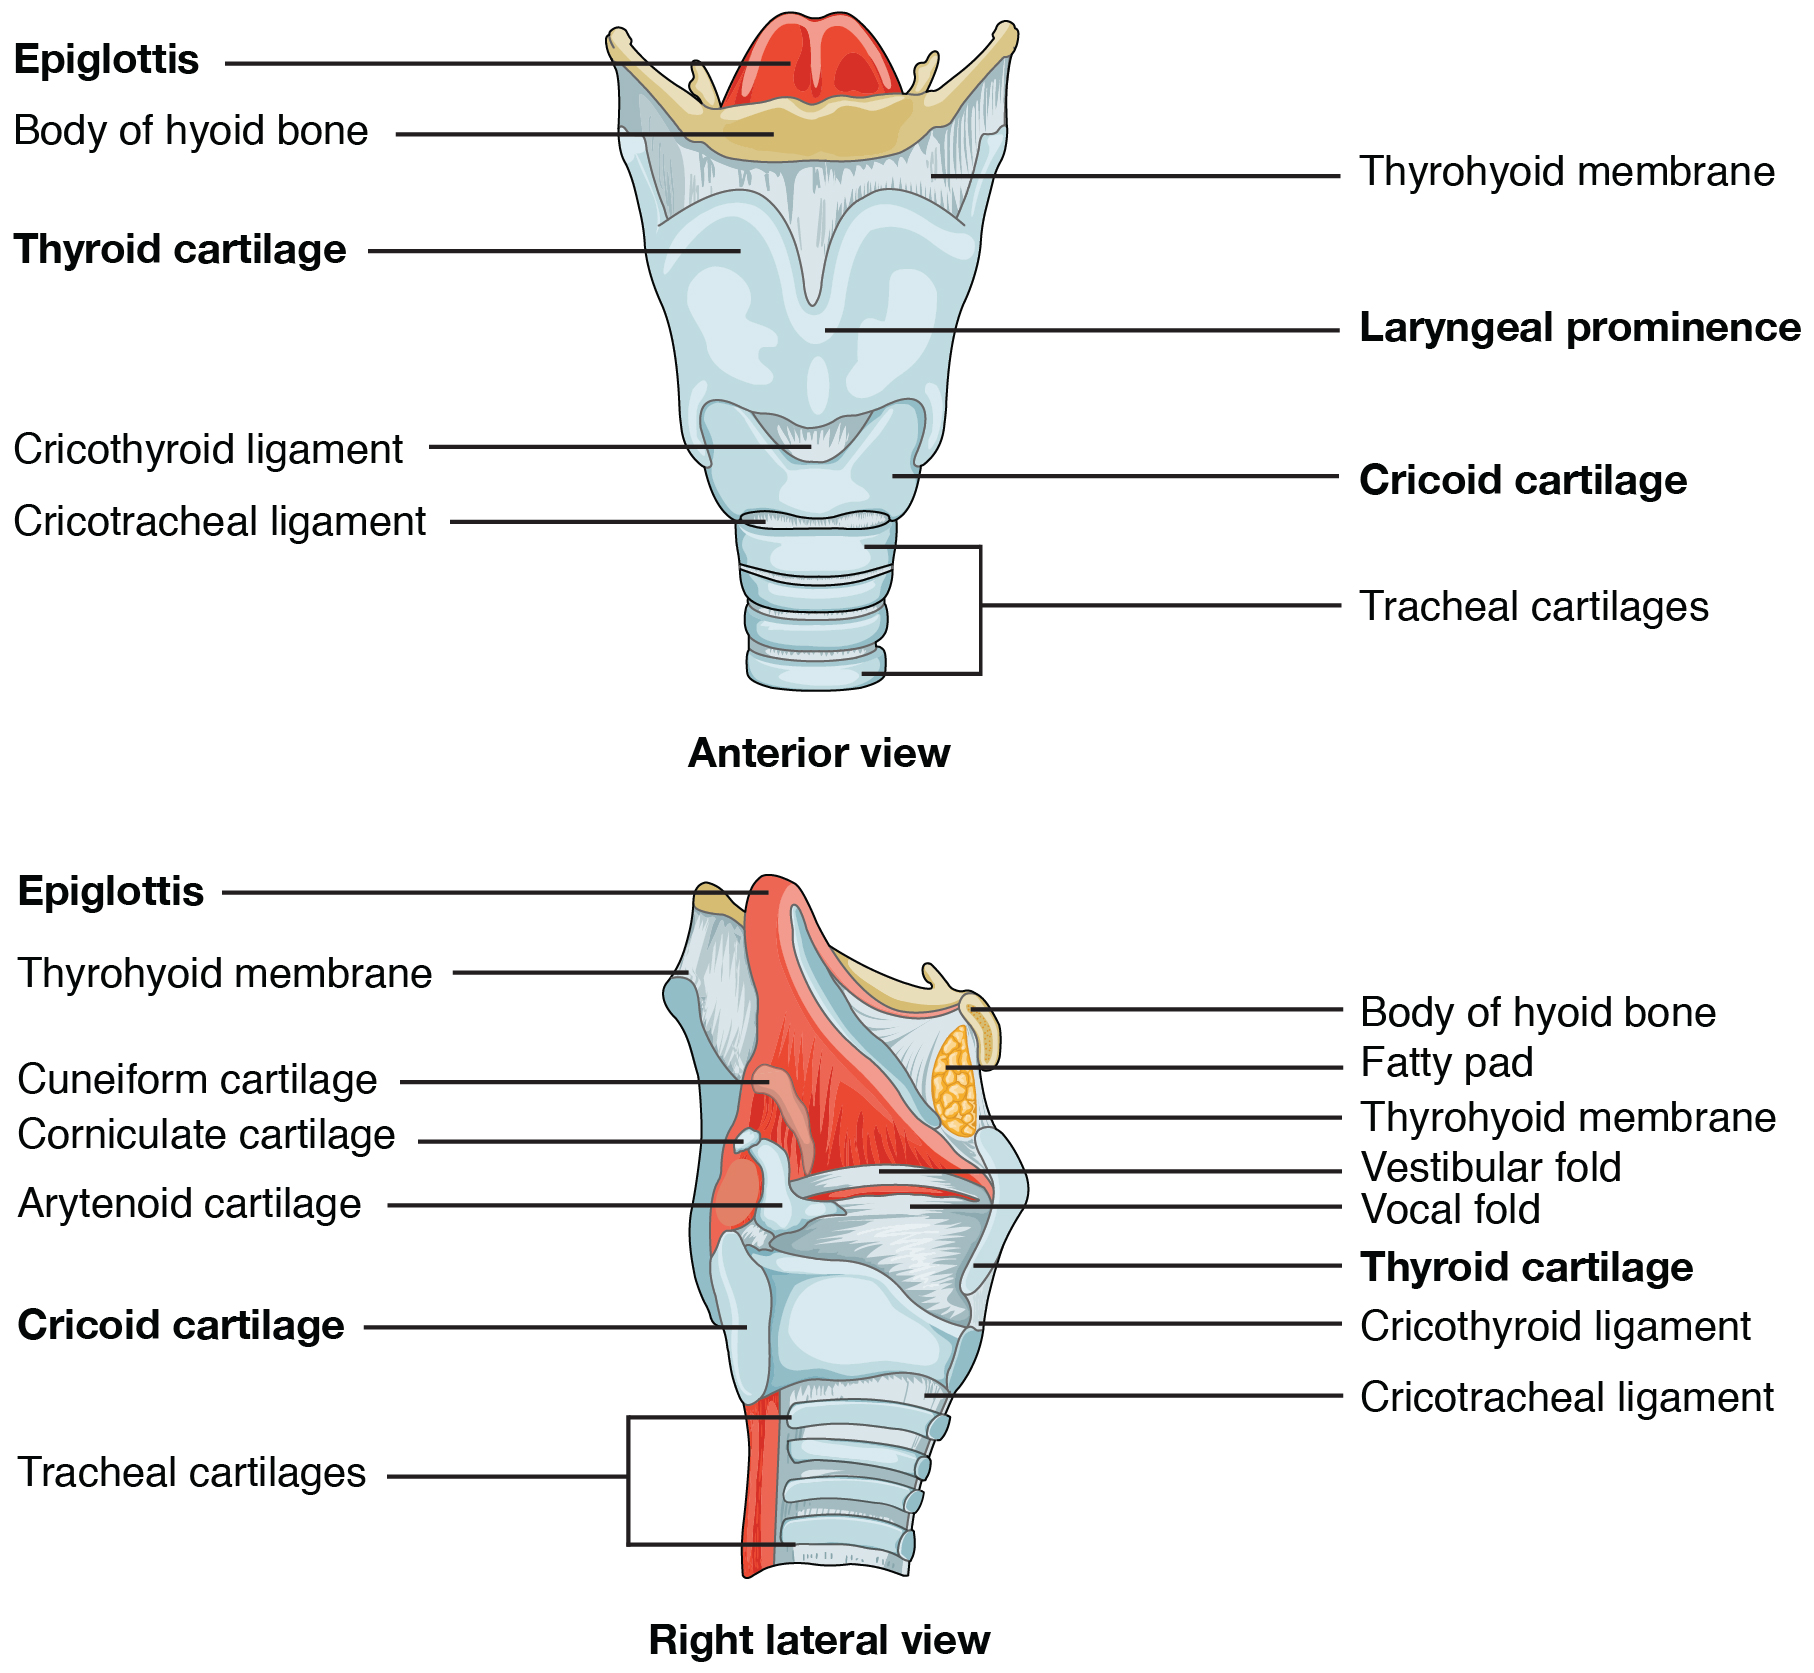
Locate the epiglottis, vocal folds, laryngeal cartilages and cricothyroid region. Relate the landmarks to airway anatomy in sedation and emergency assessment. Review tongue and pharyngeal obstruction in the accompanying lesson.
Larynx: anterior and right lateral views · OpenStax College (2013) · CC BY 3.0. Unchanged published image; displayed responsively. Original publication.
Distinguish important mimics without delaying treatment
Vasovagal syncope commonly involves pallor, nausea and a prompt positional recovery; anxiety or an adrenaline effect may produce palpitations and tremor. Local-anaesthetic systemic toxicity can cause neurological symptoms or seizures. These alternatives are useful when assessing the pattern, but they must not become reasons to delay adrenaline when anaphylaxis is suspected. Rapid airway swelling, bronchospasm or circulatory compromise after a plausible exposure is a different risk from isolated local itching. Reassess repeatedly because an initially limited reaction can evolve. The diagnosis is clinical during the emergency; confirmatory allergy investigations come later.
Stop exposure and activate emergency support
Stop the procedure and remove or stop the possible trigger if immediately feasible, without delaying treatment. Call 999 in community care, state suspected anaphylaxis and request emergency help; in hospital activate the local emergency team. Allocate tasks for medicines, oxygen, equipment, observations and handover. Use a position that supports circulation, generally lying down with legs raised, while adapting for respiratory distress or pregnancy. Do not allow the patient to stand or walk, even after apparent improvement. Assess airway and breathing and prepare for resuscitation if the patient becomes unresponsive with abnormal breathing.
Give adult intramuscular adrenaline promptly
For adults with suspected anaphylaxis, RCUK 2025 specifies adrenaline 500 micrograms intramuscularly using the 1 mg/mL preparation: this is 0.5 mL of 1:1000. The usual site is the anterolateral thigh. Repeat after five minutes if there is no improvement, with ongoing assessment and emergency support. State dose, route and concentration together to avoid confusion with other adrenaline preparations. Paediatric doses differ and must follow the current age-specific protocol. Do not substitute an improvised intravenous bolus: intravenous adrenaline requires experienced specialist management and monitoring, and dosing errors can be dangerous.
Support ABCDE and understand adjuncts
Provide oxygen and airway support according to the current emergency protocol and team competence. Monitor responsiveness, breathing, circulation and response to each intervention. Severe circulatory compromise can require intravenous fluid treatment by the appropriately equipped team, and refractory reactions need urgent advanced expertise. Antihistamines do not treat life-threatening airway or circulatory features and must not delay intramuscular adrenaline. Corticosteroids are not routine first-line emergency treatment. Bronchodilator treatment may help bronchospasm but does not replace adrenaline for anaphylaxis. If cardiac arrest occurs, start CPR and AED use according to the current resuscitation algorithm while specialist support continues.
Arrange hospital assessment after improvement
A patient who improves after initial treatment still needs emergency transfer and assessment. Symptoms may recur, and further treatment and observation depend on severity, response and clinical circumstances. Do not promise one fixed observation period for every reaction or send the person home because the rash has faded. Provide a structured handover describing suspected exposures, timing, ABC findings, medicines with dose and route, and the observed response. Preserve the relevant product information and clinical record. The receiving service can organise further assessment, advice, specialist allergy referral and an emergency plan appropriate to the confirmed or suspected risk.
Record accurately and prepare for the next event
Document the sequence and distinguish a suspected trigger from a proven allergy. Include other simultaneous exposures so future assessment does not focus only on the local anaesthetic. Explain the need for follow-up and avoidance advice from the relevant team without making unsupported claims that every related medicine is unsafe. Review emergency stock, expiry dates, dosing aids and staff roles after the event. Regular scenario practice should make calling, positioning, intramuscular dosing, monitoring and handover familiar. A well-written allergy entry prevents future harm only if it describes what actually happened and the level of diagnostic certainty.
A distinction to remember
Do not wait for a rash, use antihistamines first, or confuse intramuscular 1 mg/mL adrenaline with an intravenous adrenaline regimen.
Minutes after exposure, an adult develops wheeze, a hoarse voice and hypotension without a rash. What should be given first?
Reveal the reasoning
Treat suspected anaphylaxis promptly: activate emergency help and give adult adrenaline 500 micrograms intramuscularly using 0.5 mL of the 1 mg/mL preparation, with appropriate positioning and ABCDE support. Repeat after five minutes if there is no improvement.
Guidance to read alongside this chapter
Test your recall
Can anaphylaxis occur without a rash?
Show answer
Yes. Life-threatening airway, breathing or circulation problems can occur without skin or mucosal changes. A rapidly evolving compatible pattern after exposure warrants prompt treatment. Waiting for urticaria can delay adrenaline when the patient already has dangerous physiological compromise.