
Oral lesions and suspected cancer
Describe, investigate and track suspicious findings.
Clinical images and diagrams
Cervical lymph nodes and anatomical levels
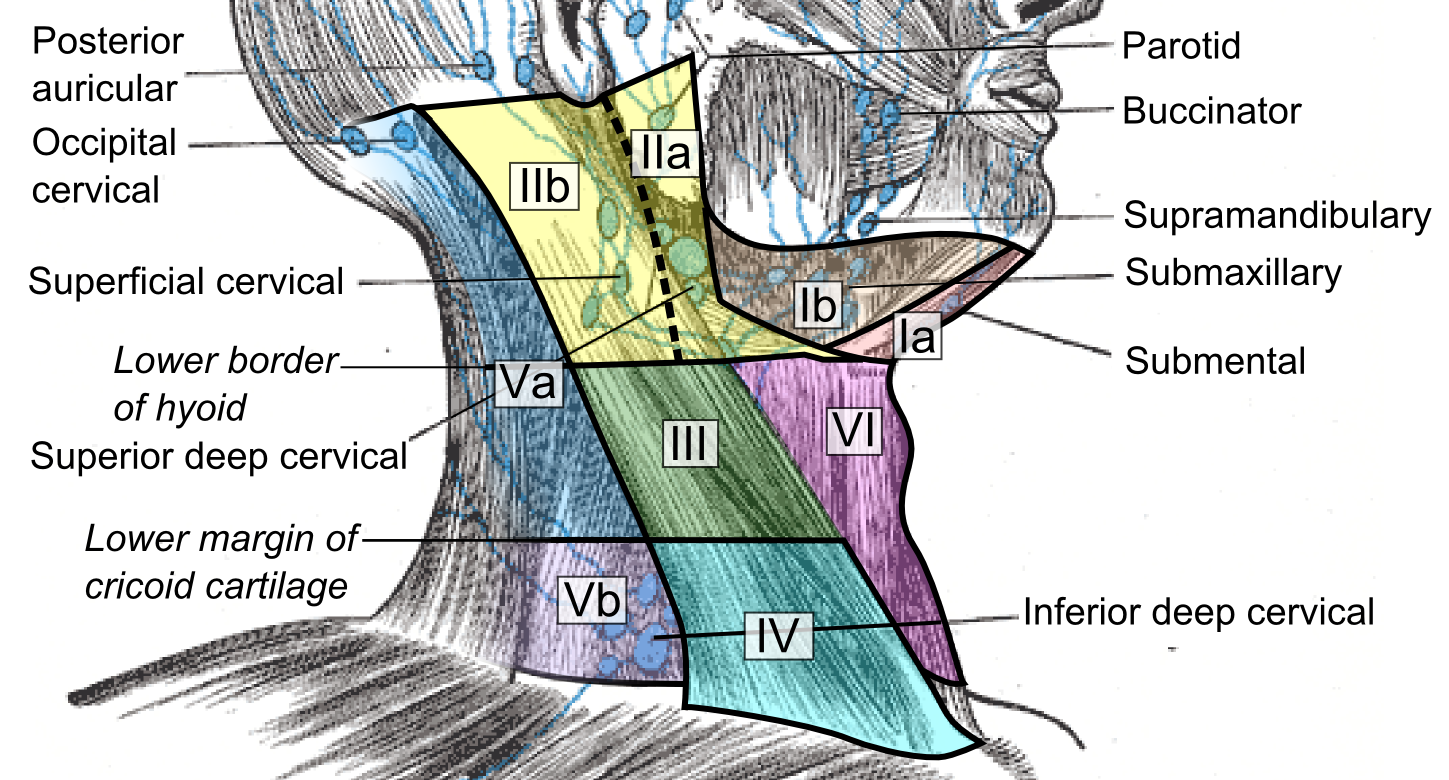
Compare the named node groups with the numbered cervical levels. This schematic does not replace cross-sectional imaging criteria for staging or treatment planning.
Cervical lymph nodes and levels.png · Mikael Häggström, M.D. · CC0. None; reproduced without alteration.
What should you record about a clinically palpable cervical node?
Its exact site and laterality, size, tenderness, consistency and mobility, alongside the relevant oral examination and history.
What to expect
Clinics may include 2-week-wait referrals, mucosal lesions, salivary swelling and biopsies. A DCT should learn a reproducible oral and neck examination, document findings precisely and understand who owns pathology results and follow-up.
What to know
Record exact site, dimensions, colour, surface, border, induration, fixation, symptoms and duration; examine the rest of the mucosa and cervical nodes. NICE recommends considering a suspected cancer pathway referral for unexplained oral ulceration lasting more than three weeks, among other oral findings. A benign or non-specific biopsy that conflicts with a clinically suspicious lesion needs discussion, not automatic discharge. Histology depends on representative sampling and clinical context.
A practical approach
Form a differential, photograph with appropriate consent and document a clear biopsy or referral question. Check anticoagulant and bleeding risk before a procedure. Label specimen site and orientation accurately. Arrange a reliable mechanism to review histology and tell the patient the result, whether benign, indeterminate or malignant. Use MDT and local pathways for cancer workup.
Safety point
Do not repeatedly treat a persistent indurated or changing lesion as trauma or candidosis without a short, documented review and escalation plan.
Red flags, lesion description and biopsy planning
Describe a lesion before naming it. A serious diagnosis can be painless, and a painful lesion can still be malignant. Duration, texture and associated findings matter.
A reproducible mucosal assessment
Record site, size, colour, surface, border, number, symmetry, tenderness, induration and fixation, with a suitable photograph or diagram. Ask about duration, change, trauma, tobacco / alcohol exposure, medicines, systemic symptoms and previous treatment. Palpate relevant nodes and assess cranial nerve or functional changes when indicated.
Unexplained oral ulceration persisting for more than three weeks meets a NICE suspected-cancer referral consideration. A dentist assessing a suspicious oral lump or red / red-white patch consistent with erythroplakia or erythroleukoplakia should also consider the cancer pathway. A lesion already strongly suspicious should not be left until a timing threshold has elapsed.
Cervical lymph nodes and anatomical levels
Compare the named node groups with the numbered cervical levels. This schematic does not replace cross-sectional imaging criteria for staging or treatment planning.
Cervical lymph nodes and levels.png · Mikael Häggström, M.D. · CC0. None; reproduced without alteration.
What should you record about a clinically palpable cervical node?
Its exact site and laterality, size, tenderness, consistency and mobility, alongside the relevant oral examination and history.
Features that require more than symptomatic treatment
| Finding | Concern | Action principle |
|---|---|---|
| Induration / fixation | Infiltrative or malignant disease | Urgent appropriate specialist assessment. |
| Persistent unexplained ulcer | Cancer or another non-healing process | Establish cause and use the appropriate referral / biopsy pathway. |
| Red or red-white patch | Potentially malignant epithelial disease | Representative assessment and tissue diagnosis when indicated. |
| Neck mass / suspicious node | Metastatic, lymphoid, infectious or other pathology | Investigate the node in context; do not assume a dental cause. |
| Paraesthesia / unexplained mobility | Nerve or bone involvement | Correlate with imaging and urgent specialist investigation. |
| Possible vascular lesion | Bleeding risk | Assess vascularity before an incision. |
Choose a sample that answers the question
A larger or suspicious lesion commonly needs a representative incisional specimen, chosen from viable tissue with sufficient depth. Avoid necrotic-only sampling and preserve definitive cancer planning. An apparently benign small lesion may be suitable for excision, but the decision still depends on the differential and anatomy.
Supply the site, clinical appearance, duration, medicines, systemic features and ranked differential. Arrange separate handling for direct immunofluorescence or culture if needed. Reconcile histology with the examination: an inadequate or discordant sample may require further assessment. Record who will review and communicate the result.
A mucosal finding has a safety decision before a label
Suspicious epithelial lesion
- Persistent, indurated, red / red-white or changing
- Use the appropriate urgent pathway
- Plan representative histology
Possible vascular lesion
- Assess colour, compressibility and vascular clues
- Investigate before incision
- Use a safe specialist sampling plan
Apparently inflammatory lesion
- Identify a coherent cause
- Treat and set a review
- Reassess persistence or discordance
A distinction to remember
The three-week ulcer criterion is not a reason to delay referral of an already suspicious lesion. Pain and age do not reliably exclude malignancy.
A two-week lateral tongue ulcer is firm, fixed and associated with a neck lump. Should referral wait another week?
Reveal the reasoning
No. The current findings are already suspicious. Use the appropriate urgent specialist / suspected-cancer pathway rather than waiting to satisfy a duration mnemonic.
Guidance to read alongside this chapter
Oral cancer, staging and treatment consequences
The diagnosis, grade, anatomical stage and patient fitness answer different questions. Treatment balances disease control, survival, function and the patient’s priorities.
Separate the terms
| Term | Question answered | Clinical implication |
|---|---|---|
| Clinical suspicion | Does the pattern warrant investigation? | Starts the appropriate pathway; does not establish histology. |
| Histological diagnosis / grade | What is the lesion and how differentiated is it? | Supports biological assessment and treatment planning. |
| T component | Local primary-tumour extent | Site-specific staging incorporates relevant extent features, including depth of invasion in oral cavity disease. |
| N component | Regional nodal disease | Node burden and other staging features affect prognosis and treatment. |
| M component | Distant metastatic disease | Changes stage and the overall management discussion. |
| Patient / functional assessment | What treatment can the patient tolerate and value? | Fitness, swallowing, speech, nutrition, rehabilitation and preference shape care. |
Head and neck lymphatic glands (Gray's Anatomy, plate 602)
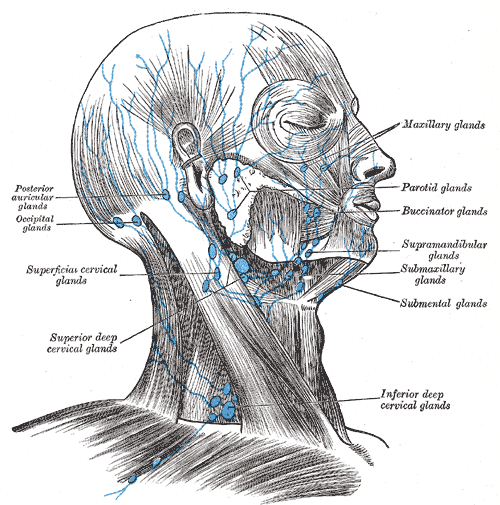
Find the submental and submandibular groups and follow drainage toward the cervical nodes. In this historical figure, ‘glands’ means lymph nodes and ‘submaxillary’ means submandibular. Use current cancer guidance for modern oncological neck levels.
Head and neck lymphatic glands (Gray's Anatomy, plate 602) · Henry Vandyke Carter; reproduced in Henry Gray, Anatomy of the Human Body (1918), plate 602 · Public domain. Unchanged published image; displayed responsively.
A multidisciplinary decision
Investigations establish the tissue diagnosis and disease extent, including the appropriate neck and distant assessment. The MDT considers site, stage, resectability, histology, comorbidity and function. Surgery, radiotherapy and systemic therapy have different roles and may be combined; there is no one generic oral-cancer operation or one medicine for every stage.
Reconstruction and rehabilitation are part of planning, not an afterthought. Effects on speech, swallowing, appearance, dental function and nutrition can be substantial. The discussion should include support services, treatment consequences and the patient’s priorities as well as tumour control.
Cervical lymph nodes and anatomical levels
Compare the named node groups with the numbered cervical levels. This schematic does not replace cross-sectional imaging criteria for staging or treatment planning.
Cervical lymph nodes and levels.png · Mikael Häggström, M.D. · CC0. None; reproduced without alteration.
What should you record about a clinically palpable cervical node?
Its exact site and laterality, size, tenderness, consistency and mobility, alongside the relevant oral examination and history.
Dental care before and after cancer treatment
Pre-treatment dental assessment aims to manage active disease, reduce later infection and avoid preventable invasive care in a compromised environment. Coordinate timing with the cancer team so that necessary care does not delay treatment without a clear reason. Radiation field and systemic treatment affect the risk assessment.
Radiotherapy can cause mucositis, salivary dysfunction, caries risk, fibrosis and bone-healing problems. Systemic anticancer treatment can cause mucositis, infection susceptibility and blood-cell abnormalities. Prevention, fluoride / hygiene planning, symptom support and coordinated follow-up matter. New persistent lesions or unexplained symptoms during surveillance need reassessment for recurrence or another cause.
Cancer planning combines disease and patient factors
Disease identity
- Representative histology
- Diagnosis and differentiation
- Biological context
Disease extent
- Primary, nodes and metastases
- Use current site-specific staging
- Select suitable disease-control options
Patient and function
- Fitness, nutrition and priorities
- Plan rehabilitation and support
- Coordinate treatment and surveillance
A distinction to remember
Grade is not stage. A small surface lesion may have important depth or nodal disease, and a painless lesion may still be invasive.
Why does pretreatment dental planning matter before head and neck radiotherapy?
Reveal the reasoning
Radiation can change salivary function, caries risk, soft tissues and bone healing. Coordinated preventive and disease-control care reduces avoidable later problems and helps protect function.
Guidance to read alongside this chapter
Test your recall
Which features make an oral lesion record reproducible?
Show answer
Exact subsite, size, surface, colour, border, ulceration, induration, symptoms and change over time.