
Odontogenic infection and the airway
Recognise spread, assess severity and arrange source control.
What to expect
Patients may present after oral antibiotics, with a dental source that is not obvious externally. A DCT often performs the first assessment, obtains a focused history and examination, starts the agreed admission pathway and contacts the senior decision maker.
What to know
Examine airway, voice, secretion control, swallowing, tongue and floor-of-mouth position, mouth opening, neck swelling, dental source, hydration and observations. Consider diabetes, immunosuppression and previous treatment. Distinguish localised infection from spreading infection with systemic illness. Imaging helps answer a defined question, but should not delay airway escalation. Antibiotics may be indicated for spread or systemic involvement under current local/SDCEP guidance; drainage and removal of the source remain central.
A practical approach
Call for senior and anaesthetic assessment immediately if there is airway concern. Use the trust’s sepsis and admission pathways where indicated, obtain investigations that change management, and coordinate theatre or drainage decisions. Document the likely source, anatomical spaces, trajectory, examination and response to treatment. Reassess after intervention and give explicit worsening signs at discharge.
Safety point
Do not reassure on the basis of absent fever or prescribe repeated antibiotics without a source-control plan. A deteriorating airway is a time-critical emergency.
Severity, spread and recognition of sepsis
Severity is determined by anatomy, function and physiology. A small dental source can cause a deep-space infection, while immunosuppression can make surface signs deceptively modest.
Identify the source and extent
Odontogenic infection commonly involves a mixed flora, including facultative organisms and anaerobes. The clinical presentation evolves from local inflammation to cellulitis or a collection and, in some cases, deeper spread. Find the causative tooth or other source and examine beyond the immediate swelling: floor of mouth, neck, mouth opening, voice and swallowing are important.
Spread depends on the point of cortical perforation and muscle attachments. Above or below the mylohyoid can direct initial lingual spread into sublingual or submandibular compartments. Masticator involvement can cause marked trismus; bilateral floor-of-mouth cellulitis can elevate the tongue. These relationships help localise disease, but the airway assessment has priority.
Mandibular landmarks
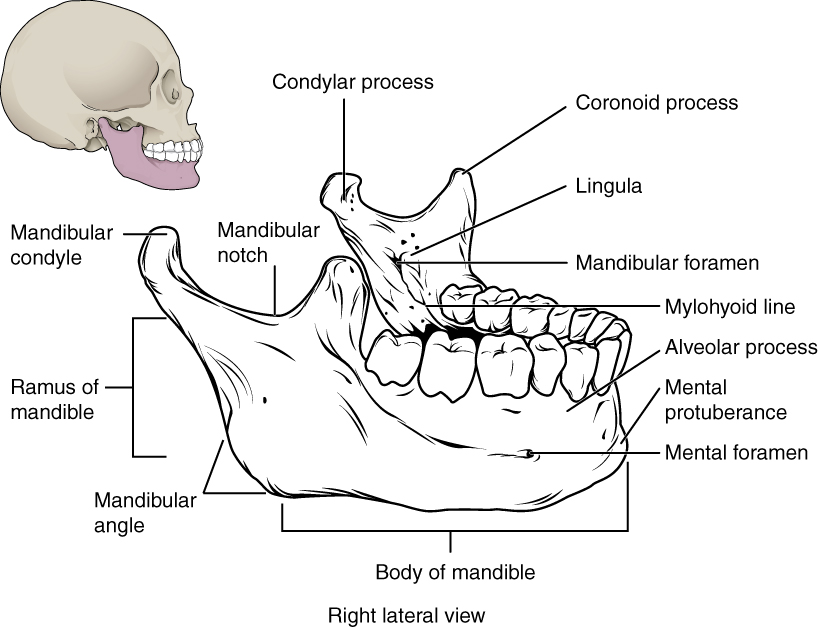
Locate the mental and mandibular foramina, lingula and mylohyoid line. The mandibular foramen, lingula and mylohyoid line are medial landmarks; this schematic brings several surfaces together. Relate the landmarks to nerve risk and fracture assessment.
Mandibular landmarks · OpenStax College · CC BY 3.0. Original image; displayed at a responsive size. Original publication.
Features that change urgency
| Finding | Why it matters | Direction of care |
|---|---|---|
| Breathing difficulty, drooling, altered voice or tongue elevation | Possible airway compromise | Urgent emergency assessment and specialist airway support. |
| Rapid progression, marked trismus or deep-neck features | Possible deep spread and difficult access | Hospital / specialist assessment rather than repeated oral prescriptions. |
| Confusion, circulatory compromise or other organ dysfunction | Possible sepsis or severe systemic disease | ABCDE, urgent escalation and the appropriate sepsis pathway. |
| Immunosuppression / neutropenia | Fever and pus may be muted | Lower threshold for coordinated medical assessment. |
| Failure to improve after source treatment | Incorrect source, inadequate drainage or another diagnosis | Reassess the patient and treatment; do not only change antibiotics. |
Coronal sublingual and submandibular spaces with normal MRI correlation
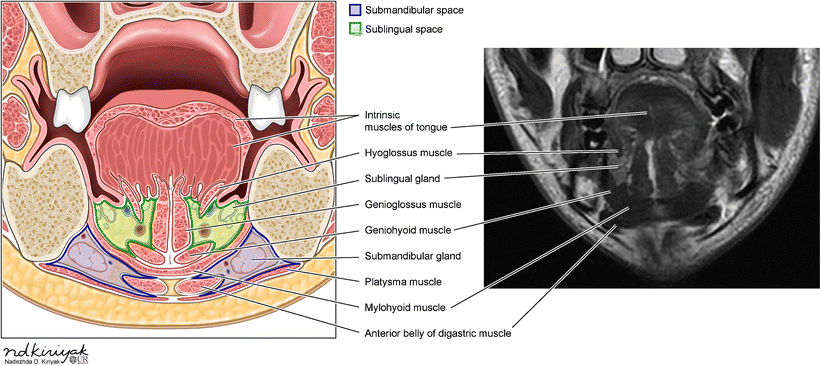
Identify the mylohyoid and compare the sublingual and submandibular compartments in the schematic and normal MRI. Relate the compartments to the tooth-apex relationships discussed in this section.
Coronal sublingual and submandibular spaces with normal MRI correlation · Swapnil Patel and Alok A. Bhatt (2018); illustration credited within the figure to Nadezhda D. Kiriyak / University of Rochester · CC BY 4.0. Unchanged published image; displayed responsively. Original publication.
Sepsis is a physiological syndrome
Sepsis is life-threatening organ dysfunction caused by a dysregulated response to infection. Temperature alone cannot confirm or exclude it. Assess observations, mental state, perfusion and risk factors. NICE NG253 applies to people aged 16 or over who are not and have not recently been pregnant; use the separate age- or pregnancy-specific pathway when applicable. NEWS2 supports assessment in the relevant acute-care settings but does not replace clinical judgement or an anatomical airway assessment.
Urgent management addresses airway and circulation, suitable antimicrobial treatment and source control with coordinated specialist care. Investigations and imaging proceed according to stability and the pathway. A threatened airway must not wait for CT, a culture result or a more precise fascial-space label.
An infection can be severe in three ways
Anatomical threat
- Deep or bilateral floor-of-mouth spread
- Swallowing / voice / airway changes
- Emergency airway and specialist assessment
Physiological threat
- Infection with systemic deterioration
- Assess organ dysfunction and observations
- Urgent sepsis / resuscitation pathway
Host vulnerability
- Immunosuppression or poor reserve
- Signs may be blunted
- Coordinate care with a lower escalation threshold
A distinction to remember
A low early-warning score, normal temperature or lack of fluctuance cannot rule out an anatomically threatened airway.
Why can an afebrile patient with a raised floor of mouth still need urgent hospital care?
Reveal the reasoning
The anatomical threat to the airway exists independently of fever. Immunosuppression may also blunt the usual signs. Assess breathing, swallowing, voice and progression and escalate urgently.
Guidance to read alongside this chapter
Source control and rational antimicrobial treatment
Antibiotics support treatment in selected infection; they do not remove an infected tooth or drain a collection. Decide the need for antimicrobials after assessing severity and the source-control plan.
Treat the source
A collection may need drainage, and the dental source may need endodontic treatment or extraction according to the clinical situation. A localised abscess can have poor antibiotic penetration and will often recur if the source remains. Severe spread may need specialist drainage and hospital support rather than a primary-care procedure.
Antibiotics are considered when local measures are insufficient or spreading / systemic infection and patient factors justify them. Assess allergy phenotype, medicines, renal and hepatic function and pregnancy. Select the narrowest effective treatment using current SDCEP and local hospital guidance. “Broader” does not automatically mean “better”.
What changes the antimicrobial decision?
| Situation | Decision principle | Common error |
|---|---|---|
| Localised drainable dental infection | Source control is central; assess whether antibiotics are needed | Prescribing while leaving an accessible source untreated. |
| Spreading / systemic infection | Antibiotics plus source control and severity-appropriate care | Treating airway or organ dysfunction with oral antibiotics alone. |
| Reported penicillin allergy | Establish reaction, timing and severity; use the appropriate alternative | Equating nausea with an immediate hypersensitivity reaction. |
| Non-response | Reassess diagnosis, drainage, adherence and host factors | Repeatedly escalating drug breadth without reassessment. |
| Severe / atypical / recurrent infection | Useful culture / tissue sampling when indicated | Delaying urgent treatment for a sample or relying on a superficial swab. |
Review and communicate the course
Current SDCEP dental-abscess guidance favours phenoxymethylpenicillin when appropriate because of its narrower spectrum; the actual choice and dose must follow the current entry and patient context. It usually describes a short course with review, ideally at three days, and stopping when symptoms have resolved according to that advice. Severe hospital infection follows the hospital antimicrobial pathway.
Give the indication, dose, frequency, duration, interaction advice and deterioration instructions clearly. At review, establish whether the source has been controlled and symptoms are resolving. Persistent symptoms may represent a retained source, inadequate drainage, resistant organism, host problem or a different diagnosis. Record why therapy continues, changes or stops.
Source control and antibiotics answer different needs
Local source
- Identify the tooth / collection
- Provide appropriate definitive care
- Review healing and symptoms
Antimicrobial indication
- Assess spread, systemic signs and host factors
- Choose current narrow-spectrum treatment
- Set a review and stop / continue decision
Non-response
- Re-examine source and patient
- Check drainage, diagnosis and medicine factors
- Escalate or sample when clinically indicated
A distinction to remember
Antibiotic failure is not always resistance. Inadequate drainage or an untreated source is often the question to revisit first.
A patient returns after two antibiotic courses with the same localised dental swelling. What should be reconsidered?
Reveal the reasoning
The diagnosis and source-control plan, including whether a collection has been drained and the causative tooth treated. Examine for spread and systemic disease before selecting any further antimicrobial.
Guidance to read alongside this chapter
Test your recall
Which airway, local and systemic findings determine the urgency of an odontogenic infection?
Show answer
Airway, swallowing, voice, secretion control, floor of mouth, trismus, neck spread, observations and systemic risk.